(1Prescription+2 Repoert):-


TC(1382).(56).General Medicine Department Case No (07):-Suspected Enteric Fever (Prescription+Report+Image)
Publication status: These identifiers were identified as next available in the earlier archive review, but a fresh live check could not be completed; confirm TC and departmental case number against current posts immediately before publication.
1. Case Identification | রোগীর পরিচিতি
Male, 22 years; Patient identity withheld for online privacy. Prescription 06 Oct 2026, CBC 03 Oct 2026 and serology reported 06 Oct 2026. Review on Saturday, 17 October 2026, 08:40 AM (Bangladesh Time). Prescription scan is ten days old; outcome after treatment unknown.
2. C/C — Chief Complaints | প্রধান উপসর্গ
- Fever ~17 days — প্রায় ১৭ দিন জ্বর (handwriting interpretation, moderately confident).
- Cough ~7 days — প্রায় ৭ দিন কাশি.
- Abdominal pain — পেটব্যথা.
- Anorexia — ক্ষুধামন্দা.
- Headache — মাথাব্যথা.
Confidence: 0.88 except duration 0.75.
3. Patient History | O/H, D/H, M/H
| O/H (Other history) | Not documented / লেখা নেই |
| D/H (Drug history) | Not documented / পূর্বের ওষুধ জানা নেই |
| M/H (Medical history) | Not documented / পূর্ব-রোগ জানা নেই |
| O/S/E, O/G/E | Separate headings not found; do not invent findings |
Allergy, prior antibiotics, travel, diarrhea/constipation, vaccination, occupational exposure and family history must be obtained.
Confidence: 0.98 that these details are unrecorded.
4. O/E — Examination | শারীরিক পরীক্ষা
BP ~120/80 mmHg; pulse ~88/min; T ~98°F at the time of visit. Two abbreviated findings appear as NAD but specific organs are not reliably legible. No documented SpO₂, respiratory rate, examination of chest or abdomen, hydration assessment. Confidence: 0.75–0.9.
5. Doctor’s Diagnosis & Plan | চিকিৎসকের ধারণা
Handwriting appears to note “Dengue Negative” and “Enteric Fever”. This represents the treating doctor’s clinical impression, not microbiologic confirmation. The dengue test report is not among the provided documents. Confidence: 0.75 for exact wording.
6. Original Reports & Prescribed Investigations | রিপোর্ট ও পরীক্ষা
| Test / পরীক্ষা | Result / ফল | Clinical meaning / অর্থ |
|---|---|---|
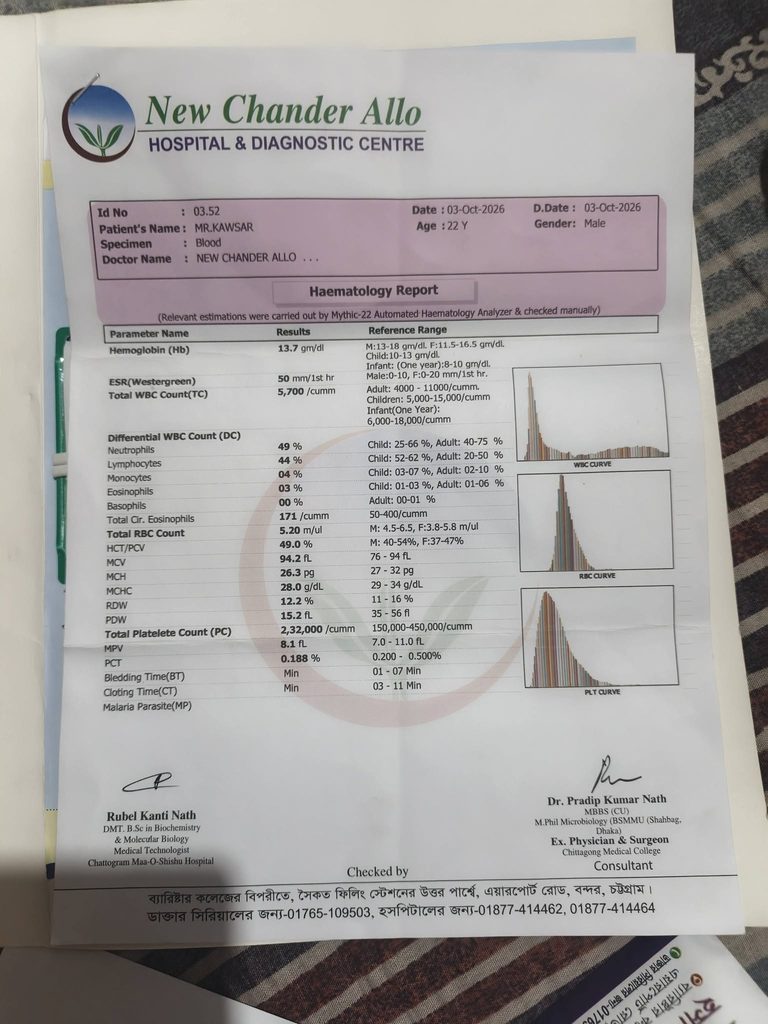
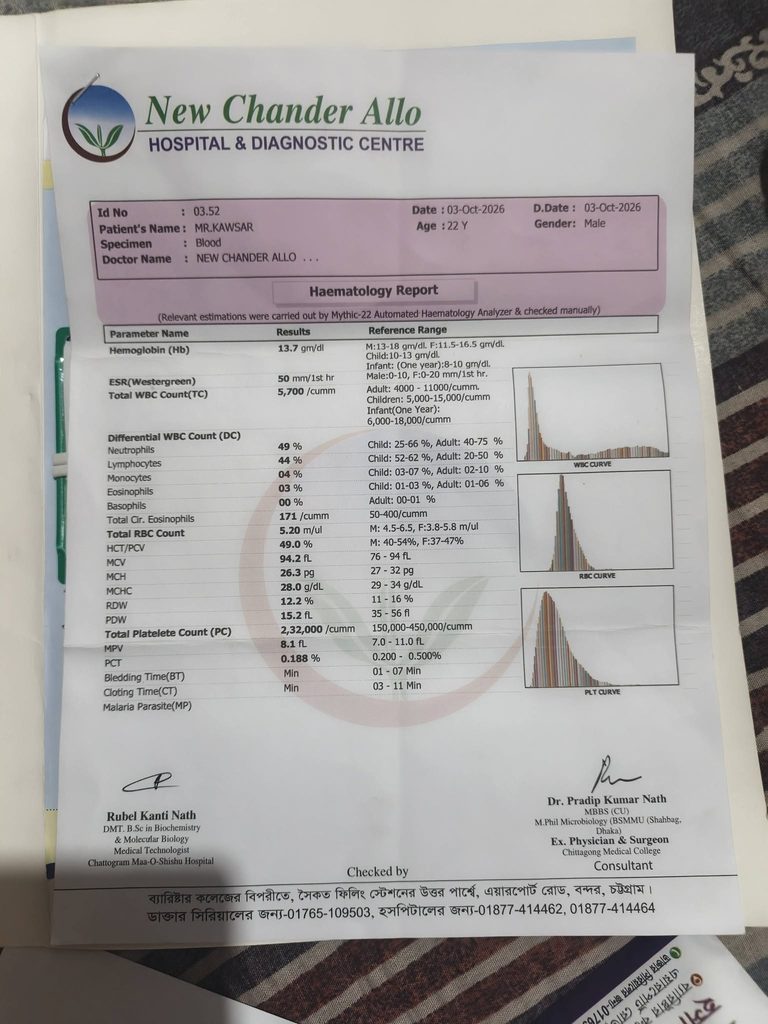
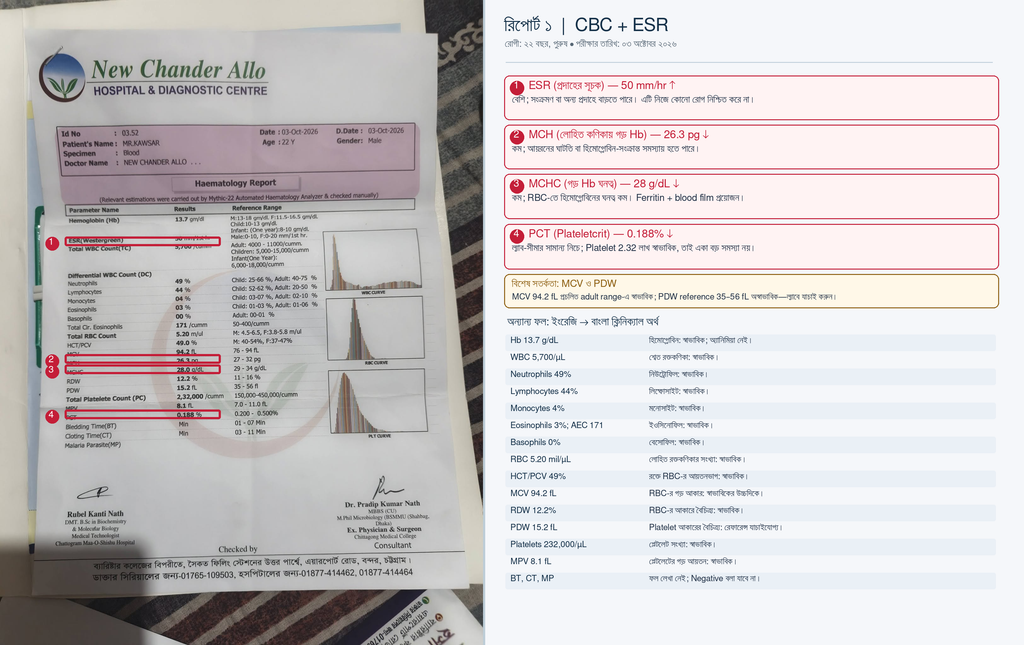
| ESR | 50 mm/h ↑ | নন-স্পেসিফিক প্রদাহ/সংক্রমণের সূচক |
| WBC | 5,700/µL | স্বাভাবিক; টাইফয়েড বাদ দেয় না |
| Hb | 13.7 g/dL | স্বাভাবিক |
| MCH / MCHC | 26.3 pg ↓ / 28.0 g/dL ↓ | হিমোগ্লোবিন সূচক কম; ferritin/iron profile |
| Platelets | 232,000/µL | স্বাভাবিক |
| Widal TO | 1:160 | একটি titre দিয়ে বর্তমান টাইফয়েড নিশ্চিত নয় |
| Typhoid IgG / IgM | Positive / Negative | পুরোনো exposure বা cross-reaction সম্ভব; active infection অনির্ণীত |
Prescription tests: LFT (লিভার ফাংশন), Chest X-ray PA (বুকের এক্স-রে), Urine R/E (প্রস্রাব পরীক্ষা), CRP (প্রদাহ সূচক). These are orders, not results. Blood culture + AST should be considered promptly if still febrile. Confidence: 0.95 for visible results, 0.85 for handwritten orders.
Case Images: Red-Boxed Supporting Documents | লাল বক্সে চিহ্নিত মূল নথি
রোগীর ব্যক্তিগত পরিচয় গোপন করে মূল প্রেসক্রিপশন ও দুটি রিপোর্ট যুক্ত করা হয়েছে। লাল বক্সগুলো প্রাসঙ্গিক অংশ নির্দেশ করে; পাশে clinical interpretation দেখুন।


Red boxes identify fields for review, not definitive disease confirmation. Any handwriting that is unclear remains provisional.
7. Prescribed Drug Analysis — MedEx অনুযায়ী | ১৬-দফা বিশ্লেষণ
Critical: Handwriting is partly illegible. Brand identification is provisional and must be checked against dispensing records. No guessed drug is an instruction to give medication. All prices are MedEx listing prices as checked 17 October 2026 and may change.
1) Traxon 2 g IV injection (সম্ভাব্য পাঠ)
| প্রেসক্রিপশন (পড়া) | Traxon 2 g IV injection (সম্ভাব্য পাঠ) |
| 1. Generic name | Ceftriaxone sodium |
| 2. Brand name | Traxon |
| 3. MedEx alternate brand | Traxef, Trizon, Tribac |
| 4. MedEx therapeutic class | Third-generation cephalosporins |
| 5. Pharmacological class | Beta-lactam / third-generation cephalosporin |
| 6. Use/purpose | Suspected serious bacterial infection / গুরুতর ব্যাকটেরিয়াল সংক্রমণ |
| 7. Why prescribed in this patient | প্রেসক্রিপশনে সম্ভবত 2 g ইনজেকশন; prolonged fever ও enteric-fever suspicion-এ দেওয়া হয়েছে—অবশ্যই মূল ampoule যাচাই |
| 8. Side effects | Rash, diarrhea, allergy, C. difficile infection, biliary sludge |
| 9. Direct MedEx link | https://medex.com.bd/generics/225/ceftriaxone-sodium/brand-names |
| 10. Unit/strip price | 2 g IV vial ৳350; strip price প্রযোজ্য নয় |
| 10A. Other composition | 250 mg, 500 mg, 1 g এবং 2 g vial; IV/IM strength preparation-dependent |
| 11. Mechanism of action | Inhibits bacterial cell-wall transpeptidation; bactericidal |
| 12. Other indications | Susceptible typhoid/bacteremia, pneumonia, other susceptible infections |
| 13. Interaction + contraindication | Avoid if severe cephalosporin allergy; warfarin bleeding risk; calcium-containing IV admixtures unsuitable |
| 14. Precautions & warnings | Check β-lactam allergy, response within 48–72 h, culture and susceptibility, C. difficile; may need hospital-based IV therapy |
| 15. Dosage & administration | Typical adult IV 1–2 g once daily (case/disease-specific); **not** an independently authorized patient prescription |
| 16. Pregnancy & lactation | Male patient. Pregnancy: cephalosporins generally usable when indicated; breastfeeding: usually compatible |
| Drug-reading confidence | 0.70 |
2) Napa Extend 665 mg XR (সম্ভাব্য পাঠ)
| প্রেসক্রিপশন (পড়া) | Napa Extend 665 mg XR (সম্ভাব্য পাঠ) |
| 1. Generic name | Paracetamol (acetaminophen) |
| 2. Brand name | Napa Extend |
| 3. MedEx alternate brand | Feva Extend, Fevac Extend |
| 4. MedEx therapeutic class | Non-Opioid Analgesics |
| 5. Pharmacological class | Analgesic-antipyretic / non-NSAID |
| 6. Use/purpose | Fever and headache / জ্বর ও মাথাব্যথা |
| 7. Why prescribed in this patient | জ্বর ও মাথাব্যথার উপসর্গ কমাতে, রোগের কারণ দূর করতে নয় |
| 8. Side effects | Rare rash; dose-related hepatotoxicity, overdose liver failure |
| 9. Direct MedEx link | https://medex.com.bd/brands/10454/napa-extend-665-mg-xr-tablet |
| 10. Unit/strip price | Unit ৳2.00; reported 24-tab strip ৳48.00 |
| 10A. Other composition | Napa 500 mg standard, Napa One 1000 mg; Napa suspension/injection; XR not interchangeable mg-for-mg |
| 11. Mechanism of action | Acts predominantly centrally to reduce pain and hypothalamic fever signaling |
| 12. Other indications | Fever, mild-moderate pain, headache |
| 13. Interaction + contraindication | Alcohol, hepatotoxic medicines, multi-ingredient cold medicines containing paracetamol; severe liver disease |
| 14. Precautions & warnings | Verify total daily paracetamol; XR tablets must be swallowed whole, not crushed |
| 15. Dosage & administration | MedEx XR adults >12 y: 2 tabs whole q6–8 h, max 6 tablets/24 h; in this case verify actual prescriber dose |
| 16. Pregnancy & lactation | Male patient. Pregnancy/lactation generally preferred analgesic if medically indicated at lowest effective dose |
| Drug-reading confidence | 0.90 |
3) Algin 50 mg tablet (সম্ভাব্য পাঠ; ছবিতে মাত্রা অস্পষ্ট)
| প্রেসক্রিপশন (পড়া) | Algin 50 mg tablet (সম্ভাব্য পাঠ; ছবিতে মাত্রা অস্পষ্ট) |
| 1. Generic name | Tiemonium methylsulfate |
| 2. Brand name | Algin |
| 3. MedEx alternate brand | Aspasom, Emogin, Veralgin |
| 4. MedEx therapeutic class | Anticholinergics |
| 5. Pharmacological class | Visceral antispasmodic / antimuscarinic-like |
| 6. Use/purpose | Abdominal cramps / পেটের খিঁচুনিজনিত ব্যথা |
| 7. Why prescribed in this patient | পেটব্যথার উপসর্গ সাময়িক কমাতে; enteric fever-এর definitive treatment নয় |
| 8. Side effects | Dry mouth, constipation, dizziness, blurred vision |
| 9. Direct MedEx link | https://medex.com.bd/brands/1430/algin-50-mg-tablet |
| 10. Unit/strip price | Unit ৳8.50; 10-tab strip ৳85 |
| 10A. Other composition | Syrup 10 mg/5 mL; injection 5 mg/2 mL; tablet 50 mg |
| 11. Mechanism of action | Antagonizes smooth-muscle contraction, reduces visceral spasm |
| 12. Other indications | Functional GI/biliary spasm; urinary tract spasm |
| 13. Interaction + contraindication | Avoid if hypersensitivity; caution in glaucoma, urinary obstruction and other anticholinergic risks |
| 14. Precautions & warnings | Caution in fever with significant abdominal tenderness/peritonitis signs; may mask surgical abdomen |
| 15. Dosage & administration | MedEx adult usual 2–6 tablets/day in divided doses; actual handwriting requires confirmation |
| 16. Pregnancy & lactation | Male patient. Pregnancy/lactation safety information limited; clinician decision |
| Drug-reading confidence | 0.81 |
4) Norium 10 mg tablet (সম্ভাব্য পাঠ)
| প্রেসক্রিপশন (পড়া) | Norium 10 mg tablet (সম্ভাব্য পাঠ) |
| 1. Generic name | Flunarizine |
| 2. Brand name | Norium |
| 3. MedEx alternate brand | Nalzin, Tigover, Rizelium |
| 4. MedEx therapeutic class | Other drugs for migraine |
| 5. Pharmacological class | Selective calcium-entry blocker; antihistaminic |
| 6. Use/purpose | Migraine prevention/vertigo / মাইগ্রেন প্রতিরোধ ও মাথা ঘোরা |
| 7. Why prescribed in this patient | মাথাব্যথার জন্য সম্ভবত দেওয়া; কিন্তু acute febrile headache-এ routine migraine prophylaxis প্রমাণিত নয় |
| 8. Side effects | Drowsiness, weight gain, depression, extrapyramidal adverse effects |
| 9. Direct MedEx link | https://medex.com.bd/brands/10842/norium-10-mg-tablet |
| 10. Unit/strip price | Unit ৳7.00; strip (10) ৳70 |
| 10A. Other composition | 5 mg and 10 mg tablet |
| 11. Mechanism of action | Limits calcium entry in excitable cells and reduces neuronal hyperexcitability |
| 12. Other indications | Migraine prophylaxis, selected vertigo |
| 13. Interaction + contraindication | Contraindicated in depression/Parkinsonism; sedatives/alcohol additive CNS effects |
| 14. Precautions & warnings | Assess headache phenotype before initiation; not an acute headache abortive drug |
| 15. Dosage & administration | Migraine prevention often 10 mg at night in adults <65 years; only after clinical assessment |
| 16. Pregnancy & lactation | Male patient. Pregnancy/lactation safety not established |
| Drug-reading confidence | 0.82 |
5) Naprosyn 500 mg (সম্ভাব্য পাঠ)
| প্রেসক্রিপশন (পড়া) | Naprosyn 500 mg (সম্ভাব্য পাঠ) |
| 1. Generic name | Naproxen sodium |
| 2. Brand name | Naprosyn |
| 3. MedEx alternate brand | Naprox, Anaflex, Napro-A |
| 4. MedEx therapeutic class | Non-steroidal Anti-inflammatory Drugs (NSAIDs); Drugs for Osteoarthritis; Drugs used for Rheumatoid Arthritis |
| 5. Pharmacological class | Non-selective COX-1/COX-2 inhibitor |
| 6. Use/purpose | Pain, inflammation / ব্যথা-প্রদাহ |
| 7. Why prescribed in this patient | মাথা বা শরীরের ব্যথা কমাতে; abdominal pain, dehydration অথবা dengue exclusion অজানা হলে risk–benefit পুনর্বিবেচনা |
| 8. Side effects | Gastritis, peptic ulcer/bleeding, AKI, fluid retention |
| 9. Direct MedEx link | https://medex.com.bd/brands/11447/naprosyn-500-mg-tablet/en |
| 10. Unit/strip price | Unit ৳16.00; 10-tab strip ৳160 |
| 10A. Other composition | 250 mg tablets; 125 mg/5 mL suspension |
| 11. Mechanism of action | Blocks COX-1/COX-2 → reduces prostaglandin synthesis |
| 12. Other indications | Arthritis and acute musculoskeletal/other pain |
| 13. Interaction + contraindication | Avoid in active GI bleeding/ulcer, NSAID hypersensitivity, significant kidney impairment; caution with anticoagulants, ACE-I, diuretics |
| 14. Precautions & warnings | In persistent fever of uncertain cause especially suspected dengue, prefer paracetamol and avoid routine NSAID until assessed |
| 15. Dosage & administration | Typical pain regimen depends on indication; MedEx notes initial 500 mg then 250 mg q6–8 h if needed; do not treat this as patient-specific approval |
| 16. Pregnancy & lactation | Male patient. Avoid from ~20 weeks pregnancy unless doctor specifically advises, and from ~30 weeks; enters breast milk |
| Drug-reading confidence | 0.82 |
6) Butil syrup (সম্ভাব্য পাঠ)
| প্রেসক্রিপশন (পড়া) | Butil syrup (সম্ভাব্য পাঠ) |
| 1. Generic name | Butamirate citrate |
| 2. Brand name | Butil |
| 3. MedEx alternate brand | Butaret, Kofnix, Mirakof |
| 4. MedEx therapeutic class | Cough suppressant |
| 5. Pharmacological class | Centrally acting non-opioid antitussive |
| 6. Use/purpose | Dry cough / শুকনো কাশি |
| 7. Why prescribed in this patient | কাশি শুকনো হলে কমাতে; productive cough থাকলে যুক্তি ভিন্ন |
| 8. Side effects | Occasional nausea, rash, dizziness, diarrhea |
| 9. Direct MedEx link | https://medex.com.bd/brands/18421/butil-75-mg-syrup |
| 10. Unit/strip price | 100 mL bottle ৳80; strip price প্রযোজ্য নয় |
| 10A. Other composition | Syrup 7.5 mg/5mL; class also has 50mg SR tablets |
| 11. Mechanism of action | Suppresses cough center activity centrally |
| 12. Other indications | Dry non-productive cough |
| 13. Interaction + contraindication | Do not routinely combine expectorants; hypersensitivity contraindication |
| 14. Precautions & warnings | Need respiratory examination and CXR if prolonged fever/cough; do not suppress important productive cough |
| 15. Dosage & administration | MedEx adult syrup: 15 mL four times daily; actual prescription handwriting looks different—confirm before use |
| 16. Pregnancy & lactation | Male patient. Avoid in 1st trimester; later pregnancy only if indicated; breast-feeding data limited |
| Drug-reading confidence | 0.65 |
Unverified handwritten entries — নিশ্চিত না হওয়া ওষুধ
- One “…bon” tablet ~30 mg, brand not MedEx-verified from handwriting.
- One “Vita…in” tablet, generic unknown; do not assume vitamin composition.
- Last “P…rin” tablet ~20 mg, brand/generic unknown; do not assume PPI.
For each unverified item, fields 1–16 (generic, mechanism, safety, dose, prices and MedEx URL) cannot safely be determined until brand spelling is checked. Confidence: <0.4, so no pharmacologic claim assigned.
8. Bangladesh Clinical Practice — Disease-Appropriate Medicines
| # | Common generic & example BD MedEx brand | Indication and rationale | Prescribing restriction |
|---|---|---|---|
| 1 | Ceftriaxone IV — Traxon / Traxef | Severe or hospitalized susceptible enteric fever; IV, AST guided | কেবল clinician-supervised, no routine injection for positive Widal |
| 2 | Azithromycin oral — Azithrocin / Zithrin | Clinically justified uncomplicated typhoid in suitable context | Blood culture and local resistance considered |
| 3 | Paracetamol — Napa / Napa Extend | Fever and headache symptom relief | Prevent total daily dose overlap |
| 4 | ORS and fluids | Hydration and electrolyte replacement | Evaluate dehydration/heart-kidney issues |
| 5 | Tiemonium — Algin | Cramping abdominal pain if surgical abdomen excluded | Symptomatic only |
| 6 | Butamirate — Butil | Dry bothersome cough, after examining cause | Avoid routine use in productive cough |
These are examples of Bangladesh practice / MedEx-listed agents, not a validated drug set for this undiagnosed patient. Cefixime or fluoroquinolones should not be automatically substituted given resistance considerations. Confidence: 0.9 for drug class and country listing, lower for patient suitability until examined.
9. My Clinical Working Assessment | স্বাধীন রোগ নির্ণয়
Prolonged undifferentiated febrile illness (reported 17 days), suspected enteric fever (unconfirmed); concomitant cough and abdominal pain; raised ESR; low MCH/MCHC without anemia.
বাংলায়: দীর্ঘস্থায়ী জ্বরের রোগ, টাইফয়েডের সন্দেহ থাকলেও জীবাণুবৈজ্ঞানিক নিশ্চয়তা নেই; সঙ্গে কাশি, পেটব্যথা ও ESR বৃদ্ধি। Fever resolution must be assessed afresh because the prescription is from 6 October. Confidence: 0.86 for syndrome; active typhoid not sufficiently substantiated (no numeric probability assigned).
10. Definition & Pathophysiology | সংজ্ঞা ও কারণ
Enteric fever is a systemic infection due to Salmonella Typhi or S. Paratyphi; humans acquire it through contaminated food or water. Bacteremia and reticuloendothelial infection cause sustained fever, headache and variable abdominal complaints. A cough can occur but is not specific. Confidence: 0.98.
11. Differential Diagnosis | বিকল্প রোগ
- Other respiratory infection / pneumonia: cough and fever, needs chest examination and CXR.
- Tuberculosis: consider if fever persists, weight loss, night sweats, prolonged cough or epidemiologic exposure.
- Dengue: evaluate by illness-day appropriate testing; written “negative” cannot be verified from provided image.
- Malaria where epidemiologically relevant, urinary infection, viral respiratory illness, other invasive bacterial infection.
Confidence of particular alternative diagnoses cannot be quantified from these data.
12. Diagnostic Gaps & Investigation Priority | পরবর্তী পরীক্ষা
Today if symptomatic: examine vital signs including SpO₂, respiratory and abdominal findings; blood culture × appropriate sets + AST before additional antibiotics where possible; CBC, CRP, LFT, RFT/electrolytes, urine R/E and culture if urinary symptoms, chest X-ray PA; dengue/malaria investigations guided by exposure and illness day; TB testing if clinically indicated. After prior ceftriaxone, blood culture sensitivity may decline. Iron deficiency evaluation separately: ferritin, transferrin saturation and smear. Confidence: 0.95.
13. Critical Prescription Review | ব্যবস্থাপত্রের ঝুঁকি
- Antibiotic administered without documented culture: may prevent microbiologic confirmation and foster unnecessary antibiotic exposure.
- Naproxen for fever with abdominal pain / unverified dengue result carries GI bleeding and kidney risks.
- Napa Extend and naproxen are both pain/fever reducers; clarify whether both are truly needed.
- Flunarizine for headache is prophylactic migraine therapy, not routine acute fever-related headache treatment.
- Multiple brand names/doses and “Dengue negative” are unclear or have no accompanying source result.
These are documentation and safety concerns, not proof that the original doctor’s decisions were incorrect. Confidence: 0.85–0.95.
14. Doctor Dx versus LIPU MED Dx | সবুজ ও কমলা তুলনা
15. Management & Immediate Action | ক্লিনিক্যাল পদক্ষেপ
If fever, cough, abdominal pain or weakness continues on 17 October: same-day Internal Medicine review. Document fever pattern, prior antibiotic dosing/allergy, hydration, oxygen saturation and full exam. Obtain cultures if feasible, review existing injection/medicine packaging and test results, then select antimicrobial according to illness severity, susceptibility and clinician judgment. Stable patients need clear reassessment in 24–48 h. Emergency transfer for hypoxia, hypotension, altered sensorium, persistent vomiting, GI bleed, rigid abdomen or reduced urine. Confidence: 0.95.
16. Real Prescription Demo & Referral Note | শিক্ষামূলক প্রেসক্রিপশন
Patient: 22/M, review date 17 Oct 2026.
C/C: History of ~17-day fever, ~7-day cough, abdominal pain, anorexia, headache (as documented 6 Oct).
O/E: Today’s vitals and examination must be entered by the attending clinician.
Provisional Dx: Prolonged febrile illness — R/O enteric fever; evaluate respiratory focus; increased ESR; low MCH/MCHC without anemia.
Investigations: Blood culture + AST if clinically indicated, CBC, CRP, LFT, RFT, chest X-ray, urine R/E; ferritin later.
Rx: Oral hydration and antipyretic as assessed; no automatic antibiotic based only on Widal/IgG. If clinically serious enteric fever and suitable for ceftriaxone after allergy check, the treating clinician can consider IV ceftriaxone with susceptibility-informed reassessment.
Review: 24–48 h or sooner if deterioration.
Referral to: Consultant, Internal Medicine / Infectious Diseases.
Referral statement: “22-year-old male with prolonged febrile illness, cough, abdominal pain and nonspecific positive typhoid serology. Widal TO 1:160; IgG positive, IgM negative; ESR 50 mm/h; normal WBC, platelets and Hb. Please evaluate current activity of infection, respiratory source, antibiotic exposure and appropriate culture/AST-guided management.”
17. Overview, Action Plan, References & Author | সারসংক্ষেপ
Overview: Suspected rather than confirmed enteric fever. Action: current reassessment, culture if febrile, review respiratory involvement and medication exposure. Confidence: 0.98 for unconfirmed-status; 0.85 for syndrome classification.
- Harrison’s Principles of Internal Medicine, 22nd ed., Salmonella infections; Davidson’s Principles and Practice of Medicine, 24th ed., infectious disease chapters (page numbers not verified).
- CDC, Clinical Guidance for Typhoid Fever and Paratyphoid Fever; CDC Yellow Book 2026. Clinical Guidance.
- Wijedoru L, Mallett S, Parry CM. Rapid diagnostic tests for typhoid and paratyphoid fever. Cochrane Database Syst Rev. 2017. DOI: 10.1002/14651858.CD008892.pub2.
- Tanmoy AM et al. Trends in antimicrobial resistance amongst Salmonella Typhi in Bangladesh. PLoS Negl Trop Dis. 2024;18:e0012558. DOI: 10.1371/journal.pntd.0012558.
- General Medicine Department archive lists department code (56) and Case No 06 as its last published departmental case (14 Oct 2026). Medical Blog archive shows TC(1381) on 17 Oct 2026. Next proposed: TC(1382).(56).General Medicine Department Case No (07) — provisional only; verify before publishing.
Author: Md.Rafiqul Islam Lipu
Reviewed: Saturday, 17 October 2026, 08:40 AM (Bangladesh Time)
Report Analysis 2:-
Clinical Report Analysis — CBC, ESR, Widal & Typhoid IgG/IgM
রোগীর রিপোর্ট বিশ্লেষণ, সম্ভাব্য রোগনির্ণয় ও চিকিৎসা পরিকল্পনা
Patient: ২২ বছর, পুরুষ CBC Report: 03 October 2026 Immunological Report: 06 October 2026 Clinical Review: 17 October 2026
আপনার দেওয়া দুটি রিপোর্টের প্রতিটি ফলাফল পরীক্ষা করেছি। অস্বাভাবিক ফলগুলো মূল রিপোর্টে লাল বক্স দিয়ে চিহ্নিত করেছি এবং পাশে ইংরেজি নামসহ বাংলা ক্লিনিক্যাল ব্যাখ্যা দিয়েছি।
🔴 ১. Red-Marked Original Reports
Report 1 — CBC + ESR
📄 লাল বক্সে চিহ্নিত CBC রিপোর্ট ও বাংলা ব্যাখ্যা দেখুন
Report 2 — Widal + Typhoid IgG/IgM
📄 লাল বক্সে চিহ্নিত Widal রিপোর্ট ও বাংলা ব্যাখ্যা দেখুন
গুরুত্বপূর্ণ ক্লিনিক্যাল সিদ্ধান্ত: রিপোর্টে Widal TO 1:160 এবং Typhoid IgG Positive পাওয়া গেছে। কিন্তু এগুলোর ভিত্তিতে রোগীর বর্তমানে টাইফয়েড হয়েছে—এমন নিশ্চিত রোগনির্ণয় করা যায় না। WHO ও CDC উভয়ই বর্তমান সংক্রমণ নিশ্চিত করতে Blood Culture-কে অগ্রাধিকার দেয়।
২. CBC Report — প্রতিটি ফলাফলের ক্লিনিক্যাল অর্থ Investigation (English) Result বাংলা অর্থ ও Clinical Interpretation Hemoglobin (Hb) 13.7 g/dL স্বাভাবিক। বর্তমানে অ্যানিমিয়া নেই। 🔴 ESR 50 mm/1st hr ↑ উল্লেখযোগ্যভাবে বেশি। শরীরে প্রদাহ বা সংক্রমণ থাকতে পারে। Total WBC Count 5,700/µL স্বাভাবিক। শ্বেত রক্তকণিকার সংখ্যা বাড়েনি। Neutrophils 49% স্বাভাবিক। Lymphocytes 44% স্বাভাবিক। Monocytes 4% স্বাভাবিক। Eosinophils 3% স্বাভাবিক। Basophils 0% স্বাভাবিক। Absolute Eosinophil Count 171/µL স্বাভাবিক। Total RBC Count 5.20 million/µL স্বাভাবিক। HCT/PCV 49% স্বাভাবিক। MCV 94.2 fL ল্যাবের সীমার চেয়ে 0.2 fL বেশি, কিন্তু প্রচলিত প্রাপ্তবয়স্ক সীমায় স্বাভাবিক। 🔴 MCH 26.3 pg ↓ RBC-প্রতি গড় হিমোগ্লোবিনের পরিমাণ কম। 🔴 MCHC 28.0 g/dL ↓ RBC-তে হিমোগ্লোবিনের গড় ঘনত্ব কম। RDW 12.2% স্বাভাবিক। RBC-এর আকারের বৈচিত্র্য স্বাভাবিক। PDW 15.2 fL ল্যাবের দেওয়া রেফারেন্স সীমা অস্বাভাবিক; যাচাই প্রয়োজন। Platelet Count 232,000/µL স্বাভাবিক। MPV 8.1 fL স্বাভাবিক। 🔴 PCT (Plateletcrit) 0.188% ↓ ল্যাবের সীমার সামান্য নিচে; একা বিশেষ রোগ নির্দেশ করে না। Bleeding Time ফল লেখা নেই মূল্যায়ন করা যাবে না। Clotting Time ফল লেখা নেই মূল্যায়ন করা যাবে না। Malaria Parasite ফল লেখা নেই ম্যালেরিয়া নেগেটিভ বলা যাবে না।
🔴 গুরুত্বপূর্ণ অস্বাভাবিক ফলগুলোর কারণ
A. ESR = 50 mm/hr
ESR অর্থ *Erythrocyte Sedimentation Rate*—লোহিত রক্তকণিকা কত দ্রুত নিচে বসে যায় তার পরিমাপ।
এটি বৃদ্ধি পেতে পারে:
– ব্যাকটেরিয়াল বা ভাইরাল সংক্রমণ – টাইফয়েডসহ অন্যান্য দীর্ঘস্থায়ী জ্বরের রোগ – যক্ষ্মা – অটোইমিউন বা প্রদাহজনিত রোগ – কিছু রক্তস্বল্পতা এবং অন্যান্য দীর্ঘস্থায়ী অসুখ
Clinical conclusion: Elevated ESR indicates possible inflammation but is not specific for typhoid.
Confidence: 0.99 — ESR বেশি, এটি নিশ্চিত। কিন্তু কেন বেশি, তা এই পরীক্ষায় নির্ণয় করা যায় না।
B. MCH = 26.3 pg এবং MCHC = 28.0 g/dL
এই দুটি সূচক কম থাকায় হিমোগ্লোবিনের পরিমাণ বা ঘনত্ব কম থাকার ইঙ্গিত পাওয়া যায়।
সম্ভাব্য কারণ:
– প্রাথমিক আয়রনের ঘাটতি – Thalassemia trait বা অন্য hemoglobinopathy – দীর্ঘস্থায়ী প্রদাহের সঙ্গে আয়রনের বিপাকে পরিবর্তন – পরীক্ষাগত বা বিশ্লেষণগত পার্থক্য
কিন্তু রোগীর Hb 13.7 g/dL এবং MCV 94.2 fL। ফলে বর্তমানে iron deficiency anemia অথবা thalassemia trait নিশ্চিত করা যাবে না।
Next investigation: Serum Ferritin, Peripheral Blood Film এবং প্রয়োজন অনুযায়ী Iron Profile।
Confidence: 0.95 — MCH/MCHC কম। নির্দিষ্ট কারণের বিষয়ে সিদ্ধান্ত অনিশ্চিত।
C. PCT = 0.188%
এখানে PCT বলতে Plateletcrit বোঝানো হয়েছে; এটি Procalcitonin নয়।
Platelet count স্বাভাবিক থাকায় এই সামান্য নিম্নমান সাধারণত একা চিকিৎসার কারণ নয়। প্রয়োজনে CBC পুনরায় করা যায়।
৩. Widal & Typhoid IgG/IgM — বিস্তারিত বিশ্লেষণ Investigation Result Clinical Meaning 🔴 TO (S. Typhi O) 1:160 ল্যাবের 1:80 সীমার বেশি; তবে একক Widal titre বর্তমান টাইফয়েড নিশ্চিত করে না। TH (S. Typhi H) 1:80 ল্যাবের সীমায়; পূর্ববর্তী সংক্রমণ বা exposure-এর পরেও থাকতে পারে। AH (Paratyphi A H) 1:40 নিম্ন titre; রোগ নিশ্চিত করে না। BH (Paratyphi B H) 1:40 নিম্ন titre; রোগ নিশ্চিত করে না। 🔴 S. Typhi IgG Positive পূর্ববর্তী সংক্রমণ, exposure বা cross-reaction হতে পারে। S. Typhi IgM Negative IgM শনাক্ত হয়নি; তবে বর্তমান টাইফয়েড সম্পূর্ণ বাদ দেওয়া যায় না।
Widal 1:160-এর প্রকৃত অর্থ কী?
রিপোর্টে “TITRE IS SIGNIFICANT” লেখা আছে।
এটি ল্যাবরেটরির নির্ধারিত সীমার ভিত্তিতে দেওয়া মন্তব্য। বাংলাদেশসহ টাইফয়েড-প্রবণ এলাকায় পূর্ববর্তী exposure, antibody persistence এবং cross-reactivity-এর কারণে Widal Positive হতে পারে।
একইভাবে IgG Positive ও IgM Negative থাকলে পূর্ববর্তী exposure-এর সম্ভাবনা থাকে, কিন্তু শুধু এই ফল দিয়ে পুরোনো কিংবা বর্তমান সংক্রমণ নির্দিষ্ট করা যায় না।
সিদ্ধান্ত: এই রোগীর active typhoid fever এখনও unconfirmed.
Confidence: 0.99 — Serology alone cannot confirm active typhoid.
৪. My Clinical Working Assessment
Prescription-Ready Provisional Diagnosis
বর্তমান রিপোর্টে জ্বরের ইতিহাস, কতদিন ধরে জ্বর, তাপমাত্রা, শারীরিক পরীক্ষার ফল এবং পূর্ববর্তী অ্যান্টিবায়োটিক ব্যবহারের তথ্য নেই।
তাই দুটি পরিস্থিতি আলাদা করতে হবে।
রোগীর বর্তমানে জ্বর থাকলে:
Provisional Dx: Undifferentiated febrile illness; Enteric fever (Typhoid) to be ruled out. Elevated ESR with positive typhoid serology (non-confirmatory). Reduced MCH/MCHC without anemia.
বাংলায়:
অজানা কারণে জ্বর; টাইফয়েড জ্বরের সম্ভাবনা যাচাই প্রয়োজন। ESR বৃদ্ধি এবং টাইফয়েডের অ্যান্টিবডি পরীক্ষায় পজিটিভ ফল রয়েছে, তবে সংক্রমণ নিশ্চিত হয়নি। অ্যানিমিয়া ছাড়াই MCH ও MCHC কম পাওয়া গেছে।
রোগীর বর্তমানে জ্বর না থাকলে:
Dx: Positive typhoid serology of uncertain clinical significance; Elevated ESR; Low MCH/MCHC requiring evaluation.
এক্ষেত্রে শুধু পুরোনো রিপোর্ট দেখে টাইফয়েডের চিকিৎসা শুরু করা যুক্তিযুক্ত নয়।
Diagnostic Confidence Clinical Finding Confidence ESR elevated 0.99 Reduced MCH/MCHC 0.99 Typhoid serology reactive 0.99 Iron deficiency may be present Moderate — further tests required Currently active typhoid fever Not established; diagnostic confidence insufficient
এগুলো পরীক্ষার ফল সম্পর্কে আস্থার মাত্রা; রোগীর টাইফয়েড হওয়ার শতকরা সম্ভাবনা নয়।
৫. Differential Diagnosis — কোন রোগগুলো বিবেচনা করবেন?
যদি রোগীর জ্বর বা সংক্রমণের উপসর্গ থাকে, চিকিৎসক নিচের রোগগুলো বিবেচনা করবেন। সম্ভাব্য রোগ কখন সন্দেহ করবেন? Enteric Fever (Typhoid/Paratyphoid) কয়েকদিনের ক্রমবর্ধমান জ্বর, মাথাব্যথা, দুর্বলতা, পেটের উপসর্গ Dengue Fever তীব্র জ্বর, শরীরব্যথা, মাথাব্যথা, উপযুক্ত মৌসুম বা exposure Other Bacterial Infection নির্দিষ্ট সংক্রমণের উপসর্গ, স্থানীয় সংক্রমণের উৎস Viral Febrile Illness ভাইরাল উপসর্গ ও স্বল্পমেয়াদি জ্বর Tuberculosis দীর্ঘদিনের জ্বর, রাতের ঘাম, ওজন কমা, কাশি Inflammatory Disease দীর্ঘস্থায়ী প্রদাহজনিত উপসর্গ
এসব রোগের কোনোটিই শুধু বর্তমান রিপোর্ট দিয়ে নিশ্চিত করা যায় না।
৬. Further Investigations — পরবর্তী পরীক্ষা
Priority 1: যদি রোগীর বর্তমানে জ্বর থাকে
Blood Culture with Antimicrobial Susceptibility Testing সবচেয়ে গুরুত্বপূর্ণ পরীক্ষা।
সম্ভব হলে অ্যান্টিবায়োটিক শুরুর আগে রক্তের নমুনা সংগ্রহ করতে হবে। প্রয়োজন অনুযায়ী একাধিক blood culture নেওয়া যায়। পূর্বে অ্যান্টিবায়োটিক খেয়ে থাকলে পরীক্ষার sensitivity কমতে পারে।
এর সঙ্গে প্রয়োজন অনুযায়ী: Investigation Clinical Purpose Blood Culture + AST Salmonella Typhi/Paratyphi বা অন্য bloodstream infection শনাক্ত করা CBC Repeat রক্তকণিকার বর্তমান অবস্থা CRP প্রদাহের মাত্রা ও চিকিৎসা পর্যবেক্ষণে সহায়ক Serum Creatinine, Electrolytes কিডনি ও পানিশূন্যতার অবস্থা Liver Function Tests লিভার জড়িত আছে কি না Dengue NS1/IgM জ্বরের দিন অনুযায়ী ডেঙ্গু মূল্যায়ন Malaria RDT/Smear উপযুক্ত ভ্রমণ বা exposure history থাকলে
Blood Culture গুরুত্বপূর্ণ হলেও একবারের Negative Culture টাইফয়েড পুরোপুরি বাদ দেয় না।
Priority 2: MCH/MCHC কম থাকার কারণ
Serum Ferritin + Peripheral Blood Film প্রথমে করুন।
Ferritin-এর ব্যাখ্যার সময় প্রদাহের বিষয়টি বিবেচনা করতে হবে। প্রয়োজন হলে Serum Iron, TIBC, Transferrin Saturation এবং পরবর্তী ধাপে Hb Electrophoresis করা যেতে পারে।
৭. Management / Treatment Plan
A. রোগীর জ্বর না থাকলে
শুধু Widal 1:160 বা IgG Positive-এর কারণে অ্যান্টিবায়োটিক দেওয়ার প্রয়োজন প্রতিষ্ঠিত হয় না।
চিকিৎসক বর্তমান উপসর্গ, পরীক্ষা এবং আগের চিকিৎসার ইতিহাস দেখে ESR ও RBC indices-এর পরবর্তী মূল্যায়ন করবেন।
B. Active Enteric Fever clinically suspected হলে
রোগীকে পরীক্ষা করে, severity মূল্যায়ন করে এবং সম্ভব হলে Blood Culture সংগ্রহের পরে অ্যান্টিবায়োটিক নির্বাচন করতে হবে।
প্রাপ্তবয়স্কদের জন্য guideline-এ ব্যবহৃত উদাহরণ: পরিস্থিতি Guideline-Based Treatment Option Uncomplicated enteric fever Azithromycin oral, সাধারণত ৭ দিন Severe enteric fever Hospital treatment; Ceftriaxone IV যেখানে susceptibility উপযুক্ত Resistant/XDR infection Infectious Disease consultation এবং AST অনুযায়ী চিকিৎসা
MSF-এর গাইডলাইনে uncomplicated adult enteric fever-এর জন্য Azithromycin 500 mg–1 g once daily for 7 days অথবা প্রথম দিন 1 g এবং পরবর্তী দিনগুলোতে 500 mg উল্লেখ আছে। Severe illness-এ Ceftriaxone IV-এর মতো parenteral treatment ব্যবহৃত হয়।
এগুলো এই রোগীর জন্য চূড়ান্ত প্রেসক্রিপশন নয়। বর্তমান উপসর্গ, ওজন, drug allergy, QT-prolongation risk, hepatic/renal function এবং স্থানীয় antimicrobial resistance বিবেচনা করে চিকিৎসা নির্ধারণ করতে হবে। বাংলাদেশে Azithromycin resistance-ও রিপোর্ট হয়েছে।
যদি রোগীর Sepsis, Shock, তীব্র পেটব্যথা, পেট শক্ত হয়ে যাওয়া, অন্ত্রে রক্তক্ষরণ, বিভ্রান্তি বা পানি পান করতে না পারার মতো অবস্থা থাকে, জরুরি হাসপাতালে চিকিৎসা প্রয়োজন।
৮. Doctor’s Immediate Action Plan
প্রথম কাজ: রোগীকে সরাসরি মূল্যায়ন করে বর্তমান জ্বরের ইতিহাস ও vital signs সংগ্রহ করুন।
এরপর:
1. জ্বর থাকলে তার duration, pattern, abdominal symptoms, bowel habit, hydration status ও পূর্ববর্তী antibiotic history নিন। 2. সম্ভাব্য টাইফয়েড হলে Blood Culture + AST সংগ্রহ করুন; গুরুতর সংক্রমণে পরীক্ষা করতে গিয়ে জরুরি চিকিৎসা বিলম্ব করবেন না। 3. CBC, CRP, LFT/RFT এবং প্রয়োজন অনুযায়ী অন্য জ্বরের কারণগুলো পরীক্ষা করুন। 4. সংক্রমণের সম্ভাবনা ও severity অনুযায়ী চিকিৎসা শুরু বা পরিবর্তন করুন। 5. রোগীকে ২৪–৪৮ ঘণ্টার মধ্যে পুনর্মূল্যায়ন করুন; অবস্থার অবনতি হলে অবিলম্বে হাসপাতালে পাঠান।
৯. Specialist Referral
Recommended Department
প্রথম পছন্দ: Department of Internal Medicine
জ্বর দীর্ঘস্থায়ী, রোগনির্ণয় জটিল, চিকিৎসায় উন্নতি হচ্ছে না অথবা resistant enteric fever সন্দেহ হলে Infectious Diseases Specialist-এর পরামর্শ প্রয়োজন।
MCH/MCHC কম থাকার কারণ অনির্ধারিত থাকলে প্রাথমিক Iron Profile-এর পরে প্রয়োজন অনুযায়ী Hematology referral করা যেতে পারে।
Prescription-Ready Referral Note
To: Consultant, Department of Internal Medicine / Infectious Diseases
Re: 22-year-old male, evaluation of abnormal typhoid serology and elevated ESR.
Laboratory findings: ESR 50 mm/hr, WBC 5,700/µL, Hb 13.7 g/dL, Platelets 232,000/µL, MCH 26.3 pg and MCHC 28 g/dL. Widal TO 1:160, TH 1:80; S. Typhi IgG Positive, IgM Negative.
Clinical impression: Positive typhoid serology without confirmation of active enteric fever; elevated ESR and reduced MCH/MCHC without anemia.
Advice: Kindly assess current clinical symptoms and evaluate for enteric fever or an alternative cause of inflammation. Consider blood culture with antimicrobial susceptibility testing if clinically indicated, along with appropriate investigations.
Referral requested for: Diagnostic evaluation and further management.
১০. Overview / Summary — চূড়ান্ত ক্লিনিক্যাল সিদ্ধান্ত
এই রোগীর রিপোর্টে প্রধানত তিন ধরনের পরিবর্তন পাওয়া যাচ্ছে।
প্রথমত, ESR 50 mm/hr—এটি বেশি এবং প্রদাহ বা সংক্রমণের কারণ অনুসন্ধান প্রয়োজন।
দ্বিতীয়ত, MCH ও MCHC কম, কিন্তু Hb স্বাভাবিক। ফলে সম্ভাব্য আয়রনের ঘাটতি বা অন্য RBC disorder মূল্যায়ন করা প্রয়োজন; এখনই অ্যানিমিয়া নির্ণয় করা যাবে না।
তৃতীয়ত, Widal TO 1:160 ও IgG Positive থাকলেও বর্তমানে টাইফয়েড নিশ্চিত নয়। জ্বরের তথ্য এবং প্রাসঙ্গিক Blood Culture ছাড়া নির্ভরযোগ্য definitive diagnosis দেওয়া সম্ভব নয়।
Final Working Diagnosis — বাংলায়
“টাইফয়েডের অ্যান্টিবডি পরীক্ষায় পজিটিভ ফল, কিন্তু সক্রিয় টাইফয়েড সংক্রমণ অনিশ্চিত; ESR বৃদ্ধি এবং রক্তস্বল্পতা ছাড়াই MCH/MCHC হ্রাস।”
জ্বর থাকলে *Enteric Fever to be Ruled Out* যুক্ত করতে হবে।
১১. Actionable Plan — সংক্ষিপ্ত নির্দেশনা
বর্তমানে জ্বর থাকলে: Medicine Specialist-এর মূল্যায়ন, Blood Culture + AST এবং প্রয়োজন অনুযায়ী অন্যান্য পরীক্ষা।
জ্বর না থাকলে: শুধু Widal/IgG-এর জন্য অ্যান্টিবায়োটিক নয়; ESR-এর কারণ এবং MCH/MCHC-এর পরিবর্তন মূল্যায়ন।
প্রেসক্রিপশনে এখনই “Confirmed Typhoid Fever” লিখবেন না।
১২. Reference List
Textbooks
1. *Harrison’s Principles of Internal Medicine*, 22nd Edition — Salmonella infections / Enteric fever. 2. *Davidson’s Principles and Practice of Medicine*, 24th Edition — Infectious diseases and hematological investigations.
Guidelines
3. WHO. Position Paper on Typhoid Vaccines, 2026 — Diagnosis and antimicrobial resistance. 4. CDC. Typhoid and Paratyphoid Fever, *Yellow Book*, 2026 Edition. 5. Médecins Sans Frontières. *Enteric (Typhoid and Paratyphoid) Fevers*, Clinical Guidelines.
Peer-Reviewed Journals with DOI
6. Wijedoru L, Mallett S, Parry CM. Rapid diagnostic tests for typhoid and paratyphoid fever. *Cochrane Database Syst Rev*. 2017. DOI: 10.1002/14651858.CD008892.pub2. 7. Seidman JC, et al. Use of Salmonella Typhi Hemolysin E and Lipopolysaccharide IgA to Identify Enteric Fever Cases, South Asia. *Emerg Infect Dis*. 2026;32(8):1221–1230. DOI: 10.3201/eid3208.250753.
রোগীর বিষয়ে ৫টি তথ্য প্রয়োজন
নিচের তথ্যগুলো দিলে সম্ভাব্য diagnosis আরও নির্দিষ্ট করা যাবে এবং patient-specific treatment plan তৈরি করা যাবে।
1. রোগীর এখন জ্বর আছে? থাকলে কতদিন ধরে এবং সর্বোচ্চ কত °F? 2. পেটব্যথা, ডায়রিয়া, কোষ্ঠকাঠিন্য বা বমি আছে? 3. আগে কোনো অ্যান্টিবায়োটিক খেয়েছেন? নাম ও কতদিন? 4. ওজন কত এবং রোগীর বর্তমানে দুর্বলতা বা মাথা ঘোরানো আছে? 5. এই রিপোর্টগুলো করার পর রোগী সুস্থ হয়েছেন, নাকি এখনও অসুস্থ?
বিশেষ করে বর্তমানে জ্বর আছে কি না এবং আগে অ্যান্টিবায়োটিক খেয়েছেন কি না—এই দুটি উত্তর রোগনির্ণয় ও চিকিৎসার সিদ্ধান্তে সবচেয়ে গুরুত্বপূর্ণ।