Report Attached:-
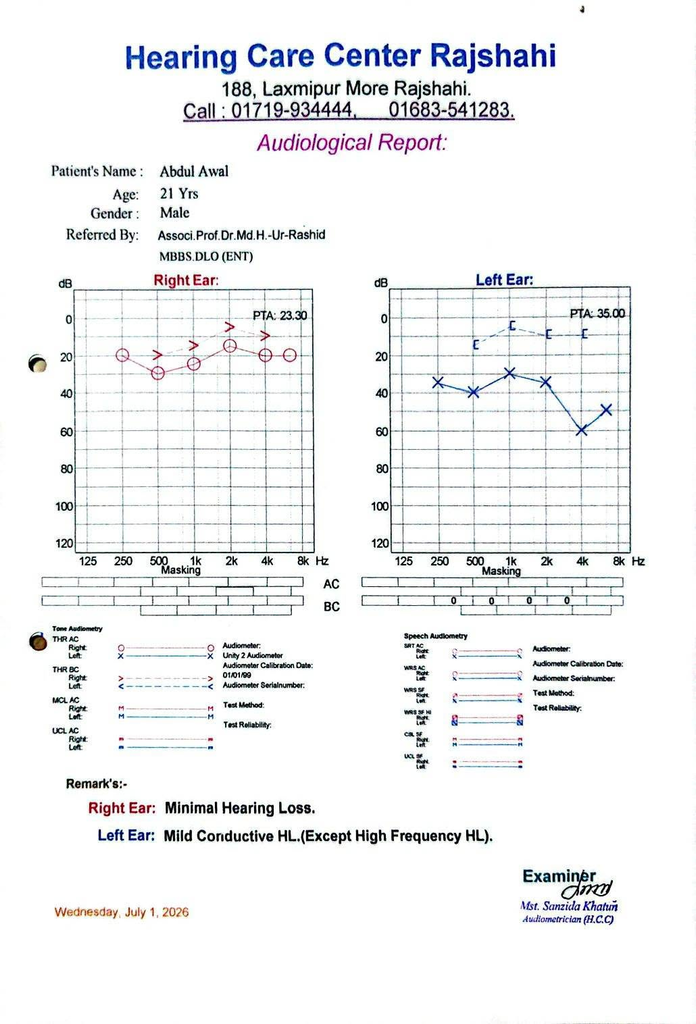
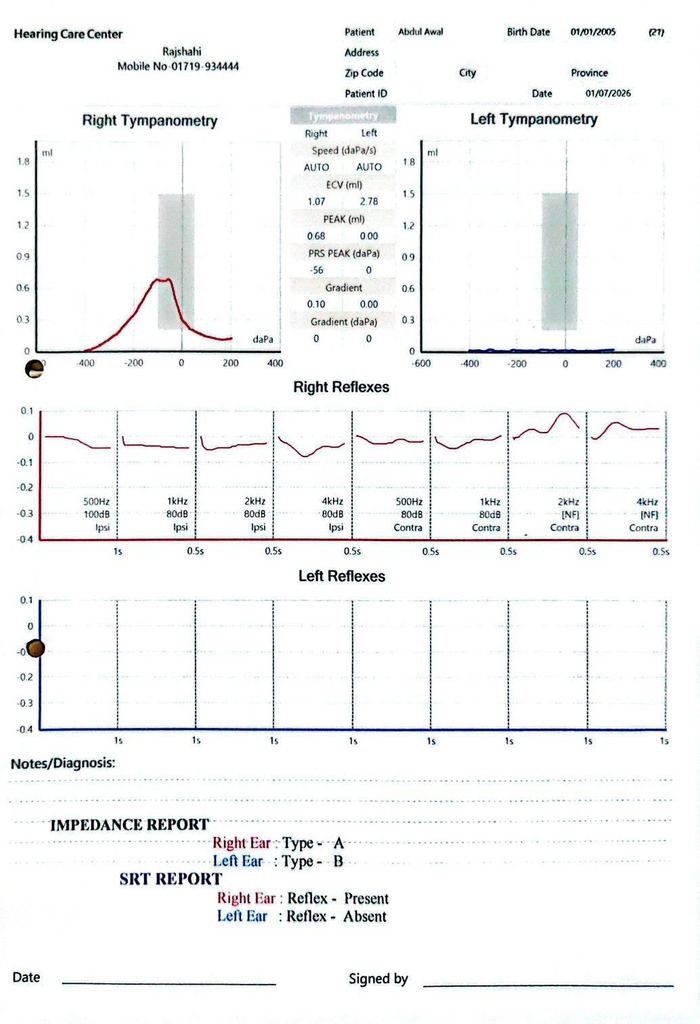
দুইটা রিপোর্ট একসাথে মিলিয়ে সবচেয়ে গুরুত্বপূর্ণ finding হলো—বাম কানে (Left ear) একটি স্পষ্ট conductive hearing loss আছে, এবং Type-B flat tympanogram + ECV 2.78 mL থাকার কারণে left tympanic membrane (eardrum) perforation strongly suspected। তবে perforation-এর exact size/site এবং এটা chronic otitis media কিনা—শুধু audiology report দিয়ে নিশ্চিত করা যাবে না; otoscopy/otomicroscopy দিয়ে confirm করতে হবে। ASHA অনুযায়ী adult-এ flat tympanogram-এর সাথে ECV >2.5 mL হলে perforated tympanic membrane বা patent ventilation tube strongly suggested হয়।
Report No. 1 — Pure Tone Audiometry (PTA)
| Finding | Report | Clinical বাংলা অর্থ |
| Right ear PTA | 23.3 dB HL | ডান কানে minimal/slight hearing loss—খুব সামান্য শ্রবণহানি |
| Right AC thresholds | প্রায় 15–30 dB | মোটামুটি near-normal/slight loss range |
| Left ear PTA | 35 dB HL | 🔴 বাম কানে mild hearing loss |
| Left AC | প্রায় 30–40 dB at 250–2000 Hz | মৃদু শ্রবণহানি |
| Left AC at 4 kHz | প্রায় 60 dB | 🔴 high-frequency-তে loss বেশি |
| Left AC at 8 kHz | প্রায় 50 dB | 🔴 high-frequency hearing reduction |
| Left BC | প্রায় 5–15 dB | Bone conduction প্রায় স্বাভাবিক → cochlear function largely preserved |
| Air–bone gap | উল্লেখযোগ্য | 🔴 Conductive component প্রমাণ করে |
Report-1 interpretation
Right Ear:
Minimal/slight hearing loss, PTA 23.3 dB. ডান কানের hearing clinically প্রায় স্বাভাবিকের কাছাকাছি।
Left Ear:
Mild conductive hearing loss (CHL), with greater loss at high frequencies.
এখানে সবচেয়ে গুরুত্বপূর্ণ বিষয় হচ্ছে:
Air conduction খারাপ কিন্তু bone conduction প্রায় normal → Conductive Hearing Loss.
অর্থাৎ সমস্যা primarily cochlea/8th nerve-এর নয়; বরং tympanic membrane বা middle-ear sound-conduction mechanism-এ।
Report-এ লেখা:
“Left Ear: Mild Conductive HL (Except High Frequency HL)”
এর clinical অর্থ: বাম কানে overall mild conductive hearing loss, তবে high-frequency অংশে hearing loss আরও বেশি। এটাকে শুধু এই graph দেখে “high-frequency sensorineural loss” বলা ঠিক হবে না, কারণ bone thresholds preserved আছে।
Confidence: 0.97 — Left conductive hearing loss.
Report No. 2 — Tympanometry / Impedance Audiometry
Right Ear
| Parameter | Value | Interpretation |
| ECV | 1.07 mL | Normal adult range |
| Peak compliance | 0.68 mL | Normal mobility |
| Peak pressure | −56 daPa | Acceptable/near-normal |
| Tympanogram | Type A | ✅ Normal middle-ear function |
| Acoustic reflex | Present | ✅ supportive of functioning middle-ear pathway |
Meaning
Right Type-A tympanogram = ডান কানের eardrum ও middle-ear pressure/mobility মোটামুটি স্বাভাবিক।
🔴 Left Ear — Abnormal findings
| Parameter | Value | Clinical meaning |
| ECV | 2.78 mL | 🔴 Abnormally/high ear-canal volume |
| Peak compliance | 0.00 mL | 🔴 measurable TM movement নেই |
| Tympanometric peak | নেই | 🔴 Flat curve |
| Tympanogram | Type B | 🔴 Abnormal |
| Acoustic reflex | Absent | 🔴 consistent with conductive middle-ear pathology |
সবচেয়ে গুরুত্বপূর্ণ finding
Type-B flat tympanogram + ECV 2.78 mL
Adult flat Type-B tympanogram-এ ECV >2.5 mL হলে tympanic membrane perforation অথবা patent tympanostomy tube strongly suggested হয়।
এই patient-এর ventilation tube-এর history দেওয়া হয়নি। তাই বর্তমান তথ্য অনুযায়ী:
Left tympanic membrane perforation is the leading explanation.
এটি Report-1-এর conductive hearing loss-এর সাথেও perfectly concordant:
TM perforation → sound transmission কমে → air conduction খারাপ → bone conduction preserved → air–bone gap → conductive hearing loss.
Confidence that left ear has middle-ear conductive pathology: 0.98.
Confidence that this represents TM perforation: ~0.88–0.92.
এটা 100% করতে otoscopy/otomicroscopy প্রয়োজন—tympanometry একা exact pathology নির্ধারণ করে না।
একটি ছোট technical point: দ্বিতীয় রিপোর্টের নিচে “SRT Report” লেখা থাকলেও “Reflex Present/Absent” আসলে acoustic reflex finding, true Speech Reception Threshold নয়।
আমার Working Clinical Diagnosis
English
Left-sided mild conductive hearing loss, most likely secondary to tympanic membrane perforation, with Type-B tympanogram and increased ear-canal volume; right ear minimal/slight hearing loss with normal Type-A tympanogram.
বাংলা
বাম কানের পর্দায় সম্ভাব্য ছিদ্র/মিডল-ইয়ার conductive pathology-এর কারণে মৃদু conductive hearing loss; ডান কানে খুব সামান্য hearing loss এবং middle-ear function স্বাভাবিক।
গুরুত্বপূর্ণ limitation
এই রিপোর্ট দেখে “CSOM/Chronic Suppurative Otitis Media” নিশ্চিত লিখব না, কারণ CSOM বলার জন্য chronic/recurrent otorrhea, otoscopic evidence of perforation এবং middle-ear status জানা দরকার।
Prescription-এ Dx কী লিখবেন?
বর্তমান রিপোর্টের ভিত্তিতে সবচেয়ে clinically defensible wording:
Dx: Left-sided mild conductive hearing loss with Type-B tympanogram — suspected left tympanic membrane perforation.
আরও সংক্ষিপ্তভাবে:
Dx: Left CHL, likely secondary to TM perforation.
Otoscopy-তে perforation confirm হলে
তখন লিখতে পারেন:
Dx: Left tympanic membrane perforation with mild conductive hearing loss.
বাংলায়:
বাম কানের পর্দায় ছিদ্রজনিত মৃদু কন্ডাক্টিভ শ্রবণহানি।
ICD-oriented documentation দরকার হলে, confirmed perforation-এ H72.92 — unspecified perforation of left tympanic membrane এবং hearing loss-এর জন্য appropriate unilateral conductive hearing-loss code ব্যবহার করা যায়। AAO-HNS-ও TM perforation-associated conductive hearing loss-কে recognized tympanoplasty indication হিসেবে উল্লেখ করে।
Differential Diagnosis
সবচেয়ে সম্ভাব্য থেকে নিচের দিকে:
- Left tympanic membrane perforation — highest probability.
- Chronic otitis media with TM perforation — শুধু history/otoscopy support করলে।
- Previous traumatic perforation.
- Patent ventilation tube — only if tube insertion history exists.
- Other middle-ear/ossicular pathology — lower probability.
Simple middle-ear effusion (OME) তুলনামূলক কম likely, কারণ OME-তে Type-B হলেও সাধারণত ECV normal থাকে; এখানে ECV 2.78 mL, অর্থাৎ perforation/open pathway বেশি suggestive।
এখন Doctor কী করবেন — Action Plan
প্রথমে ENT/Otolaryngology examination, preferably Otologist। Microscope/otoendoscope দিয়ে left TM-এর perforation আছে কিনা, size, position—central/marginal/attic, ear dry না wet, cholesteatoma আছে কিনা এবং ossicular status assess করতে হবে।
এরপর প্রয়োজন অনুযায়ী repeat PTA with proper masking + Speech Reception Threshold (SRT) + Word Recognition/Discrimination score করা ভালো। বর্তমান audiogram conductive pattern দেখাচ্ছে, কিন্তু surgical planning-এর আগে complete masked audiometry বেশি useful।
Additional investigations
- Otoscopy / otoendoscopy / otomicroscopy — essential
- Rinne & Weber test
- Repeat Pure-tone audiometry with masked AC/BC
- SRT + Word Recognition Score
- Persistent discharge থাকলে ear discharge culture & sensitivity
- HRCT temporal bone শুধুমাত্র cholesteatoma, ossicular erosion, chronic mastoid disease, unusual large conductive gap বা surgical planning-এর indication থাকলে; uncomplicated perforation-এ routine CT প্রয়োজন নেই।
Treatment Plan
যদি ear dry থাকে এবং active infection না থাকে, routine antibiotic প্রয়োজন নেই। Ear dry রাখতে হবে, swimming/water entry বন্ধ করতে হবে এবং cotton bud/ear instrumentation এড়াতে হবে।
যদি active otorrhea/purulent discharge থাকে, ENT examination/aural toilet-এর পর appropriate topical therapy, সাধারণত non-ototoxic fluoroquinolone-based drops বিবেচনা করা যায়। Perforated TM-তে aminoglycoside-containing drops দীর্ঘদিন indiscriminately ব্যবহার করা উচিত নয়, কারণ potential ototoxicity আছে। CSOM-এ topical versus systemic antimicrobial evidence এখনও limited/variable।
Operation কি লাগতেই হবে?
এখনই audiogram দেখে surgery mandatory বলা যাবে না।
Acute/new perforation হলে অনেক ক্ষেত্রে spontaneous healing হতে পারে। কিন্তু perforation/hearing loss >3 months persistent, recurrent infection, significant conductive hearing loss, অথবা water exposure-এর কারণে recurrent problem হলে myringoplasty/Type-I tympanoplasty বিবেচনা করা হয়। AAO-HNS clinical indicators-এ persistent perforation বা hearing loss >3 months এবং TM-perforation-related conductive hearing loss surgical indications হিসেবে listed আছে।
কাকে Refer করবেন?
ENT / Otolaryngology → preferably an Otologist / Ear surgeon.
Referral note এভাবে দিতে পারেন:
21-year-old male with asymmetrical hearing loss. PTA shows right PTA 23.3 dB (minimal/slight loss) and left PTA 35 dB with significant air–bone gap consistent with mild conductive hearing loss and high-frequency worsening. Tympanometry: right Type-A; left Type-B flat tympanogram with ECV 2.78 mL and absent acoustic reflex, suspicious for left tympanic membrane perforation. Kindly evaluate by otomicroscopy/otoendoscopy for TM perforation, middle-ear/ossicular pathology and advise definitive management including suitability for myringoplasty/tympanoplasty if persistent.
Overview / Summary
Final working diagnosis:
Left-sided mild conductive hearing loss, most likely due to left tympanic membrane perforation.
Right ear shows only minimal/slight hearing reduction with normal Type-A tympanometry.
Overall diagnostic confidence
- Left conductive hearing loss: 0.97
- Left middle-ear/TM pathology: 0.98
- TM perforation specifically: 0.90
- “CSOM” as exact diagnosis: <0.60 without history + otoscopy, তাই এখনই CSOM লেখা উচিত নয়।
Actionable Plan
ENT/otologist → otomicroscopy → confirm perforation → complete masked audiometry/SRT/WRS → keep ear dry → treat only active infection if present → reassess. Persistent confirmed perforation with conductive loss/recurrent infections → myringoplasty/tympanoplasty assessment।
Prescription-এর জন্য আমার preferred final Dx
Dx: Left-sided mild conductive hearing loss secondary to suspected tympanic membrane perforation (Type-B tympanogram with increased ECV).
Otoscopy-তে confirm হলে:
Dx: Left tympanic membrane perforation with mild conductive hearing loss.
References
Textbook: Dhingra PL, Dhingra S. Diseases of Ear, Nose and Throat & Head and Neck Surgery, 8th ed. Chapters on assessment of hearing, conductive hearing loss, tympanic membrane perforation and chronic otitis media. Page numbers vary by printing.
ASHA: Tympanometry—flat Type-B tympanogram with abnormally large adult ear-canal volume (>2.5 cm³) suggests TM perforation or patent pressure-equalization tube.
AAO-HNS: Clinical Indicators: Tympanoplasty—conductive hearing loss due to TM perforation and perforation/hearing loss persistent >3 months are accepted indications for consideration of tympanoplasty.
Peer-reviewed guideline: Rosenfeld RM, et al. Clinical Practice Guideline: Otitis Media with Effusion (Update). Otolaryngol Head Neck Surg. 2016;154(Suppl):S1–S41. DOI: 10.1177/0194599815623467. Type-B tympanogram with high ear-canal volume indicates non-intact TM/patent tube.
Cochrane Review: Topical versus systemic antibiotics for chronic suppurative otitis media. 2025. DOI: 10.1002/14651858.CD013053.pub3.
rogi ke ki bolbo clinically babe gusie bolbo
রোগীকে খুব বেশি technical শব্দ না বলে, clinically এভাবে গুছিয়ে বলতে পারেন:
“আপনার hearing test-এ দেখা যাচ্ছে ডান কানের hearing প্রায় স্বাভাবিকের কাছাকাছি। বাম কানে হালকা মাত্রার hearing loss আছে। তবে এটি মূলত কানের নার্ভের সমস্যা মনে হচ্ছে না; কানের পর্দা বা middle ear দিয়ে শব্দ যাওয়ার পথে সমস্যা হচ্ছে—এটাকে conductive hearing loss বলে।
বাম কানের আরেকটি পরীক্ষায় Type-B pattern এবং ear-canal volume বেশি পাওয়া গেছে। এই ধরনের রিপোর্টে কানের পর্দায় ছোট বা বড় ছিদ্র থাকার সম্ভাবনা থাকে। তবে শুধু রিপোর্ট দিয়ে ছিদ্র নিশ্চিত করা যায় না; ENT ডাক্তার কানের ভেতর otoscope/microscope দিয়ে দেখলে নিশ্চিত হওয়া যাবে।
এখনই ভয় পাওয়ার বা অপারেশন লাগবেই এমন কিছু বলা যাচ্ছে না। আগে ENT specialist দিয়ে কানের পর্দা পরীক্ষা করতে হবে। যদি ছিদ্র নতুন হয়, অনেক ক্ষেত্রে নিজে থেকেই শুকিয়ে/বন্ধ হয়ে যেতে পারে। কিন্তু যদি দীর্ঘদিনের ছিদ্র থাকে, বারবার পানি/পুঁজ পড়ে বা hearing কম থাকে, তখন পরবর্তীতে পর্দা মেরামতের operation—myringoplasty/tympanoplasty—লাগতে পারে।
এখন সবচেয়ে গুরুত্বপূর্ণ হলো কানে পানি ঢুকতে না দেওয়া, কটন বাড/কোনো কিছু কানের ভেতরে না দেওয়া এবং নিজের ইচ্ছায় ear drop না ব্যবহার করা। যদি কান দিয়ে পুঁজ বা পানি পড়ে, ব্যথা হয়, মাথা ঘোরে বা hearing হঠাৎ আরও কমে যায়, দ্রুত ENT ডাক্তার দেখাবেন।”
রোগী যদি জিজ্ঞেস করে, “আমার আসলে কী হয়েছে?”
সংক্ষেপে বলবেন:
“বাম কানে হালকা conductive hearing loss হয়েছে এবং কানের পর্দায় ছিদ্র থাকার সম্ভাবনা আছে। ENT examination করলে এটা নিশ্চিত হওয়া যাবে।”
“নার্ভ নষ্ট হয়ে গেছে?” জিজ্ঞেস করলে
বলবেন:
“বর্তমান test অনুযায়ী বাম কানের inner-ear/nerve hearing তুলনামূলকভাবে preserved আছে। প্রধান সমস্যা sound conduction বা কানের পর্দা/middle-ear side-এ মনে হচ্ছে।”
“Operation লাগবে?” জিজ্ঞেস করলে
বলবেন:
“এখনই operation লাগবে বলা যাচ্ছে না। আগে কানের পর্দা দেখে ছিদ্র আছে কিনা, কত বড়, কতদিনের এবং কান dry না infected—এসব দেখতে হবে। Persistent perforation ও hearing problem থাকলে পরে operation বিবেচনা করা হয়।”
Prescription-এ clinical diagnosis
Dx: Left mild conductive hearing loss with suspected tympanic membrane perforation.
Otoscopy-তে ছিদ্র নিশ্চিত হলে:
Dx: Left tympanic membrane perforation with mild conductive hearing loss.
Confidence: Conductive hearing loss 0.97; TM perforation suspicion ~0.90, কিন্তু perforation confirm করতে otoscopy/otomicroscopy প্রয়োজন।
reffer note ki dibo
Prescription-এ Refer Note এভাবে লিখতে পারেন:
Referred to ENT/Otology specialist for evaluation of left-sided mild conductive hearing loss. PTA shows left PTA ~35 dB with significant air–bone gap. Tympanometry shows Type-B curve with increased ECV (2.78 mL) and absent acoustic reflex, suggestive of left tympanic membrane perforation/middle-ear pathology. Kindly perform otoscopic/otomicroscopic evaluation and advise definitive management, including suitability for myringoplasty/tympanoplasty if indicated.
Short prescription version
Refer to ENT/Otologist for evaluation of left mild CHL with Type-B tympanogram and increased ECV—suspected TM perforation. Please assess by otomicroscopy and advise further management.
আরও ছোট করে লিখতে চাইলে
ENT referral: Left mild CHL with suspected TM perforation; kindly evaluate and manage accordingly.
বাংলা অর্থ: বাম কানে mild conductive hearing loss আছে এবং রিপোর্টে কানের পর্দায় ছিদ্র থাকার সন্দেহ হচ্ছে। ENT/Otology specialist-কে otoscopy/otomicroscopy করে নিশ্চিত diagnosis ও প্রয়োজন হলে myringoplasty/tympanoplasty-এর suitability মূল্যায়নের জন্য refer করা হলো।
সবচেয়ে clinically safe wording হলো “suspected TM perforation”, কারণ audiology report strongly suggestive হলেও direct otoscopic examination ছাড়া perforation confirmed লেখা উচিত নয়।
Md.Rafiqul Islam Lipu.