(Prescription+Report)attached




Report analysis:-
রিপোর্টগুলো একসাথে দেখে সবচেয়ে গুরুত্বপূর্ণ বিষয় হলো—এগুলো একই সময়ের রিপোর্ট নয়: lumbar X-ray ও knee MRI 2024 সালের, CBC 2025 সালের, urine R/E 2026 সালের। তাই পুরোনো MRI/X-ray-এর finding এখনো active আছে ধরে নেওয়া যাবে না; current clinical examination দরকার। নিচে report-based working clinical diagnosis দিচ্ছি।
1. Final Working Diagnosis — কী লিখবেন
| Diagnosis | Confidence | Clinical interpretation |
| Right knee partial ACL tear with lateral femoral condyle bone contusion/marrow edema + mild joint effusion | 0.99 | MRI-তে সরাসরি documented |
| Early lumbar spondylosis / degenerative lumbar disc disease, especially L4–L5 | 0.95 | Osteophyte + disc-space loss |
| Bilateral SI-joint marginal sclerosis — etiology uncertain | 0.85 finding; <0.40 for inflammatory sacroiliitis | sclerosis আছে, কিন্তু শুধু এটুকু দিয়ে sacroiliitis/axSpA বলা যাবে না |
| Mild anemia, normocytic with hypochromic indices; possible early iron deficiency | anemia 0.97, IDA 0.65 | Hb 11.5 + low MCH/MCHC; ferritin ছাড়া IDA confirm নয় |
| Raised ESR — nonspecific inflammatory marker elevation | 0.99 | ESR 42 mm/hr |
| Urine R/E essentially normal; no laboratory evidence of UTI | 0.98 | pyuria/hematuria/proteinuria নেই |
Prescription-এর concise Dx:
Dx: MRI-confirmed partial ACL tear, right knee with lateral femoral condyle bone contusion and mild joint effusion (old MRI, 2024); early degenerative changes of lumbar spine/L4–L5 spondylosis; mild anemia—?early iron deficiency; raised ESR—cause under evaluation.
আমি এই report থেকে complete ACL tear, UTI, বা ankylosing spondylitis/sacroiliitis final diagnosis লিখব না।
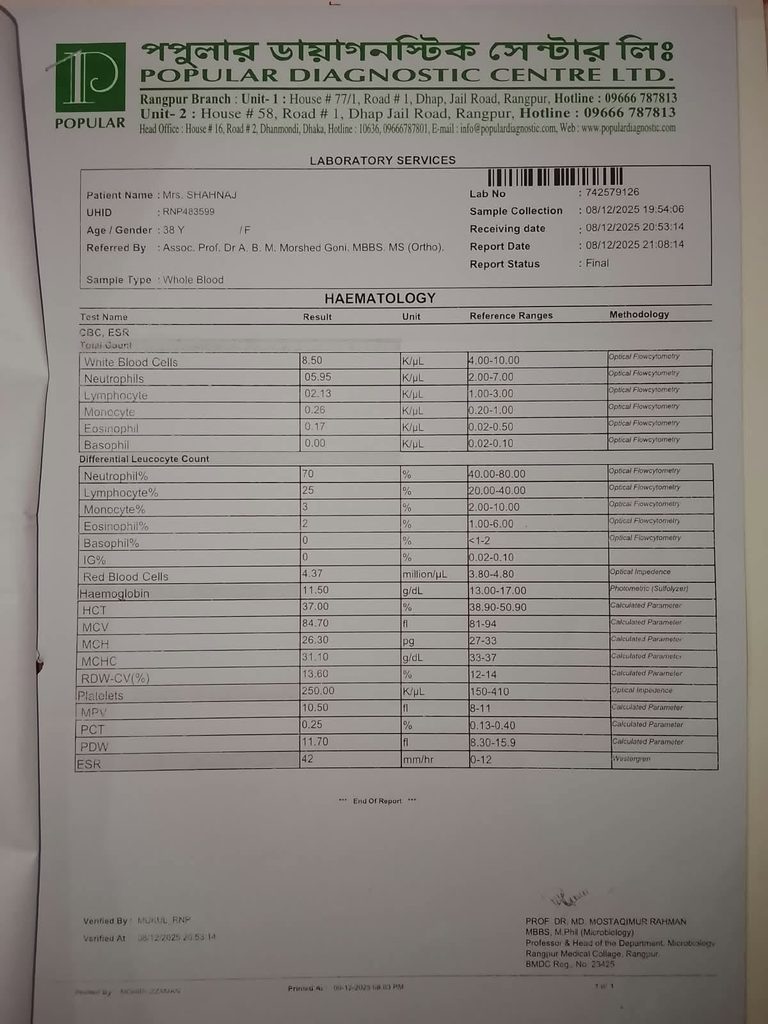
2. CBC / ESR Report
🔴 Abnormal findings
| Test | Result | Meaning | বাংলা clinical meaning |
| Hemoglobin | 11.5 g/dL ↓ | Mild anemia | হালকা রক্তস্বল্পতা |
| MCH | 26.3 pg ↓ | Low Hb per RBC | RBC-এর ভেতরে Hb কিছুটা কম |
| MCHC | 31.1 g/dL ↓ | Hypochromia | RBC তুলনামূলক ফ্যাকাশে/কম Hb-containing |
| ESR | 42 mm/hr ↑ | Nonspecific inflammation marker | শরীরে inflammation/infection/anaemiaসহ বিভিন্ন কারণে বাড়তে পারে |
| HCT | 37% | Lab-flagged low | তবে 38 বছর বয়সী নারীর ক্ষেত্রে borderline/near-normal হতে পারে |
| Basophil absolute | 0.00 | Low versus printed range | একা এর clinical significance সাধারণত নেই |
এই patient female; report-এ Hb reference 13–17 g/dL দেওয়া হয়েছে, যা female-এর জন্য উপযুক্ত reference বলে মনে হচ্ছে না। WHO অনুযায়ী non-pregnant adult woman-এর Hb <12 g/dL হলে anemia এবং 11.0–11.9 g/dL mild anemia range-এর মধ্যে পড়ে। তাই Hb 11.5 = mild anemia।
🟢 Normal / reassuring findings
WBC 8.5, neutrophils 70%, lymphocytes 25%, platelet 250,000/µL, RBC 4.37 million/µL, MCV 84.7 fL, RDW 13.6%—major abnormality নেই।
Clinical interpretation
Patternটি mild normocytic anemia with hypochromic indices। অর্থাৎ MCV এখনো normal, কিন্তু MCH/MCHC কম। এটি early iron deficiency-তে হতে পারে, আবার inflammatory anemia/mixed anemia-তেও হতে পারে।
Ferritin ছাড়া “Iron deficiency anemia” নিশ্চিত লিখব না। Serum ferritin iron deficiency নির্ণয়ের সবচেয়ে useful initial marker; inflammation থাকলে transferrin saturation সহ interpret করা ভালো।
এখন investigation
Repeat current CBC করা উচিত, কারণ reportটি December 2025-এর। সাথে:
- Serum ferritin
- Serum iron, TIBC + transferrin saturation
- CRP + repeat ESR
- Peripheral blood film
- Reticulocyte count
- Menstrual history—menorrhagia আছে কি না
- যদি ferritin/iron deficiency confirm হয়: dietary history, menstrual loss, এবং প্রয়োজন অনুযায়ী coeliac screening/GI evaluation
Confirmed IDA-তে oral ferrous sulfate/fumarate/gluconate commonly first-line; response কয়েক সপ্তাহের মধ্যে monitor করা হয়।
3. MRI Right Knee — সবচেয়ে significant report
🔴 Finding 1: Partial ACL tear
Report:
“Outline of ACL could not be well delineated… hyperintense signal… sparing some fibres.”
বাংলা: ACL ligament-এর সব fibre ছিঁড়ে যায়নি; কিছু fibre intact রেখে আংশিক ছিঁড়ে গেছে — Partial ACL tear।
Confidence: 0.99.
🔴 Finding 2: Lateral femoral condyle bone contusion / marrow edema
“STIR hyperintensity… lateral condyle of femur suggesting bony contusion/marrow oedema.”
বাংলা: হাঁটুর femur-এর বাইরের অংশে হাড়ের ভেতরে bruising/আঘাতজনিত swelling ছিল।
এটি fracture বলা হয়নি।
🔴 Finding 3: Mild joint effusion
Suprapatellar/retropatellar region-এ fluid collection রয়েছে।
বাংলা: হাঁটুর joint-এর ভিতরে অল্প fluid/swelling জমেছিল।
🟢 Important normal findings
Menisci: normal
PCL: no signal abnormality
Medial & lateral collateral ligaments: normal
Quadriceps tendon: normal
Patellar tendon: intact
Hoffa’s fat pad: normal
অর্থাৎ MRI report অনুযায়ী meniscus tear নেই এবং major associated ligament tear নেই।
একটি গুরুত্বপূর্ণ limitation
MRIটি November 2024-এর। Bone marrow edema ও effusion 2024-এ ছিল—2026-এ এখনো আছে, এটা এই report থেকে বলা যাবে না। একইভাবে partial ACL এখন functionally stable নাকি unstable হয়েছে সেটিও MRI alone দিয়ে বর্তমান সময়ে বলা যাবে না।
AAOS ACL guideline অনুযায়ী treatment decision-এ current history, knee stability, activity level এবং focused musculoskeletal examination গুরুত্বপূর্ণ।
4. Right knee-এর এখন Clinical Examination
Orthopaedic examination-এ specifically করতে হবে:
Lachman test, anterior drawer, pivot-shift, varus/valgus stability, knee ROM, joint-line tenderness, effusion এবং quadriceps strength।
যদি patient বলেন:
- হাঁটু বারবার giving way / buckling
- দৌড়ানো বা ঘোরার সময় instability
- recurrent swelling
- sport বা heavy work করতে পারছেন না
তাহলে clinically significant ACL insufficiency হওয়ার সম্ভাবনা বেশি।
Treatment plan
বর্তমান knee stable এবং recurrent giving-way না থাকলে structured physiotherapy/rehabilitation first যুক্তিযুক্ত: ROM restoration, quadriceps–hamstring strengthening, hip/core strengthening, balance/proprioception ও neuromuscular training। Pivoting/twisting activity initially avoid করা উচিত। AAOS অনুযায়ী treatment activity level ও instability-এর ওপর নির্ভর করে; কিছু রোগী rehabilitation-এর পর যথেষ্ট stable থাকেন এবং surgery প্রয়োজন হয় না।
Pain/swelling থাকলে contraindication না থাকলে short-course NSAID বিবেচনা করা যায়, তবে renal disease, peptic ulcer, anticoagulant use, pregnancy, uncontrolled hypertension ইত্যাদি আগে দেখতে হবে।
ACL Reconstruction কখন consider করব?
বর্তমানে যদি objective instability + recurrent giving-way, high-demand/pivoting activity, বা adequate rehabilitation সত্ত্বেও functional limitation থাকে—তাহলে knee/sports orthopaedic surgeon-এর ACL reconstruction assessment প্রয়োজন।
MRI-তে “partial ACL tear” লেখা আছে বলেই automatic surgery নয়। Conversely, repeatedly unstable knee ignore করাও উচিত নয়। AAOS-এ reconstruction নির্বাচিত patients-এ future meniscal/cartilage injury কমানোর জন্য বিবেচিত হয়।
5. Lumbar Spine X-ray
🔴 Osteophytes at L4–L5
Osteophytes = bone spurs / অস্থির বাড়তি ক্ষুদ্র projection।
এটি degenerative change বা lumbar spondylosis-এর feature।
🔴 “Disc spaces are not maintained”
বাংলা: vertebra-এর মাঝের disc-space স্বাভাবিক height বজায় রাখেনি—disc degeneration/narrowing বোঝাচ্ছে।
Report exact level specify করেনি, তাই “L4–L5 disc narrowing” confidently লেখা ঠিক হবে না; L4–L5-তে osteophyte নিশ্চিত।
🔴 Bilateral SI-joint marginal sclerosis
Sclerosis = joint margin-এর হাড় তুলনামূলক ঘন/সাদা হয়ে যাওয়া।
এটি degenerative/mechanical change হতে পারে; অন্যদিকে inflammatory sacroiliac pathology differential-এ থাকে।
কিন্তু report sacroiliitis বলেনি।
🟢 Lumbar lordosis maintained
বাংলা: কোমরের স্বাভাবিক curvature বজায় আছে।
Final X-ray diagnosis
Early lumbar spondylosis / degenerative changes of lumbar spine. Confidence 0.95.
6. SI-joint sclerosis + ESR 42 — এখানে কী miss করা উচিত নয়?
এটাই report-এর গুরুত্বপূর্ণ clinical cross-check।
Patient 38 years old এবং X-ray-তে bilateral SI marginal sclerosis আছে। যদি back pain age <45-এ শুরু, >3 months থাকে এবং সাথে morning stiffness/night pain, buttock pain, movement-এ improvement, NSAID-এ দ্রুত improvement, psoriasis, uveitis, IBD বা family history থাকে—তাহলে axial spondyloarthritis evaluate করা উচিত। NICE অনুসারে plain X-ray inconclusive হলেও clinical suspicion থাকলে dedicated MRI SI joints/inflammatory back-pain protocol এবং প্রয়োজন অনুযায়ী HLA-B27 করা যায়।
কিন্তু এই রিপোর্টগুলো দিয়ে ankylosing spondylitis diagnosis দেওয়া যাবে না। ESR 42-ও specific নয়।
Inflammatory sacroiliitis confidence from current reports alone: <0.40 → আমি diagnosis হিসেবে reject করছি, শুধু differential হিসেবে রাখছি।
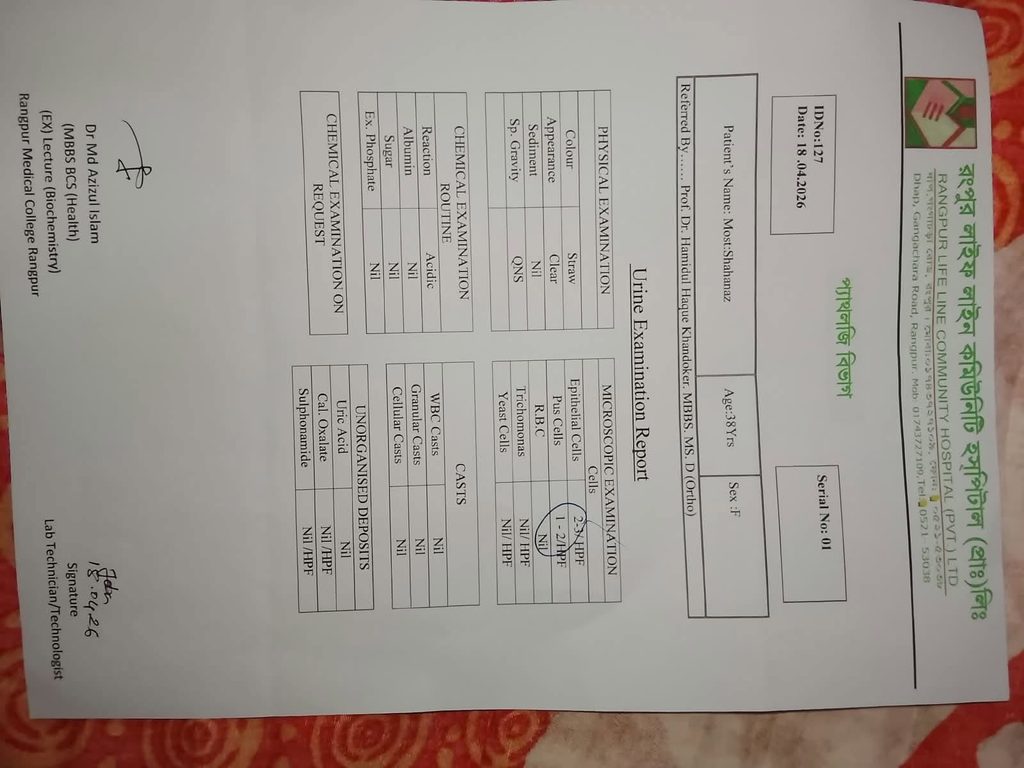
7. Urine Examination
এটি মূলত normal urine R/E।
| Finding | Interpretation |
| Colour: Straw | স্বাভাবিক |
| Appearance: Clear | স্বাভাবিক |
| Albumin: Nil | Proteinuria নেই |
| Sugar: Nil | Glycosuria নেই |
| RBC: Nil | Hematuria নেই |
| Pus cell: 1–2/HPF | significant pyuria নয় |
| Epithelial cell: 2–3/HPF | acceptable |
| Casts: Nil | renal cast নেই |
| Crystals: Nil | উল্লেখযোগ্য crystal নেই |
| Trichomonas/yeast: Nil | negative |
| Specific gravity: QNS | parameterটি adequately measured হয়নি |
Conclusion: No evidence of UTI/proteinuria/hematuria. Confidence 0.98.
এই urine report-এর জন্য antibiotic প্রয়োজনের কোনো evidence নেই।
8. Differential Diagnosis
বর্তমান তথ্য থেকে তিনটি differential area মাথায় রাখব:
Anemia: early iron deficiency > anemia of inflammation > other causes. Thalassemia trait currently less characteristic because MCV normal এবং RBC count elevated নয়, তবে iron study ছাড়া final etiology নয়।
Low back/SI findings: mechanical degenerative spondylosis সবচেয়ে likely; inflammatory axial spondyloarthritis only if supportive clinical features থাকে।
Knee: MRI-confirmed partial ACL injury; current chronic ACL insufficiency আছে কি না physical examination ছাড়া বলা যাবে না।
9. Doctor এখন কী Action নেবে
Priority 1 — Knee
Orthopaedic Surgeon — Knee/Sports Medicine referral। Current Lachman/pivot-shift ও functional instability assessment → structured rehabilitation বনাম ACL reconstruction decision।
Priority 2 — Blood
Repeat CBC + ferritin + iron/TIBC/TSAT + CRP/ESR। Heavy menstrual bleeding history অবশ্যই নিন। Iron deficiency confirm হলে cause identify করে iron replacement।
Priority 3 — Back
Neurological examination: power, reflexes, sensation, SLR। Mechanical pattern হলে physiotherapy/exercise এবং activity continuation first-line; routine repeat imaging প্রয়োজন নেই যদি management change না করে। NSAID ব্যবহার করলে lowest effective dose ও shortest duration recommended।
Inflammatory back-pain features থাকলে Rheumatology referral + HLA-B27/CRP ± dedicated MRI SI joints।
আমার report-based final working Dx:
Primary Dx:
Right knee partial ACL tear with lateral femoral condyle bone contusion/marrow edema and mild knee joint effusion.
Confidence: 99% — MRI report-এ সরাসরি documented।
সাথে আরও আছে:
- Early degenerative changes / lumbar spondylosis — Confidence 95%
- Mild anemia, likely early iron deficiency — anemia 97%, iron deficiency cause হিসেবে 65%; ferritin দরকার
- Raised ESR (42 mm/hr), cause undetermined — এটি diagnosis নয়, nonspecific finding।
Prescription-এ short Dx
Dx: Partial ACL tear, Right Knee with mild joint effusion & lateral femoral condyle bone contusion.
যদি মূল complaint right knee pain/instability হয়, এটাকেই আমি main diagnosis লিখব।
10. Prescription-এ Referral Note কী লিখবেন
Orthopaedic referral:
Referral to Orthopaedic Surgeon (Knee/Sports Medicine):
38-year-old female with right knee pain ± instability. Previous MRI right knee (02-11-2024) showed partial ACL tear with lateral femoral condyle bone contusion/marrow edema and mild joint effusion; menisci, PCL and collateral ligaments intact. Kindly assess current ACL stability clinically (Lachman/pivot-shift), functional instability and advise regarding structured rehabilitation versus ACL reconstruction if indicated.
Back pain যদি inflammatory nature-এর হয়, আলাদা note:
Referral to Rheumatology:
Young female with chronic low-back pain, X-ray showing bilateral SI-joint marginal sclerosis and previous raised ESR (42 mm/hr). Kindly evaluate for inflammatory back pain/axial spondyloarthritis; consider CRP, HLA-B27 and MRI SI joints if clinically indicated.
জরুরি referral কখন
বর্তমানে new bowel/bladder dysfunction, saddle anesthesia, progressive leg weakness, fever with severe back pain, hot/red severely swollen knee, acute inability to bear weight, বা significant calf swelling থাকলে routine appointment না করে urgent assessment দরকার।
Overview / Summary
সবচেয়ে নিশ্চিত major pathology হলো old MRI-confirmed right partial ACL tear, সাথে 당시 lateral femoral condyle bone contusion ও mild effusion। দ্বিতীয়টি early lumbar degenerative spondylosis। CBC-তে mild anemia with hypochromic indices এবং ESR 42 elevated; iron deficiency probable হলেও ferritin ছাড়া final নয়। Urine examination essentially normal।
Overall report interpretation confidence: 0.94। বর্তমান ACL functional status এবং SI-joint inflammatory disease সম্পর্কে confidence কম, কারণ current symptoms ও physical examination নেই।
Actionable Plan / Steps
আজকের practical plan: current knee stability examination → Orthopaedic Knee/Sports referral; repeat CBC + ferritin + iron profile + CRP/ESR; back pain-এর inflammatory features actively screen করুন; positive হলে Rheumatology + HLA-B27/MRI SI joint; otherwise mechanical lumbar degeneration হিসেবে exercise/physiotherapy-based treatment দিন।
Reference List
Textbooks: Apley & Solomon’s System of Orthopaedics and Trauma, 10th ed.—knee ligament injuries and degenerative spine disorders; Harrison’s Principles of Internal Medicine, 22nd ed.—approach to anemia/iron deficiency; Bailey & Love’s Short Practice of Surgery, 27th ed.—orthopaedic assessment and musculoskeletal disorders.
Guidelines: AAOS, Management of Anterior Cruciate Ligament Injuries, 2022. NICE NG59, Low Back Pain and Sciatica in Over 16s, updated 2020. NICE NG65, Spondyloarthritis in Over 16s: Diagnosis and Management. WHO, Guideline on haemoglobin cutoffs to define anaemia, 2024. BSG, Management of Iron Deficiency Anaemia in Adults, reviewed 2026.
Peer-reviewed / DOI: Brophy RH, Lowry KJ. J Am Acad Orthop Surg. 2023;31:531–537. doi:10.5435/JAAOS-D-22-01020. Snook J, et al. Gut. 2021;70:2030–2051. doi:10.1136/gutjnl-2021-325210. Foster NE, et al. Lancet. 2018;391:2368–2383. doi:10.1016/S0140-6736(18)30489-6.
Prescription Medicine Analysis:-
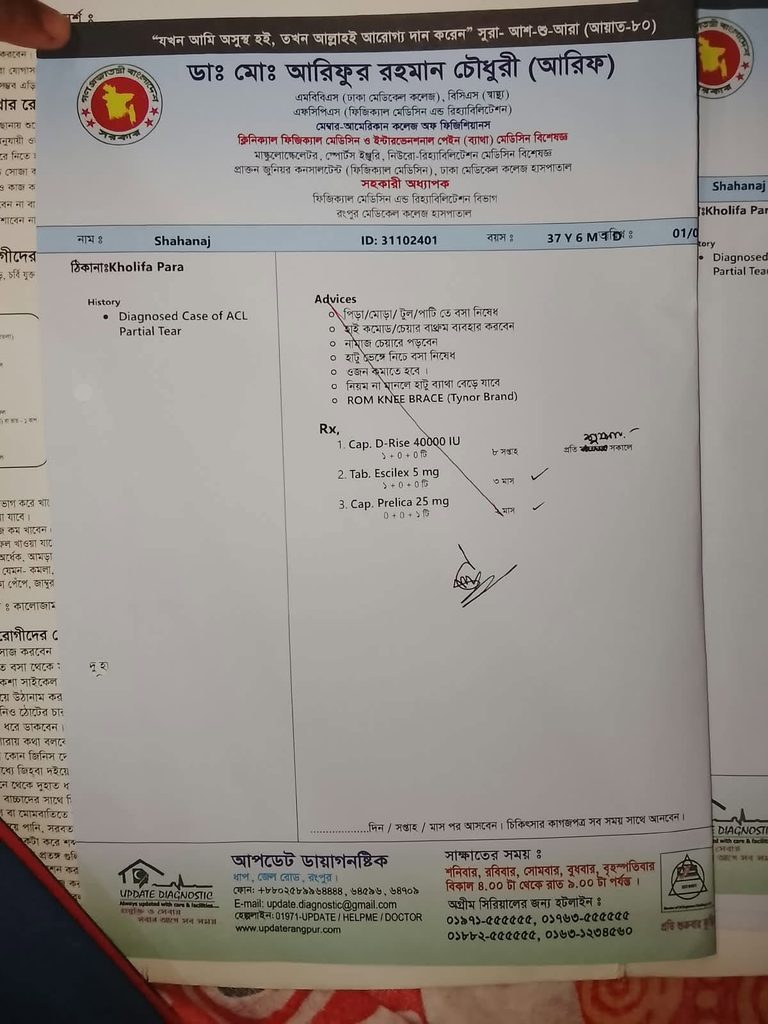
তিনটা prescription আলাদা করে মিলিয়ে দেখেছি। আগে গুরুত্বপূর্ণ clarification: ১ নম্বর এবং ৩ নম্বর একই prescription-এর দুইটি ছবি—তারিখ, diagnosis, advice এবং পাঁচটি drug একই। ২ নম্বরটি আগের/আলাদা follow-up prescription।
১ নম্বর Prescription — 07/08/2025
C/C, O/E, History, Investigation, Dx
| বিষয় | Prescription-এ যা আছে | আমার reading |
| C/C – Chief Complaint | আলাদা করে C/C লেখা নেই | কিছু handwritten complaint আছে, কিন্তু সম্পূর্ণ নির্ভুলভাবে পড়া যাচ্ছে না—অনুমান করে লিখছি না |
| O/E – On Examination | পরিষ্কারভাবে কোনো O/E documented নেই | Lachman/anterior drawer/ROM ইত্যাদির result লেখা দেখা যাচ্ছে না |
| History | Diagnosed case of ACL Partial Tear + OA Knee | ACL partial tear = ACL-এর আংশিক ছিঁড়ে যাওয়া; OA knee = হাঁটুর ক্ষয়জনিত osteoarthritis |
| Investigation | handwritten অংশে “X-ray Dorsal spine B/V” এবং সম্ভবত “X-ray both knee joint AP/Lateral in standing position” | দ্বিতীয়টির reading confidence ≈ 0.75, handwriting পুরোপুরি পরিষ্কার নয় |
| Doctor’s Dx | ACL Partial Tear + OA Knee | ACL diagnosis strongly supported; OA Knee বর্তমান দেওয়া report দিয়ে independently confirm করা যাচ্ছে না |
Advice
Doctor মূলত deep knee flexion ও mechanical loading কমাতে বলেছেন:
- পিঁড়া/মোড়া/টুল/পাটিতে বসা নিষেধ।
- High commode/chair ব্যবহার।
- নামাজ চেয়ারে পড়া।
- হাঁটু ভেঙে নিচে/squatting position-এ বসা নিষেধ।
- ওজন কমাতে হবে।
- নিয়ম না মানলে হাঁটুর ব্যথা বাড়তে পারে।
- ROM Knee Brace (Tynor) ব্যবহার।
এগুলো OA/ACL-related knee pain-এর conservative management-এর সাথে broadly compatible; তবে ACL injury-তে মূল বিষয় হলো structured rehabilitation + quadriceps/hamstring strengthening + stability assessment, শুধু brace/medicine নয়। AAOS-এর ACL guideline-ও treatment decision-এ function, instability, rehabilitation এবং activity level-এর গুরুত্ব দেয়।
Drugs — ১ নম্বর Prescription
1. Cap. Indomet 25 mg — 1+0+1, 20 days, after food
Generic: Indomethacin 25 mg
Company: Opsonin Pharma
MedEx Therapeutic Class: Drugs for Osteoarthritis; Drugs used for Rheumatoid Arthritis; NSAIDs
Pharmacological class: Non-selective NSAID / COX inhibitor.
এই patient-এ উদ্দেশ্য: knee/OA-associated pain ও inflammation কমানো। এটি ACL ligament জোড়া লাগায় না; symptomatic pain relief দেয়।
Used in: osteoarthritis, rheumatoid arthritis, ankylosing spondylitis, acute gout, bursitis/synovitis/tendinitis। MedEx-এ unit price ৳1, strip ৳20; একই brand-এর 75 mg SR-ও আছে।
Indomet 25 mg — MedEx
Bangladesh alternatives include Imet, Indocap, Insaid, Reumacap ইত্যাদি।
2. Tab. Relentus 2 mg — 1+1+1, 20 days, after food
Generic: Tizanidine Hydrochloride 2 mg
Company: Beximco Pharmaceuticals
MedEx Therapeutic Class: Centrally acting Skeletal Muscle Relaxants
Pharmacological class: Central α₂-adrenergic agonist muscle relaxant.
এই patient-এ সম্ভাব্য উদ্দেশ্য: associated back/paraspinal or peri-knee muscle spasm কমানো। Isolated ACL tear-এর specific treatment নয়।
Painful spinal muscle spasm ও neurological spasticity-তে ব্যবহৃত হয়। Unit ৳8, strip ৳80।
Relentus 2 mg — MedEx
Alternatives: Sirdalud, Tizadin, Tizalud, Tizan ইত্যাদি।
3. Tab. Exium MUPS 20 mg — 1+0+1, 20 days, before food
Generic: Esomeprazole 20 mg
Company: Radiant Pharmaceuticals
MedEx Therapeutic Class: Proton Pump Inhibitor (PPI)
Pharmacological class: Gastric H⁺/K⁺-ATPase inhibitor.
এই patient-এ উদ্দেশ্য: সবচেয়ে সম্ভবত Indomethacin-এর gastric adverse effect/NSAID-related ulcer risk কমানোর gastroprotection। GERD, peptic ulcer, NSAID-associated gastric ulcer prevention ইত্যাদিতেও ব্যবহৃত হয়। Unit ৳11, strip ৳110; 40 mg MUPS-ও পাওয়া যায়।
Exium MUPS 20 mg — MedEx
4. Tab. Contilex TS — 1+0+1, 3 months
Generic: Glucosamine sulfate 750 mg + Chondroitin 600 mg
Company: Square Pharmaceuticals
MedEx Therapeutic Class: Stimulation of Cartilage formation
Pharmacological class: Chondroprotective / osteoarthritis dietary supplement.
এই patient-এ উদ্দেশ্য: doctor-এর OA Knee diagnosis-এর জন্য cartilage/joint symptom support হিসেবে দিয়েছেন—ACL tear heal করার জন্য নয়।
MedEx-এ OA knee/hip/spine ইত্যাদিতে supplement হিসেবে listed। Unit ৳20, 20-tablet pack ৳400; lower strength 250+200 mg-ও আছে।
Contilex TS — MedEx
Alternatives: Arth-A TS, Cartilex Plus, Joinix TS, Jointec Pro ইত্যাদি।
Clinical caveat: MedEx এটিকে OA supplement হিসেবে list করলেও NICE NG226 osteoarthritis guideline routine glucosamine না দিতে বলে, কারণ strong evidence of benefit নেই। তাই এই medicine-এর evidence NSAID/exercise-এর তুলনায় দুর্বল।
5. Tab. Escilex 5 mg — 1+0+0, 3 months
Generic: Escitalopram Oxalate 5 mg
Company: Renata
MedEx Therapeutic Class: SSRIs & related anti-depressant drugs
Pharmacological class: Selective serotonin reuptake inhibitor.
এটি ACL tear বা OA-এর routine drug নয়। Prescription-এ anxiety/depression diagnosis লেখা নেই, তাই কেন দিয়েছেন তা নিশ্চিতভাবে বলা সম্ভব নয়। Chronic pain-associated anxiety, depression, sleep/mood problem থাকলে rationale থাকতে পারে—এটি আমার inference, documented indication নয়।
Used in major depression, panic disorder, GAD, social anxiety, OCD। Unit ৳7, strip ৳70; 10 mg, 20 mg ও solution formulation আছে।
Escilex 5 mg — MedEx
BD alternatives: Oxapro, Losita, Nexito, Citalam, Nexcital ইত্যাদি।
২ নম্বর Prescription :-
এটি cleaner এবং এখানে history স্পষ্ট।
C/C, O/E, History, Investigation, Dx
| বিষয় | Prescription |
| C/C | কোনো separate chief complaint লেখা নেই |
| O/E | কোনো examination finding লেখা নেই |
| History | Diagnosed Case of ACL Partial Tear |
| Investigation | নতুন কোনো investigation লিখে দেওয়া দেখা যাচ্ছে না |
| Doctor’s Dx | ACL Partial Tear |
| বাংলা Dx | হাঁটুর Anterior Cruciate Ligament-এর আংশিক ছিঁড়ে যাওয়া |
Advice
এই prescription-এ পরিষ্কারভাবে আছে: পিঁড়া/মোড়া/টুল/পাটিতে না বসা; high commode/chair ব্যবহার; নামাজ চেয়ারে পড়া; হাঁটু ভেঙে নিচে না বসা; weight reduction; নিয়ম না মানলে knee pain বাড়তে পারে; এবং ROM knee brace ব্যবহার।
Drugs — ২ নম্বর Prescription
1. Cap. D-Rise 40,000 IU — 8 weeks
Generic: Cholecalciferol / Vitamin D3 40,000 IU
Company: Beximco
MedEx Therapeutic Class: Vitamin in bone formation; Vitamin-D preparations
Pharmacological class: Fat-soluble vitamin / vitamin D receptor agonist precursor.
Purpose: suspected/confirmed vitamin-D deficiency এবং bone health support। ACL tear repair করার specific medicine নয়।
MedEx-এর deficiency regimen-এ 40,000 IU once weekly কয়েক সপ্তাহ ব্যবহারের কথা আছে। Unit ৳35, 10-capsule strip ৳350।
D-Rise 40,000 IU — MedEx
Safety point: prescription-এর handwritten অংশটি “প্রতি শুক্রবার সকালে” বলে মনে হচ্ছে—অর্থাৎ once weekly। 40,000 IU daily × 8 weeks হিসেবে নেওয়া উচিত নয়, unless prescribing doctor explicitly confirms; এতে vitamin-D toxicity/hypercalcaemia হতে পারে।
Other D-Rise strengths include 20,000 IU, 50,000 IU, 2,000 IU ইত্যাদি।
2. Tab. Escilex 5 mg — 1+0+0, 3 months
Generic এবং class উপরের মতো: Escitalopram, SSRI। ACL-specific drug নয়। যদি associated anxiety/depression/chronic pain-related mood problem থাকে, সেক্ষেত্রে ব্যবহার rationale থাকতে পারে; prescription থেকে psychiatric indication confirm করা যায় না।
3. Cap. Prelica 25 mg — 0+0+1
Generic: Pregabalin 25 mg
Company: Radiant Pharmaceuticals
MedEx Therapeutic Class: Adjunct anti-epileptic drugs; Primary anti-epileptic drugs
Pharmacological class: Gabapentinoid; α₂δ subunit ligand of voltage-gated calcium channels.
Possible purpose in this patient: neuropathic-type pain—যেমন burning, tingling, electric-shock pain, numbness বা radiating pain থাকলে। Simple isolated ACL ligament pain-এর routine drug নয়।
Used in diabetic neuropathic pain, post-herpetic neuralgia, fibromyalgia, spinal cord–associated neuropathic pain এবং partial-onset seizures। Unit ৳11, strip ৳110।
Prelica 25 mg — MedEx
Other Prelica strengths: 50, 75, 150 mg; CR 82.5/165 mg। BD alternatives include Prelin, Pregaba, Xil, Lirica ইত্যাদি।
Prescription photo-তে duration-এর সংখ্যা পুরো clear নয়, তাই আমি guess করছি না।
৩ নম্বর Prescription
৩ নম্বরটি ১ নম্বর prescription-এর একই page-এর আরেকটি photograph।
তাই:
History/Dx: ACL Partial Tear + OA Knee
C/C: separate label নেই
O/E: documented finding পরিষ্কার নয়
Advice: ১ নম্বরের একই
Investigation: একই handwritten X-ray instruction
Drugs: একই—
- Indomet 25 mg
- Relentus 2 mg
- Exium MUPS 20 mg
- Contilex TS
- Escilex 5 mg
Dose/durationও ১ নম্বরের মতোই। নতুন বা আলাদা third prescription নয়।
এখন সবচেয়ে গুরুত্বপূর্ণ: Doctor-এর Dx বনাম আমার Dx
Doctor’s diagnosis
Rx-2:
Diagnosed case of ACL Partial Tear
Rx-1/3:
ACL Partial Tear + OA Knee
আমার report-based working diagnosis
আপনার আগে দেওয়া MRI Right Knee অনুযায়ী সবচেয়ে নিশ্চিত diagnosis:
Right knee partial ACL tear with lateral femoral condyle bony contusion/marrow edema and mild knee joint effusion.
বাংলায়:
ডান হাঁটুর ACL-এর আংশিক ছিঁড়ে যাওয়া, সাথে lateral femoral condyle-এ আঘাতজনিত bone bruise/marrow edema এবং হাঁটুর joint-এ সামান্য fluid/effusion।
Confidence: 0.99 — কারণ MRI impression-এ সরাসরি এই findings লেখা।
Similarity কতটুকু?
ACL Partial Tear বিষয়ে Doctor এবং আমার diagnosis সম্পূর্ণভাবে concordant। Confidence: 0.99।
অর্থাৎ প্রধান diagnosis নিয়ে কোনো meaningful disagreement নেই।
Difference কোথায়?
“OA Knee” diagnosis নিয়ে আমার confidence কম — ≈0.55।
কারণ আপনার দেওয়া knee MRI report-এ osteoarthritis/cartilage loss/joint-space narrowing/osteophyte উল্লেখ নেই। আবার ১/৩ prescription-এ doctor OA Knee লিখেছেন এবং standing knee X-ray করার মতো handwritten investigationও দেখা যাচ্ছে। তাই OA clinically suspected হতে পারে, অথবা পরের কোনো X-ray-এর ভিত্তিতে doctor লিখে থাকতে পারেন।
Standing weight-bearing knee X-ray যদি joint-space narrowing/osteophytes দেখায়, তাহলে OA Knee diagnosis supported হবে।
আর আপনার আলাদা lumbar X-ray-তে early degenerative lumbar spine changes documented—এটি knee OA-এর প্রমাণ নয়।
এই রোগে Bangladesh-এ সাধারণত কোন drug/class ব্যবহার হতে পারে?
ACL tear-এর definitive pharmacological drug নেই। Drug মূলত pain control; ligament healing/functional recovery নির্ভর করে rehabilitation এবং instability management-এর উপর।
বাংলাদেশে clinically commonly used symptomatic groups হলো NSAID—যেমন ibuprofen, naproxen, diclofenac, aceclofenac, celecoxib/etoricoxib বা indomethacin; প্রয়োজন হলে gastroprotection হিসেবে PPI; associated muscle spasm হলে short-course muscle relaxant; neuropathic features থাকলে pregabalin/gabapentin; documented vitamin-D deficiency থাকলে cholecalciferol। তবে escitalopram, pregabalin, vitamin D, glucosamine—কোনোটিই routine uncomplicated ACL tear-এর ligament-healing drug নয়।
OA থাকলে treatment-এর core হলো exercise/strengthening, weight management এবং প্রয়োজনমতো NSAID; NICE specifically knee OA-তে topical NSAID first এবং প্রয়োজন হলে oral NSAID + gastroprotection recommend করে, আর glucosamine routine use recommend করে না।
Overview / Summary
Doctor-এর মূল Dx ঠিক এবং MRI-এর সাথে match করছে: Partial ACL Tear। ১/৩ নম্বরে অতিরিক্ত OA Knee লেখা আছে—এটি সম্ভাব্য diagnosis, কিন্তু আপনার বর্তমানে শেয়ার করা knee imaging দিয়ে আমি নিশ্চিত করছি না। Rx-এর Indomet pain/inflammation-এর জন্য, Relentus muscle spasm-এর জন্য, Exium NSAID gastric protection-এর জন্য, Contilex OA supplement হিসেবে, D-Rise vitamin-D replacement হিসেবে, Prelica neuropathic pain থাকলে, আর Escilex anxiety/depression-related indication থাকলে ব্যবহৃত হতে পারে।
Actionable Clinical Plan
বর্তমানে patient-এর Lachman test, pivot-shift/anterior drawer, ROM, effusion, quadriceps strength এবং giving-way history document করা সবচেয়ে গুরুত্বপূর্ণ। যদি recurrent instability/giving-way থাকে → Orthopaedic Knee/Sports Surgeon evaluation; stable হলে structured ACL rehabilitation/physiotherapy। OA সন্দেহ থাকলে standing weight-bearing bilateral knee X-ray দেখে diagnosis corroborate করা যাবে। High-dose D-Rise-এর ক্ষেত্রে once-weekly instruction confirm করা উচিত।
References
Textbook: Apley & Solomon’s System of Orthopaedics and Trauma, 10th ed.—Knee ligament injuries/Osteoarthritis chapters.
Guideline: American Academy of Orthopaedic Surgeons. Management of Anterior Cruciate Ligament Injuries, Clinical Practice Guideline, 2022.
Guideline: NICE NG226. Osteoarthritis in over 16s: diagnosis and management, 2022.
Journal/DOI: Brophy RH, Lowry KJ. J Am Acad Orthop Surg. 2023;31:531–537. DOI: 10.5435/JAAOS-D-22-01020.
Md.Rafiqul Islam Lipu