This information has been collected by Dr.Anis
Image attached:-
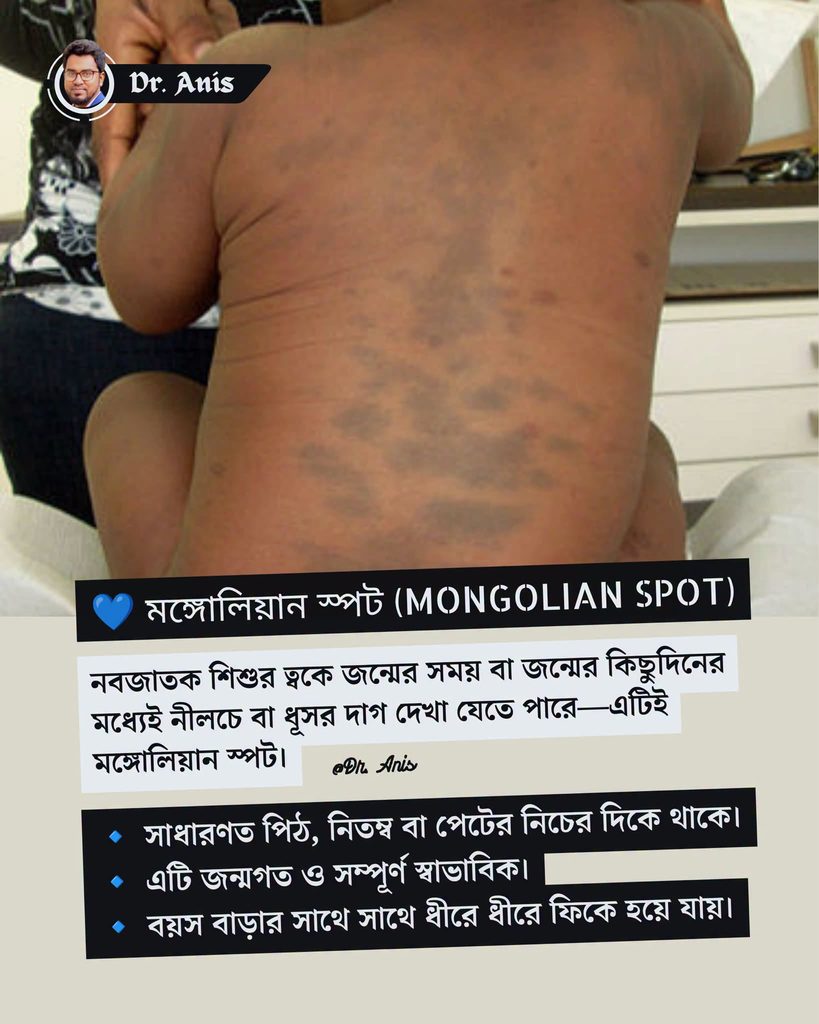
শিশুর পিঠে নীলচে-কালো দাগ দেখে ভয় পাচ্ছেন?
এটি অনেক সময় মঙ্গোলিয়ান স্পট (Mongolian Spot) হতে পারে।
জেনে রাখুন—
• সাধারণত পিঠ, নিতম্ব বা কোমরের নিচে দেখা যায়
• এটি জন্মগত ও সম্পূর্ণ স্বাভাবিক ত্বকের বৈশিষ্ট্য
• কোনো আঘাত বা রোগের কারণে হয় না
• শিশুর বয়স বাড়ার সঙ্গে সঙ্গে ধীরে ধীরে ফিকে হয়ে যায়
• সাধারণত কোনো চিকিৎসার প্রয়োজন হয় না
তাই এমন দাগ দেখলে অযথা ভয় বা দুশ্চিন্তা করবেন না।
This information has been Collected by Chat Gpt:-
Congenital Dermal Melanocytosis (Mongolian Spot) — Clinical Review
Working clinical diagnosis: Congenital Dermal Melanocytosis (CDM), formerly called Mongolian spot. এটি একটি benign congenital dermal pigmentation, রোগ/আঘাত/রক্তক্ষরণ নয়। Typical lesion হলে diagnosis মূলত clinical এবং treatment প্রয়োজন হয় না। Confidence: 0.97.
১. Definition / সংজ্ঞা
Congenital Dermal Melanocytosis হলো জন্মের সময় বা জন্মের অল্প সময়ের মধ্যে দেখা দেওয়া সমতল নীলচে-ধূসর, slate-blue বা blue-black macule/patch, যা সবচেয়ে বেশি sacral, lower back ও buttock অঞ্চলে থাকে। ত্বকের texture স্বাভাবিক থাকে—সাধারণত কোনো swelling, ulceration বা inflammation থাকে না।
পুরোনো নাম Mongolian spot হলেও বর্তমানে Congenital Dermal Melanocytosis নামটি বেশি উপযুক্ত। Confidence: 0.99.
২. Cause / Etiology ও Pathophysiology
- Embryonic melanocyte migration-এর পরিবর্তন: ভ্রূণের বিকাশের সময় neural crest-derived melanocyte ত্বকের উপরের দিকে migration করার প্রক্রিয়ায় কিছু melanocyte dermis-এর গভীরে থেকে যায়। এটিই মূল pathogenesis।
- Melanin dermis-এর গভীরে থাকার কারণে বাইরে থেকে lesion নীলচে বা ধূসর দেখায়।
- এটি আঘাত, infection, allergy, vitamin deficiency বা parental care-এর ভুলের কারণে হয় না।
- সাধারণত কোনো নির্দিষ্ট preventable environmental cause পাওয়া যায় না।
- Asian, African এবং অন্যান্য darker skin phototype-এর শিশুদের মধ্যে তুলনামূলক বেশি দেখা যায়।
Confidence: 0.95.
৩. Clinical Features / Symptoms
এটি আসলে অধিকাংশ ক্ষেত্রে asymptomatic birthmark, অর্থাৎ শিশুর কোনো শারীরিক অসুবিধা থাকে না।
- রং: নীল, slate-grey, bluish-black, blue-green বা greyish-blue হতে পারে।
- স্থান: সবচেয়ে বেশি—
- কোমরের নিচে
- sacral region
- buttock
- lower back
কখনও shoulder, arm, leg বা অন্য জায়গায়ও হতে পারে।
- Shape: গোল, oval অথবা irregular patch হতে পারে।
- Surface: সম্পূর্ণ flat; সাধারণত skin texture স্বাভাবিক।
- ব্যথা: থাকে না।
- চুলকানি: থাকে না।
- Swelling: থাকে না।
- Bleeding/ulcer: থাকে না।
- Birth থেকেই থাকে: সাধারণত জন্মের সময় বা জন্মের shortly পরে দেখা যায়।
- বয়স বাড়ার সঙ্গে অধিকাংশ lesion ধীরে ধীরে হালকা হয়ে যায়; সাধারণত early childhood-এর মধ্যে যথেষ্ট fade করে।
- Persistence বেশি হওয়ার সম্ভাবনা যদি lesion:
- extrasacral হয়
- খুব বড় হয়
- খুব dark হয়।
Confidence: 0.95–0.98.
৪. Clinical Diagnosis
Typical case-এ diagnosis কীভাবে করবেন
Diagnosis মূলত history + inspection/physical examination-এর মাধ্যমে।
Clinical features supporting CDM:
- জন্ম থেকে উপস্থিত।
- Flat blue-grey patch।
- Sacral/buttock/lower-back distribution।
- tenderness নেই।
- swelling নেই।
- শিশুর অন্য কোনো systemic symptom নেই।
- lesion bruise-এর মতো কয়েক দিনে colour evolution করে না।
- সময়ের সঙ্গে ধীরে ধীরে fade করে।
Routine laboratory test প্রয়োজন নেই।
গুরুত্বপূর্ণ clinical documentation
শিশুর newborn record-এ lesion-এর location, approximate size, colour ও number document করা উপকারী, কারণ পরবর্তীতে এটিকে traumatic bruise হিসেবে ভুল বোঝার ঝুঁকি থাকে।
৫. Investigation
Typical Mongolian spot
সাধারণত প্রয়োজন নেই:
- CBC — না
- Platelet count — না
- PT/INR/APTT — না
- X-ray — না
- Ultrasound — না
- CT/MRI — না
- Skin biopsy — না
- Genetic test — না
Typical lesion-এ clinical examination-ই যথেষ্ট।
কখন further investigation বিবেচনা করবেন
যদি lesion খুব extensive, progressive, unusual distribution বা persistent হয় এবং পাশাপাশি systemic abnormality থাকে, তখন underlying metabolic disorder বিবেচনা করা যায়। Extensive dermal melanocytosis-এর সঙ্গে কিছু case-এ GM1 gangliosidosis, mucopolysaccharidosis type I/II এবং অন্যান্য lysosomal storage disorder reported হয়েছে; এটি association, typical spot থাকলেই এসব রোগ আছে এমন নয়।
উদাহরণস্বরূপ যদি পাশাপাশি থাকে:
- developmental delay/regression
- hepatosplenomegaly
- coarse facial features
- skeletal abnormality
- neurological abnormality
- hearing/vision problem
তখন pediatric/metabolic evaluation যুক্তিযুক্ত। Confidence: 0.82, কারণ এই association rare এবং population-wide screening recommendation নয়।
৬. Differential Diagnosis
১. Traumatic bruise / Ecchymosis
সবচেয়ে গুরুত্বপূর্ণ differential।
Bruise-এর ক্ষেত্রে tenderness, swelling, trauma history এবং সময়ের সঙ্গে colour change থাকতে পারে; congenital dermal melanocytosis সাধারণত জন্ম থেকে স্থিতিশীল blue-grey patch।
বিশেষ করে non-mobile infant-এর unexplained bruise হলে child maltreatment-এর বিষয়টি যথাযথভাবে evaluate করতে হয়; কিন্তু congenital dermal melanocytosis-কে bruise হিসেবে ভুল diagnosis করাও এড়াতে হবে।
২. Nevus of Ota
চোখ/মুখের trigeminal distribution-এ blue-grey pigmentation; congenital sacral dermal melanocytosis থেকে আলাদা।
৩. Nevus of Ito
Shoulder, supraclavicular/scapular area-তে dermal melanocytosis।
৪. Blue nevus
সাধারণত ছোট ও more localized melanocytic lesion।
৫. Café-au-lait macule
Brown/tan; blue-grey নয়।
৬. Vascular birthmark
Colour এবং blanching/vascular characteristics আলাদা হতে পারে।
৭. Complications
Typical Mongolian spot-এর medical complication প্রায় নেই
- Pain/infection হয় না।
- শিশুর growth বা development বাধাগ্রস্ত করে না।
- Typical congenital dermal melanocytosis-এর জন্য malignant transformation expected complication নয়।
- সবচেয়ে গুরুত্বপূর্ণ practical complication হলো bruise বা child abuse-এর sign হিসেবে ভুল ব্যাখ্যা করা।
- কিছু বড় বা extrasacral lesion দীর্ঘদিন থাকতে পারে এবং পরে cosmetic concern তৈরি করতে পারে।
- Rare ক্ষেত্রে extensive atypical lesion metabolic disorder-এর সঙ্গে associated হতে পারে; typical isolated lesion-এর ক্ষেত্রে এই association ধরে নেওয়া উচিত নয়।
Overall complication confidence: 0.94.
৮. Treatment & Management
প্রথম এবং প্রধান চিকিৎসা: Reassurance + Observation
WHO newborn guidance-ও congenital dermal melanocytosis-এর ক্ষেত্রে reassurance দিতে বলে, কারণ অধিকাংশ lesion early childhood-এ fade করে।
Management
- Parent counseling।
- Birth/newborn record-এ lesion document করা।
- Routine follow-up।
- কোনো rubbing, bleaching agent, steroid বা antifungal লাগানোর প্রয়োজন নেই।
- Typical lesion-এর জন্য dermatologist referral বাধ্যতামূলক নয়।
- Atypical/extensive/persistent lesion হলে pediatric dermatologist review বিবেচনা করা যায়।
৯. Pharmacological Drug Management — সবচেয়ে গুরুত্বপূর্ণ অংশ
Congenital Dermal Melanocytosis-এর জন্য কোনো pharmacological drug indicated নয়।
অতএব evidence-based prescription-এ:
১. Generic name
কোনো specific medicine নেই।
MedEx Therapeutic Class: Not applicable.
Pharmacological class: Not applicable.
Purpose: কোনো drug therapy প্রয়োজন হয় না।
Dose: Not applicable.
Duration: Not applicable.
Bangladesh available brand name: প্রযোজ্য নয়।
Unit price/strip price: প্রযোজ্য নয়।
Drug interaction: প্রযোজ্য নয়।
Side effects: প্রযোজ্য নয়।
কারণ standard dermatology/pediatric references অনুযায়ী normal congenital dermal melanocytosis-এ medication প্রয়োজন হয় না।
Bangladesh-এর prescription context
Typical Mongolian spot/CDM-এর জন্য evidence-based চিকিৎসায় antibiotic, antifungal, antihistamine, steroid, vitamin, calcium, depigmenting cream বা অন্য tablet/syrup-এর indication নেই।
সুতরাং শুধু MedEx-এ available brand দেখানোর জন্য কোনো brand name, strength বা price prescription করা medically incorrect হবে।
Confidence: 0.99.
১০. Laser therapy কি করা যায়?
Typical শিশুর lesion-এর জন্য প্রয়োজন নেই।
খুব persistent বা cosmetically significant dermal melanocytosis-এ selected older patients-এর জন্য dermatologist Q-switched pigment laser বিবেচনা করতে পারেন। Persistent Mongolian spots-এ Q-switched alexandrite laser ব্যবহারের published evidence রয়েছে।
কিন্তু এটি:
- routine neonatal treatment নয়;
- pharmacological drug নয়;
- cosmetic indication-ভিত্তিক;
- post-inflammatory hyperpigmentation, hypopigmentation বা অন্যান্য pigment change হতে পারে;
- specialist assessment ছাড়া করা উচিত নয়।
১১. Prevention
এটি congenital developmental pigmentation হওয়ায় এটি prevent করার কোনো proven method নেই।
অর্থাৎ pregnancy-তে:
- কোনো নির্দিষ্ট খাবার খাওয়া/না খাওয়া,
- vitamin,
- cream,
- massage,
- sunlight avoidance
এর মাধ্যমে এটি prevent করা যায়—এমন evidence নেই।
বাস্তব preventive action হলো
Misdiagnosis prevention: জন্মের সময় lesion document করা এবং parents-কে জানান যে এটি birthmark।
কখন আবার ডাক্তার দেখাবেন?
Dermatologist/Pediatrician review করা উচিত যদি:
- দাগ জন্মের পরে দ্রুত নতুন করে বাড়তে থাকে;
- lesion painful/swollen হয়;
- bleeding/ulceration হয়;
- explanation ছাড়া নতুন bruises দেখা যায়;
- lesion খুব extensive বা unusual location-এ থাকে;
- developmental delay/regression থাকে;
- hepatosplenomegaly বা অন্যান্য systemic feature থাকে;
- চোখ বা চোখের চারপাশে pigmentation থাকে।
Overview / Summary
Congenital Dermal Melanocytosis একটি benign birthmark। এটি dermis-এ melanocyte থেকে যাওয়ার কারণে হয় এবং সাধারণত lower back, sacrum ও buttock-এ blue-grey patch হিসেবে দেখা যায়। Most cases-এ কোনো investigation বা medicine প্রয়োজন নেই এবং সময়ের সঙ্গে fade করে।
Final working assessment:
Typical Congenital Dermal Melanocytosis — benign, observation only.
Confidence: 0.97, যদি lesion জন্ম থেকে থাকে, flat blue-grey হয় এবং typical sacral/buttock distribution থাকে। কোনো নির্দিষ্ট শিশুকে examination/photo ছাড়া definitive diagnosis করা যাবে না।
Actionable Plan / Steps
- Lesion-এর location, colour, size ও number document করুন।
- Typical হলে parents-কে reassurance দিন।
- কোনো medicine/cream routinely দেবেন না।
- Routine child follow-up যথেষ্ট।
- New unexplained bruising বা atypical/extensive lesion-কে automatically Mongolian spot ধরে নেবেন না—clinical reassessment করুন।
- Extensive lesion + systemic/developmental abnormality থাকলে pediatric/dermatology/metabolic evaluation বিবেচনা করুন।
References
Textbooks
- James WD, Elston DM, Treat JR, Rosenbach M. Andrews’ Diseases of the Skin: Clinical Dermatology. 14th ed. Elsevier; Chapter 25: Melanocytic Nevi and Neoplasms.
- Kliegman RM, St Geme JW, et al. Nelson Textbook of Pediatrics. 22nd ed. Elsevier; Chapter 692: Cutaneous Nevi.
- American Academy of Pediatrics. Pediatric Dermatology: A Quick Reference Guide. 5th ed., 2025; Chapter 74: Congenital Dermal Melanocytosis. DOI: 10.1542/9781610027793-74.
Guideline / authoritative guidance
- WHO. Newborn skin guidance: congenital dermal melanocytosis—reassurance; most lesions fade in early childhood.
- NICE CG89. Child maltreatment: when to suspect maltreatment in under 18s; updated December 2025—relevant when distinguishing unexplained bruising from benign birthmarks.
Peer-reviewed DOI references
- Kettner M, et al. Mongolian spots in forensic examinations. Int J Legal Med. 2020;134:1141-1148. DOI: 10.1007/s00414-019-02208-9.
- Rzepczyk S, et al. Mongolian spots and suspected child abuse. 2024;74(3):221-227. DOI: 10.4467/16891716AMSIK.24.017.20815.
- Kagami S, et al. Treatment of persistent Mongolian spots with Q-switched alexandrite laser. Lasers Med Sci. 2012;27:1229-1232. DOI: 10.1007/s10103-012-1113-4.
- Jacobs AH, Walton RG. The incidence of birthmarks in the neonate. Pediatrics. 1976;58:218-222. DOI: 10.1542/peds.58.2.218.
Md.Rafiqul Islam Lipu,Date:-23-09-2026 Wednesday,Time:-2-38-47 Pm