3Report Attached:-

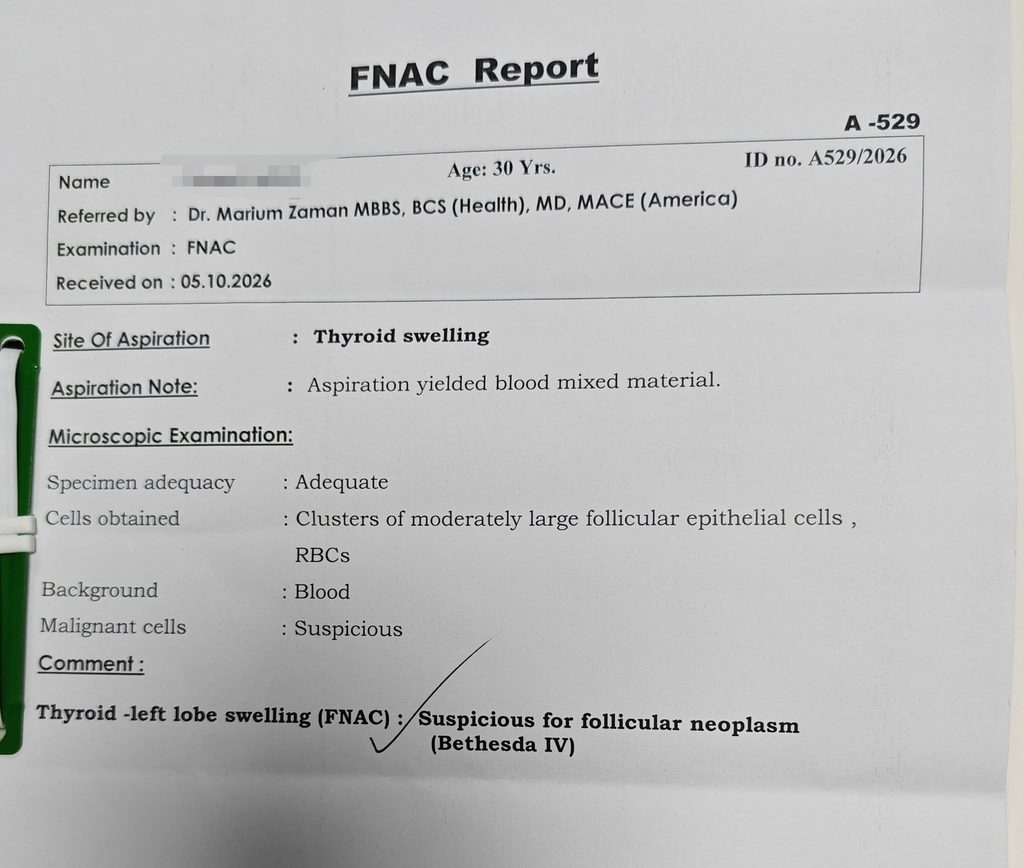
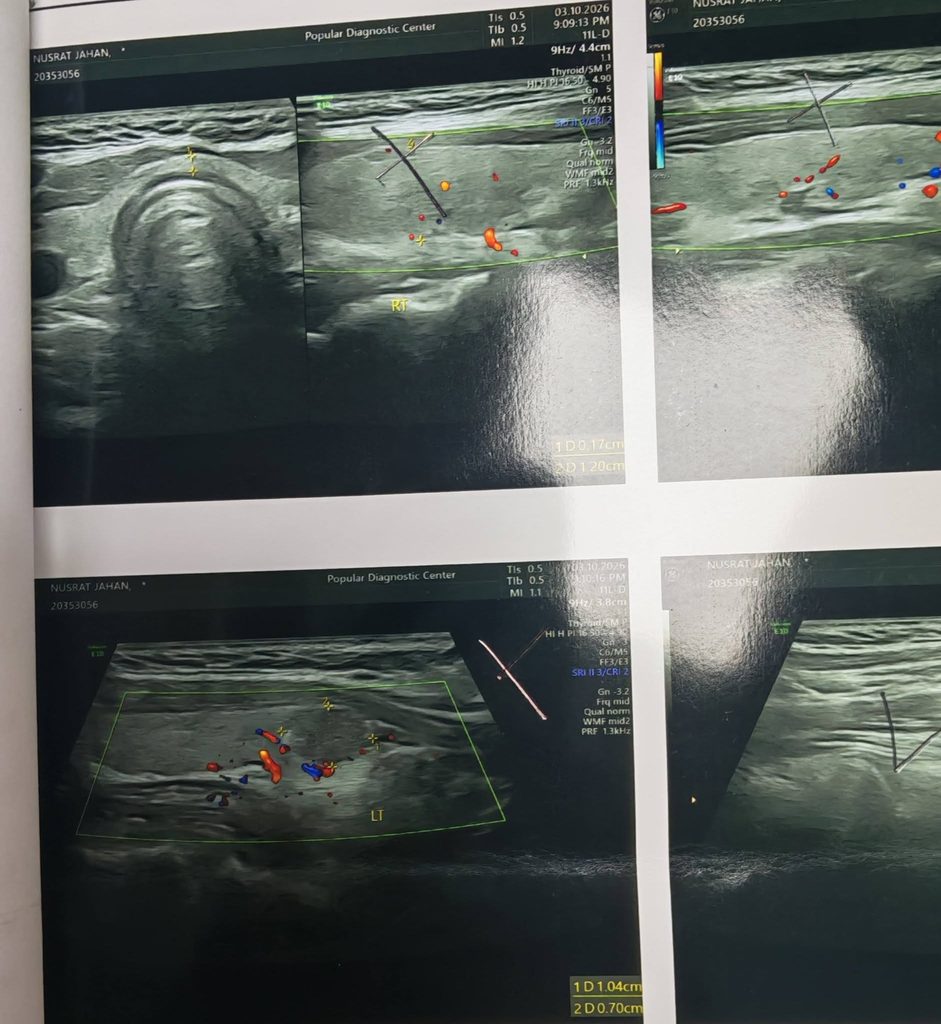
রিপোর্ট ৩টি একসাথে মিলিয়ে দেখলে একটি clinically important abnormality আছে: বাম thyroid lobe-এ 10 × 7 mm hypoechoic solid nodule, যার FNAC Bethesda IV — Follicular neoplasm / suspicious for follicular neoplasm। সবচেয়ে গুরুত্বপূর্ণ বিষয় হলো—এটাকে এখনই follicular thyroid carcinoma বলা যাবে না। FNAC দিয়ে follicular adenoma ও follicular carcinoma আলাদা করা যায় না; carcinoma নিশ্চিত করতে excised tissue-তে capsular and/or vascular invasion দেখতে হয়। 2023 Bethesda অনুযায়ী adult Bethesda IV lesion-এর average malignancy risk প্রায় 30% (range 23–34%)।
1. রিপোর্টে ঠিক কোথায় abnormal
| Report finding | বাংলা clinical meaning | Assessment |
| Right thyroid lobe: normal, AP 12 mm, uniform texture | ডান thyroid স্বাভাবিক আকার ও texture | ✅ Normal |
| No right-sided nodule | ডান পাশে কোনো nodule নেই | ✅ Normal |
| Left lobe: normal size, AP 11 mm | বাম lobe-এর overall size স্বাভাবিক | ✅ Normal |
| Hypoechoic solid nodule 10 × 7 mm | বাম lobe-এ প্রায় 1 cm solid nodule, surrounding thyroid-এর তুলনায় ultrasound-এ darker | 🔴 Abnormal |
| Isthmus AP 1.7 mm, uniform | isthmus স্বাভাবিক | ✅ Normal |
| Submandibular glands normal | দুই submandibular gland স্বাভাবিক | ✅ Normal |
| No abnormally enlarged cervical lymph node | গলায় suspicious/enlarged lymph node দেখা যায়নি | ✅ Reassuring |
| Neck vessels normal | neck vessels স্বাভাবিক | ✅ Normal |
| Muscles uniform, no mass | muscle বা surrounding tissue-তে mass নেই | ✅ Normal |
অর্থাৎ USG-এর মূল finding:
Left thyroid lobe: 10 × 7 mm hypoechoic solid nodule.
তবে এই ultrasound report-এ margin, taller-than-wide shape, punctate echogenic foci/microcalcification, extrathyroidal extension এবং formal TI-RADS score উল্লেখ নেই। তাই ছবিগুলো দেখে নির্ভরযোগ্যভাবে ACR-TIRADS category assign করা উচিত হবে না। Dedicated thyroid US + cervical node mapping করলে risk stratification আরও ভালো হবে।
2. FNAC report-এর clinical interpretation
FNAC-তে specimen adequate, অর্থাৎ diagnosis দেওয়ার মতো যথেষ্ট sample পাওয়া গেছে।
“Clusters of moderately large follicular epithelial cells”
→ মাঝারি-বড় thyroid follicular epithelial cell-এর cluster পাওয়া গেছে।
“RBCs / background blood”
→ aspirate-এ blood ছিল; এটা thyroid FNA-তে হতে পারে এবং specimen adequate হওয়ায় এটাকে nondiagnostic বলা হচ্ছে না।
সবচেয়ে গুরুত্বপূর্ণ line:
🔴 “Suspicious for follicular neoplasm — Bethesda IV”
2023 Bethesda terminology অনুযায়ী এর বর্তমান নাম “Follicular neoplasm (Bethesda IV)”। এটি একটি indeterminate cytology category—benignও হতে পারে, malignantও হতে পারে। Average malignancy risk প্রায় 30%।
রিপোর্টে “Malignant cells: suspicious” লেখা থাকলেও final Bethesda category IV, category V “Suspicious for malignancy” নয়। তাই “thyroid cancer confirmed” লেখা clinically incorrect হবে।
কেন FNAC দিয়ে cancer confirm হচ্ছে না?
Follicular thyroid carcinoma নির্ণয়ের জন্য দেখতে হয়:
Capsular invasion ± vascular invasion
কিন্তু FNA শুধু loose cells সংগ্রহ করে; পুরো nodule-এর capsule দেখা যায় না। এই কারণে একই cytology follicular adenoma, follicular carcinoma, অথবা অন্য follicular-pattern neoplasm-এর ক্ষেত্রেও পাওয়া যেতে পারে। Definitive diagnosis সাধারণত surgical histopathology-তে হয়। ATA-ও Bethesda IV-তে diagnostic surgical excision-কে established standard option হিসেবে উল্লেখ করে।
3. আমার Working Diagnosis
সবচেয়ে সঠিক diagnosis
Left thyroid follicular neoplasm — Bethesda IV, 10 × 7 mm.
বাংলায়:
বাম থাইরয়েড লোবে ১০ × ৭ মিমি follicular neoplasm; FNAC Bethesda category IV।
Cancer confirmed নয়।
আমার confidence:
- Left thyroid follicular neoplasm/Bethesda IV: 0.99
- Nodule size ~1 cm: 0.99
- Current US-তে pathological cervical lymphadenopathy নেই: 0.97
- এটি follicular carcinoma: বর্তমানে মাত্র প্রায় 0.30 probability, definitive diagnosis নয়।
- Benign বনাম malignant নির্ধারণের জন্য further risk assessment/histopathology দরকার: >0.95
4. Differential diagnosis
বর্তমানে প্রধান differential হলো:
- Follicular adenoma — benign.
- Follicular thyroid carcinoma, বিশেষ করে minimally invasive type.
- NIFTP / follicular-patterned papillary thyroid neoplasm।
- অন্যান্য follicular-pattern thyroid lesions—কম সম্ভাব্য।
Papillary thyroid carcinoma, medullary carcinoma বা metastatic disease এই FNAC report দিয়ে established হয়নি।
5. Doctor এখন কী করবেন — practical action plan
প্রথম কাজ: patient-কে Endocrine/Thyroid Surgeon বা Head & Neck Surgeon with thyroid surgery experience-এর কাছে refer করা উচিত। এটি emergency admission-এর বিষয় নয়, কিন্তু routine delayও করা উচিত নয়।
এরপর:
- Serum TSH — অবশ্যই দেখা উচিত। TSH abnormal হলে FT4 ± FT3।
- Dedicated high-resolution thyroid US with ACR-TIRADS/EU-TIRADS + complete cervical lymph-node mapping করা ভালো, কারণ বর্তমান US report incomplete risk characterization দিয়েছে।
- যদি TSH suppressed/low হয় → thyroid radionuclide scintigraphy বিবেচনা করতে হবে; functioning nodule-এর pathway আলাদা। ETA guideline-ও subnormal TSH-তে scintigraphy recommend করে।
- Molecular testing (যেমন ThyroSeq/Afirma-type validated test) available ও affordable হলে Bethesda IV-তে decision-making-এ ব্যবহার করা যায়।
- Molecular testing unavailable/inconclusive হলে standard definitive diagnostic option হলো left thyroid lobectomy/hemithyroidectomy, usually with isthmus included as appropriate, এরপর permanent histopathology। ATA ও ETA উভয় guideline-এ Bethesda IV-এর ক্ষেত্রে surgery গুরুত্বপূর্ণ management option।
একটি গুরুত্বপূর্ণ nuance
Nodule মাত্র 10 mm, lymph node suspicious নয়। 2023 ETA guideline Bethesda IV-এ সাধারণত surgery offer করতে বলে, তবে <15 mm, favorable ultrasound features থাকলে selected patient-এ close surveillanceও বিবেচনা করা যায়, বিশেষ করে expert US/molecular assessment reassuring হলে। তাই শুধু “Bethesda IV” দেখে তৎক্ষণাৎ total thyroidectomy করা উচিত নয়।
এই patient-এর বর্তমান data অনুযায়ী total thyroidectomy first step হিসেবে আমি recommend করব না। যদি operation chosen হয়, isolated unilateral 1-cm lesion-এর জন্য diagnostic left lobectomy/hemithyroidectomy বেশি proportionate initial approach—final histopathology অনুযায়ী পরবর্তী সিদ্ধান্ত হবে।
6. Surgery হলে এরপর কী হবে?
Histopathology যদি follicular adenoma/benign হয়: সাধারণত আর cancer surgery দরকার হয় না; post-lobectomy TSH follow-up যথেষ্ট হতে পারে।
Histopathology যদি follicular carcinoma দেখায়: তখন tumor size, capsular invasion, vascular invasion, margins, extrathyroidal extension এবং অন্যান্য pathological risk factor দেখে সিদ্ধান্ত হবে—lobectomy যথেষ্ট নাকি completion thyroidectomy প্রয়োজন। Confirmed DTC management-এর জন্য 2025 ATA guideline এখন risk-adapted ও individualized treatment-এর ওপর জোর দেয়।
7. কোন test অকারণে এখন করাব না
এই stage-এ routineভাবে serum thyroglobulin cancer diagnostic test হিসেবে, CT/MRI, PET-CT বা random tumor-marker panel করার প্রয়োজন নেই। CT/MRI সাধারণত local extension/retrosternal disease-এর specific indication থাকলে করা হয়।
আর repeat FNAC alone follicular adenoma বনাম carcinoma reliably আলাদা করতে পারবে না, কারণ মূল issue capsular/vascular invasion।
8. Prescription-এ Dx কী লিখবেন?
সবচেয়ে clinically accurate wording:
Dx: Left thyroid follicular neoplasm (Bethesda IV), 10 × 7 mm.
আরও completeভাবে:
Dx: Left thyroid nodule (10 × 7 mm), FNAC: Follicular neoplasm – Bethesda category IV; malignancy not yet confirmed.
“Follicular thyroid carcinoma” লিখবেন না, কারণ histopathology এখনও হয়নি।
বাংলা diagnosis
বাম থাইরয়েড লোবে ১০ × ৭ মিমি ফোলিকুলার নিওপ্লাজম (Bethesda IV)—ক্যান্সার এখনো নিশ্চিত নয়।
9. Referral note কী লিখবেন?
Prescription/referral-এ সরাসরি এইভাবে লেখা সবচেয়ে পরিষ্কার:
Refer to Endocrine/Thyroid Surgeon for evaluation of left thyroid follicular neoplasm (10 × 7 mm), FNAC Bethesda IV. No abnormal cervical lymphadenopathy reported on current USG. Kindly assess for definitive management including diagnostic left thyroid lobectomy/hemithyroidectomy versus molecular/risk-stratified surveillance as appropriate.
Short version:
Referred to Endocrine/Thyroid Surgeon — Left thyroid follicular neoplasm, Bethesda IV, for definitive evaluation and management.
Overview / Summary
এই patient-এর thyroid cancer এখনো confirmed নয়। নিশ্চিত finding হলো 1-cm left thyroid follicular neoplasm, Bethesda IV। বর্তমান evidence অনুযায়ী malignancy probability আনুমানিক 30%, অর্থাৎ roughly 7/10 Bethesda-IV nodules ultimately malignant না-ও হতে পারে।
সবচেয়ে reassuring বিষয় হলো right lobe normal, gland size normal এবং report অনুযায়ী abnormal cervical lymph node নেই। কিন্তু Bethesda IV-এর কারণে lesion-টিকে dismiss করা যাবে না।
Actionable Plan / Steps
TSH → dedicated thyroid US/TIRADS + cervical node mapping → endocrine/thyroid surgeon review → molecular testing if feasible → otherwise diagnostic left lobectomy/hemithyroidectomy is the standard definitive pathway. Final histopathology না পাওয়া পর্যন্ত diagnosis-এ carcinoma শব্দটি confirmed diagnosis হিসেবে ব্যবহার করবেন না।
References
Textbooks: Jameson JL, Fauci AS, Kasper DL, et al. Harrison’s Principles of Internal Medicine. 22nd ed. McGraw-Hill, 2025; section Thyroid Nodular Disease and Thyroid Cancer.
Kumar V, Abbas AK, Aster JC, et al. Robbins, Cotran & Kumar Pathologic Basis of Disease. 11th ed. Elsevier, 2026; Chapter 24, The Endocrine System.
Guidelines: Durante C, et al. 2023 European Thyroid Association Clinical Practice Guidelines for thyroid nodule management. Eur Thyroid J. 2023;12:e230067. DOI: 10.1530/ETJ-23-0067.
Haugen BR, et al. 2015 ATA Management Guidelines for Adult Patients with Thyroid Nodules and Differentiated Thyroid Cancer. Thyroid. 2016. DOI: 10.1089/thy.2015.0020.
Ringel MD, Sosa JA, et al. 2025 ATA Management Guidelines for Adult Patients with Differentiated Thyroid Cancer. Thyroid. 2025;35:841–985. DOI: 10.1177/10507256251363120.
Cytopathology: Ali SZ, Baloch ZW, et al. The 2023 Bethesda System for Reporting Thyroid Cytopathology. J Am Soc Cytopathol. 2023;12:319–325. DOI: 10.1016/j.jasc.2023.05.005.
Md.Rafiqul Islam Lipu.