(2Report+3prescription):-
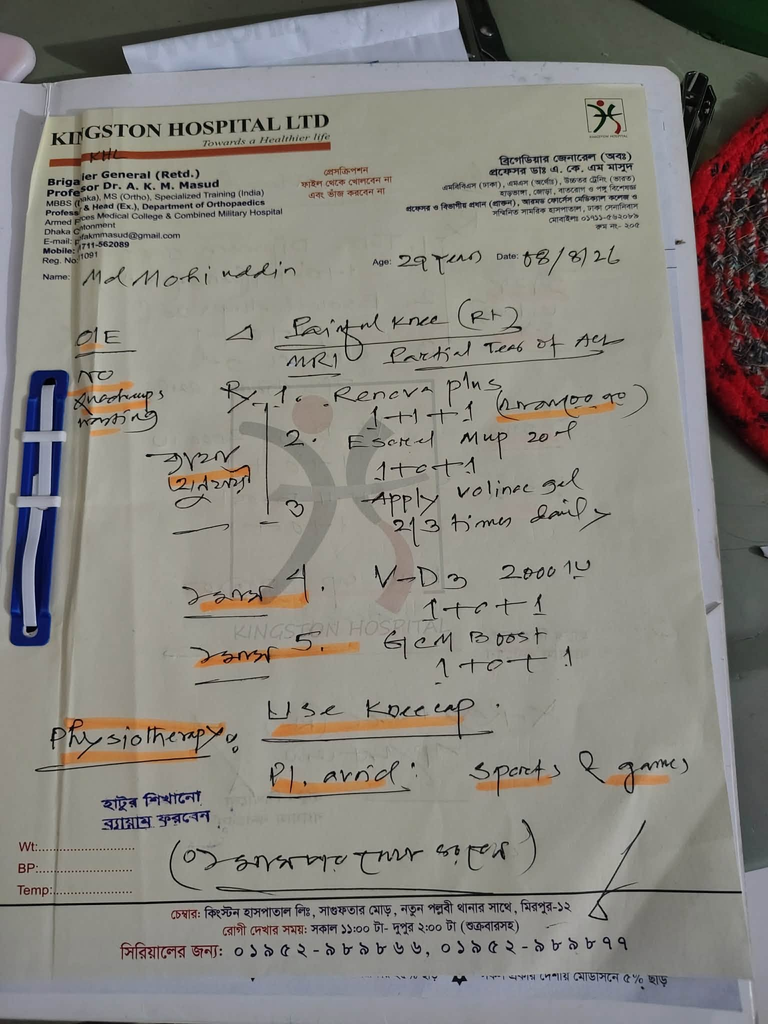

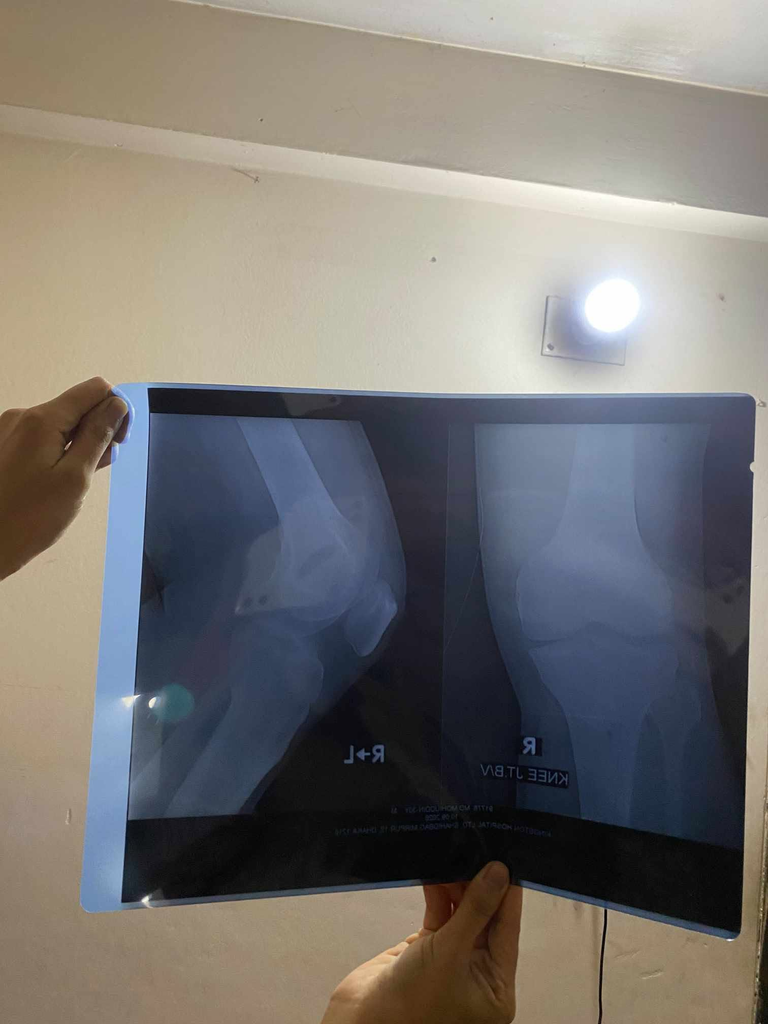


আমি ৫টি ছবিকে আলাদা করে দেখেছি। ৩–৫ নম্বর = investigation/report, আর ১ ও ২ নম্বর = দুই সময়ের আলাদা prescription হিসেবে বিশ্লেষণ করছি। Handwritten অংশে যেটা 100% readable নয়, সেখানে অনুমান করে drug/dose বানিয়ে বলছি না।
1. Report analysis — ৩, ৪ ও ৫ নম্বর
A. MRI Right Knee — সবচেয়ে গুরুত্বপূর্ণ রিপোর্ট
Clinical information: “Sports injury 3 months ago, pain & swelling.”
বাংলা: ৩ মাস আগে খেলাধুলাজনিত আঘাতের পর ডান হাঁটুতে ব্যথা ও ফোলা।
🔴 1. “Signal change is seen in anterior cruciate ligament with partial fiber disruption (70% tear).”
বাংলা: ডান হাঁটুর ACL-এর প্রায় 70% fibre আংশিকভাবে ছিঁড়ে গেছে। এটিকে clinically high-grade partial ACL tear বলা যুক্তিসঙ্গত। তবে MRI-তে “70%” লেখা মানেই functional instability 70% নয়; Lachman/Pivot-shift দিয়ে instability আলাদাভাবে assess করতে হবে।
Confidence: 0.99
🔴 2. “Signal change is seen in medial meniscus.”
বাংলা: হাঁটুর ভিতরের cartilage cushion অর্থাৎ medial meniscus-এ injury/tear-related signal change আছে।
গুরুত্বপূর্ণ: MRI report-এ bucket-handle tear লেখা নেই, tear-এর orientation/displacement-ও উল্লেখ নেই।
Medial meniscus injury confidence: 0.98
Specific bucket-handle tear confidence from report alone: ~0.60
🔴 3. “Moderate joint effusion is seen.”
বাংলা: হাঁটুর joint-এর ভেতরে মাঝারি পরিমাণ fluid জমেছে। Trauma/ACL-meniscus injury-এর কারণে reactive synovitis/effusion হতে পারে।
Confidence: 0.99
🔴 4. “Soft tissue swelling is seen around the knee joint.”
বাংলা: হাঁটুর চারপাশের soft tissue-এ ফোলা আছে।
Confidence: 0.99
🟢 5. “PCL reveal no definite abnormality.”
বাংলা: Posterior cruciate ligament-এ উল্লেখযোগ্য injury পাওয়া যায়নি।
🟢 6. “Joint spaces and fat lines appear normal.”
বাংলা: Joint space preserved; advanced cartilage-loss/advanced OA-এর evidence নেই।
🟢 7. “Lower end of femur and upper end of tibia appear normal.”
বাংলা: Femur ও tibia-এর relevant অংশে acute structural bony abnormality নেই।
🟢 8. “No bony contusion or injury could be detected.”
বাংলা: MRI-তে bone bruise বা acute bony injury পাওয়া যায়নি।
MRI Final Impression
Right knee high-grade partial ACL tear (~70%) + medial meniscal injury + moderate joint effusion + periarticular soft-tissue swelling.
এটাই এই case-এর প্রধান structural pathology।
2. X-ray report analysis
🔴 “Minimal osteophytes are noted in lower femur, upper tibia and posterior patella.”
বাংলা: Femur, tibia ও patella-এর margin-এ খুব ছোট osteophyte/bony spur তৈরি হয়েছে। এটা early degenerative change নির্দেশ করে।
Confidence: 0.97
🔴 “Tibial spines are prominent.”
বাংলা: Tibial spine কিছুটা prominent—degenerative/remodelling change-এর সঙ্গে দেখা যেতে পারে।
🟢 “Joint spaces are normal & maintained.”
বাংলা: Joint space কমে যায়নি। অর্থাৎ advanced osteoarthritis নয়।
🟢 “No fracture or dislocation is seen.”
বাংলা: কোনো fracture বা dislocation নেই।
Radiologist’s comment: “Early degenerative changes.”
বাংলা: প্রাথমিক degenerative/osteoarthritic পরিবর্তন।
এখানে আমি Kellgren-Lawrence Grade নির্দিষ্ট করে দেব না, কারণ proper weight-bearing radiographs এবং standardized views ছাড়া সেটা confidently করা ঠিক হবে না।
৩ নম্বর actual X-ray:- photograph-এ glare/photographic limitation আছে; gross fracture/dislocation দেখা যাচ্ছে না, তবে subtle change-এর জন্য formal radiology report-কে বেশি weight দিতে হবে।
MRI vs X-ray কি contradictory?
না। MRI-তে “joint space/bone normal” বলা acute structural injury-এর context-এ, আর X-ray-তে small osteophytes দেখা গেছে। Minimal osteophyte থাকতে পারে কিন্তু joint space এখনও preserved থাকতে পারে।
3. আমার Final Working Diagnosis:-
Prescription-এ clinically আমি লিখতাম:
Dx:
Right knee high-grade partial ACL tear (~70%) with medial meniscal injury, moderate knee joint effusion and periarticular soft-tissue swelling; associated early degenerative changes.
বাংলা
ডান হাঁটুর ACL-এর উচ্চমাত্রার আংশিক ছিঁড়ে যাওয়া (প্রায় ৭০%), সাথে medial meniscus injury, মাঝারি joint effusion ও হাঁটুর চারপাশে soft-tissue swelling; X-ray-এ প্রাথমিক degenerative change।
Overall confidence: 0.97
আর যদি doctor actual MRI sequences দেখে displaced meniscus নিশ্চিত করেন, তখন লেখা যেতে পারে:
“Medial meniscus bucket-handle tear”
কিন্তু শুধুমাত্র দেওয়া MRI report থেকে bucket-handle tear confirmed বলে লেখা উচিত নয়।
4. Doctor-এর “Bucket handle tear” কথাটা কীভাবে দেখব?
২ নম্বর prescription-এর handwritten diagnosis-এ পরিষ্কারভাবে প্রায় এইরকম লেখা:
“ACL injury (Rt) & Med. meniscus injury (bucket handle tear)”
এটার পক্ষে clinical support আছে কারণ:
- medial joint-line tenderness
- McMurray test positive
- MRI-তে medial meniscus injury
- sports injury history
কিন্তু written MRI report-এ displaced fragment/double-PCL sign/intercondylar fragment বা “bucket-handle” explicitly নেই।
তাই আমার assessment:
Medial meniscus injury = confirmed/high confidence
Bucket-handle morphology = probable/surgeon-suspected, but report-alone confirmation নেই।
যদি patient-এর true locking থাকে—বিশেষ করে knee পুরো extend করতে না পারে—তাহলে displaced bucket-handle tear-এর suspicion অনেক বেড়ে যায় এবং prompt arthroscopic assessment গুরুত্বপূর্ণ।
5. Etiology / Pathophysiology
এটা মূলত sports-related internal derangement of the right knee।
Twisting/pivoting injury → ACL fibres disruption → anterior/rotational instability → meniscus-এর ওপর abnormal load → medial meniscus injury → synovial irritation → effusion/swelling।
বারবার instability/giving-way হলে secondary meniscal এবং cartilage injury-এর ঝুঁকি বাড়তে পারে। AAOS বলছে, যে ACL tear-এ surgery সত্যিই indicated, সেখানে reconstruction অযথা delay না করাই ভালো; additional meniscal/cartilage injury-এর risk প্রায় 3 মাসের পর বাড়তে শুরু করে।
6. এখন Doctor-এর Action Plan কী হওয়া উচিত?
প্রথমে Knee Arthroscopy/Sports Orthopaedic Surgeon দিয়ে পুনরায় clinical assessment দরকার। বিশেষ করে Lachman test, Pivot-shift, anterior drawer, range of motion, extension block, medial joint-line tenderness, McMurray/Thessaly, effusion এবং episodes of “giving way” document করা উচিত।
তারপর surgeon-কে actual MRI images/sequences review করতে হবে—শুধু report নয়—কারণ medial meniscus tear-এর exact type, displacement এবং সত্যিই bucket-handle component আছে কি না, সেটা treatment decision বদলে দেবে।
যদি locked knee/extension block/displaced bucket-handle tear থাকে, তাহলে early arthroscopic evaluation এবং সম্ভব হলে meniscal repair বেশি যুক্তিসঙ্গত। Meniscal tissue যতটা সম্ভব preserve করা orthopaedic principle। তবে AAOS-এর 2024 acute meniscal guideline formally concomitant ACL tear-সহ cases exclude করে, তাই এই patient-এ guideline-টি সরাসরি algorithm হিসেবে ব্যবহার করা যাবে না; principle হিসেবে useful।
যদি knee clinically stable থাকে, true locking না থাকে এবং straight-line daily activities-এ instability না হয়, তাহলে structured rehabilitation reasonable initial option হতে পারে—বিশেষত partial ACL injury-তে। International ACL expert survey-এ stable partial ACL injuries-এর ক্ষেত্রে অধিকাংশ surgeon non-operative management পছন্দ করেছেন।
কিন্তু recurrent giving-way, positive pivot shift/high functional instability, high-demand pivoting sports-এ ফিরে যাওয়ার প্রয়োজন, অথবা surgically repairable displaced meniscal tear থাকলে ACL reconstruction ± meniscal repair বেশি strongly considered হবে। Consensus literature-ও high-demand pivoting athletes বা persistent instability-তে reconstruction সমর্থন করে।
Physiotherapy target
Initial rehabilitation-এ লক্ষ্য হবে effusion কমানো, full extension ও flexion ফিরিয়ে আনা, quadriceps activation/strength, hamstring ও calf flexibility, hip/core strength, proprioception এবং neuromuscular control। Pivoting, cutting, sudden turning, football/cricket-type twisting activity আপাতত avoid করা উচিত।
7. আর কী Investigation করা যায়?
সব test একসাথে প্রয়োজন নেই। Clinical indication অনুযায়ী:
- Focused knee examination: Lachman, Pivot-shift, anterior drawer, McMurray/Thessaly, ROM/extension block, effusion assessment—সবচেয়ে গুরুত্বপূর্ণ।
- Actual MRI sequence review: বিশেষ করে medial meniscus-এর bucket-handle/displaced component আছে কি না। Routine repeat MRI এখনই প্রয়োজন নেই যদি current study technically adequate হয়।
- যদি degenerative component accurately assess করতে হয়: weight-bearing AP + lateral ± Rosenberg/tunnel + patellofemoral skyline view।
- Recurrent/very tense effusion হলে therapeutic/diagnostic aspiration বিবেচনা করা যায়। যদি knee hot/red + fever থাকে তাহলে synovial fluid cell count, crystal, Gram stain/culture এবং CBC/CRP/ESR প্রয়োজন।
- Operation planned হলে appropriate pre-anaesthetic work-up—CBC, renal function/electrolytes, glucose etc. patient-specific risk অনুযায়ী; routine unnecessary tests নয়।
- Vitamin-D supplementation দীর্ঘমেয়াদি চালানোর indication প্রশ্নবিদ্ধ হলে serum 25-OH vitamin D বিবেচনা করা যায়।
8. কাকে Refer করবেন?
Orthopaedic Surgeon — Sports Medicine / Knee Arthroscopy / ACL Reconstruction & Meniscal Repair specialist.
Prescription/Referral note
Referred to Knee Arthroscopy/Sports Orthopaedic Surgeon:
29-year-old male with post-sports-injury right knee pain/swelling. MRI shows high-grade partial ACL tear (~70%), medial meniscal injury, moderate joint effusion and periarticular soft-tissue swelling. Clinical examination previously documented medial joint-line tenderness and positive McMurray test; treating surgeon has suspected a bucket-handle medial meniscal tear. X-ray demonstrates minimal osteophytes/early degenerative change with preserved joint space. Kindly evaluate ACL functional instability, confirm meniscal tear morphology/displacement on MRI images, and advise arthroscopic meniscal repair ± ACL reconstruction versus structured rehabilitation.
***1No Prescription Analysis***:-
9. Prescription–1: Kingston Hospital — আলাদা Analysis
ছবিতে যা readable:
C/C / Diagnosis written
“Painful knee (Rt)”
বাংলা: ডান হাঁটুতে ব্যথা।
“MRI → Partial tear of ACL”
বাংলা: MRI-তে ACL-এর partial tear।
O/E
Handwriting অনুযায়ী সম্ভবত:
“No quadriceps wasting.”
বাংলা: Quadriceps muscle wasting নেই।
Confidence of transcription: ~0.80, কারণ handwriting partly obscured।
Advice
- Physiotherapy
- Use knee cap
- Please avoid sports & games
এগুলো partial ACL injury-এর conservative rehabilitation approach-এর সঙ্গে clinically consistent।
***1No Prescription Analysis***:- Medicine Analysis
Rx-1 Drugs
***1. Renova Plus***
Generic: Paracetamol 500 mg + Caffeine 65 mg
Bangladesh brand: Renova Plus — Opsonin Pharma
MedEx Therapeutic Class: Non-Opioid Analgesics
Pharmacological class: Paracetamol = non-opioid analgesic/antipyretic; caffeine = methylxanthine analgesic adjuvant.
এখানে কেন দিয়েছে: হাঁটুর pain symptomaticভাবে কমানোর জন্য। ACL বা meniscus জোড়া লাগায় না।
Other uses: headache, migraine, toothache, neuralgia, backache, fever-associated pain ইত্যাদি।
MedEx price: Unit ≈ ৳2.51; 10-tablet strip ≈ ৳25.10।
একই 500+65 mg generic-এর Bangladesh alternatives-এর মধ্যে Ace Plus, Fast Plus ইত্যাদি আছে।
***2. Esoral MUPS 20 mg***
Generic: Esomeprazole 20 mg
Brand: Esoral MUPS — Eskayef
MedEx Therapeutic Class: Proton Pump Inhibitor (PPI)
Pharmacological class: H+/K+-ATPase inhibitor.
এখানে উদ্দেশ্য: gastric acid suppression / dyspepsia অথবা analgesic/anti-inflammatory treatment-এর সঙ্গে gastric protection। ACL-এর চিকিৎসা সরাসরি করে না।
Used in: GERD, peptic ulcer, NSAID-associated gastric ulcer prevention/treatment, H. pylori regimen-এর অংশ ইত্যাদি।
Price: Unit ≈ ৳10, 14-tablet strip ≈ ৳140।
Other MUPS brands: Sergel MUPS, REMMO, Siligel MUPS, Somazole MUPS ইত্যাদি।
***3. VOLINAC Gel***
Generic: Diclofenac Sodium + Methyl Salicylate + Linseed Oil + Menthol
Brand: VOLINAC 1% w/w — Square
MedEx Therapeutic Class: NSAIDs
Purpose: Local pain, inflammation ও swelling কমানো।
Used in: joint pain, sprain, strain, tendinitis, bursitis, musculoskeletal pain।
Price: 50 g tube ≈ ৳100।
Prescription-এ লেখা অনুযায়ী 2–3 times daily application মনে হচ্ছে; তবে MedEx product information-এ 3–4 times/day উল্লেখ আছে—actual treating doctor’s instruction-ই follow করতে হবে।
Other same-combination products include VOLINAC Max 2% এবং VOLINI 1%।
***4. “V-D3 2000 IU” — সম্ভবত Vita D3 2000 IU***
Handwriting অনুযায়ী drug-টি V-D3/Vita D3 2000 IU মনে হচ্ছে; exact brand নিশ্চিত করতে strip/box প্রয়োজন।
যদি Vita D3 হয়:
Generic: Cholecalciferol [Vitamin D3] 2000 IU
MedEx Therapeutic Class: Vitamin in bone formation / Vitamin-D preparations
Purpose: Vitamin-D deficiency correction এবং bone health; ACL/meniscus tear repair-এর specific drug নয়।
Price of Vita D3 (Renata): Unit ≈ ৳2.50, strip 10 ≈ ৳25।
2000-IU alternatives include D-Rise, D-Set ইত্যাদি।
5. “GCM Boost” — Did not find any medex shop
OR Tablet :-Bost you can use AS A Vitamin B1,B6,B12 AS A Specific combined vitamin preparations
এটি “GCM Boost” এর মতো দেখাচ্ছে, কিন্তু Bangladesh MedEx-এ এই exact brand আমি reliably verify করতে পারিনি। তাই generic, price বা therapeutic class অনুমান করে লিখছি না।
“GCM” নাম অনেক ক্ষেত্রে glucosamine/chondroitin/MSM supplements বোঝালেও এই prescription-এর product-এর composition না দেখে সেটা ধরে নেওয়া নিরাপদ নয়।
Confidence of drug-name reading: ~0.55।
***2No Prescription Analysis***:- Medicine Analysis
10. Prescription–2: Islami Bank Hospital — আলাদা Analysis
C/C / History written
“Pain in Rt knee”
→ ডান হাঁটুতে ব্যথা।
“H/O sports injury – 2 yrs back.”
→ প্রায় ২ বছর আগে sports injury-এর history লেখা হয়েছে।
“H/O aspiration from Rt knee.”
→ আগে ডান হাঁটু থেকে fluid aspirate করার history আছে।
গুরুত্বপূর্ণ discrepancy
MRI report একই case-এ sports injury 3 months ago লিখেছে, কিন্তু prescription-এ 2 years back লেখা।
এটা clinically reconcile করা দরকার—সম্ভবত পুরনো injury + recent re-injury হতে পারে, অথবা history documentation mismatch।
Confidence that this discrepancy exists: 0.95।
O/E
“Rt knee medial joint line – mild tender.”
বাংলা: ডান হাঁটুর medial joint line-এ হালকা tenderness।
“McMurray test: +ve.”
বাংলা: McMurray positive—medial meniscus pathology-এর clinical support দেয়, যদিও একা এই test definitive নয়।
Doctor’s Dx
“ACL injury (Rt) & medial meniscus injury (bucket handle tear)”
বাংলা:
ডান হাঁটুর ACL injury এবং medial meniscus-এর bucket-handle type tear সন্দেহ/diagnosis।
Plan
“Arthroscopic evaluation & proceed.”
বাংলা: Arthroscopy করে joint-এর ভিতরের injury directly evaluate করে প্রয়োজনমতো operative treatment করা হবে।
এটা especially reasonable যদি knee locking, mechanical catching বা displaced meniscal tear থাকে।
Advice
Prescription-এ readable:
- Physiotherapy
- Quadriceps strengthening
- Hamstring & calf stretching
- Knee cap use
***2No Prescription Analysis***:- Medicine Analysis
11. Prescription–2 Drugs
***1. Napa One 1000Mg***
Generic: Paracetamol 1000 mg
Brand: Napa One — Beximco
MedEx Therapeutic Class: Non-Opioid Analgesics
Pharmacological class: Para-aminophenol analgesic/antipyretic.
এখানে কেন দিয়েছে: traumatic knee pain control।
Used in: mild–moderate pain, sprain, musculoskeletal pain, fever, postoperative pain, osteoarthritic/rheumatic pain ইত্যাদি।
Price: Unit ≈ ৳2.25, 10-tablet strip ≈ ৳22.50।
1000-mg alternatives include Ace Power, Aceta One, Fast One ইত্যাদি।
Rx-এর exact frequency handwriting পুরোপুরি পরিষ্কার নয়, তাই আমি dose বানিয়ে দিচ্ছি না।
***2. Bontiv 750 mg + 50 mg***
Generic: Glucosamine Sulfate 750 mg + Diacerein 50 mg
Brand: Bontiv — Healthcare Pharmaceuticals
MedEx Therapeutic Class: Stimulation of Cartilage formation
Pharmacological class: Glucosamine = chondroprotective/nutraceutical substrate; Diacerein = anthraquinone derivative / IL-1-modulating symptomatic OA agent.
Prescription-এ কেন দেয়া হতে পারে: X-ray-এর early degenerative change/joint symptoms-এর জন্য joint-supporting symptomatic therapy হিসেবে।
MedEx indications-এর মধ্যে osteoarthritis এবং bone/joint injuries রয়েছে।
Price: Unit ≈ ৳12; 4-tablet strip ≈ ৳48; 7×4 pack ≈ ৳336।
Same composition alternatives: Arth-A Max, Bonacerin, Cartibon, Cartilage Max, Cartilex D, Jointec Max, Tilex Max ইত্যাদি।
Evidence caveat
এটি ACL বা meniscus tear mechanically heal করে—এমন evidence নেই। আর osteoarthritis management-এর জন্য NICE glucosamine routinely recommend করে না, কারণ convincing clinical benefit-এর evidence নেই।
***3. Sergel MUPS 20 mg***
Generic: Esomeprazole 20 mg
Brand: Sergel MUPS — Healthcare Pharmaceuticals
MedEx Therapeutic Class: Proton Pump Inhibitor
Pharmacological class: Gastric H+/K+-ATPase inhibitor.
Purpose: Gastric acid suppression/gastroprotection; analgesic/NSAID-related dyspepsia/ulcer risk থাকলে ব্যবহার করা হয়। Knee ligament repair করে না।
Price: Unit ≈ ৳11, 10-tablet strip ≈ ৳110।
Handwriting দেখে breakfast/food-এর আগে নেওয়ার নির্দেশ মনে হচ্ছে, কিন্তু exact wording পরিষ্কার না হওয়ায় dispensing label/prescriber order verify করা উচিত।
12. দুই Prescription একসাথে খাওয়া যাবে?
এটা খুব গুরুত্বপূর্ণ।
দুটো prescription দুই আলাদা date/consultation-এর, তাই automatically combine করা উচিত নয়।
বিশেষ করে:
Renova Plus = Paracetamol 500 mg + Caffeine
Napa One = Paracetamol 1000 mg
অর্থাৎ দুটো একসাথে নিলে duplicate paracetamol হয়ে total daily dose অজান্তে বেড়ে যেতে পারে এবং hepatic toxicity risk বাড়ে। MedEx-ও paracetamol-containing products overlap না করার সতর্কতা দেয়।
13. Bangladesh practice-এ এই ধরনের case-এ কোন drug classes দেখা যায়?
Drug treatment এখানে symptomatic; ACL বা displaced meniscus pharmacologically “heal” করা যায় না।
- Analgesic: Paracetamol—pain control।
- Topical NSAID: Diclofenac gel—localized pain/inflammation।
- Oral NSAID যেমন naproxen/celecoxib/etoricoxib—selected patient-এ short course, কিন্তু renal/GI/CV contraindications দেখে।
- PPI: Esomeprazole—oral NSAID/GI-risk থাকলে gastroprotection।
- Vitamin D: documented deficiency/risk থাকলে।
- Glucosamine/diacerein or other joint supplements: Bangladesh practice-এ পাওয়া যায়, কিন্তু এগুলো ACL/meniscus structural healing-এর core treatment নয়।
Early degenerative knee symptoms-এর জন্য topical NSAID evidence-supported; oral NSAID দরকার হলে lowest effective dose/shortest duration এবং GI/renal/CV risk বিবেচনা করতে NICE বলে।
14. Doctor-এর Dx আর আমার Dx কি Similar?
Doctor-2 Dx
ACL injury (Rt) + medial meniscus injury (bucket-handle tear).
আমার Dx
High-grade partial ACL tear (~70%) + medial meniscal injury + moderate effusion + soft-tissue swelling + early degenerative changes.
Similarity
Core diagnosis প্রায় একই — confidence 0.95।
ACL injury এবং medial meniscus injury দুটোই MRI-supported।
Difference
Doctor “bucket-handle tear” specify করেছেন। Written MRI report সেটা specify করেনি। সম্ভবত doctor actual MRI images এবং positive McMurray/joint-line tenderness দেখে morphology infer করেছেন। Arthroscopy করলে সেটাই definitiveভাবে যাচাই হতে পারে।
অন্যদিকে আমার Dx-এ MRI/X-ray থেকে moderate effusion, soft-tissue swelling এবং early degenerative changeও explicitly অন্তর্ভুক্ত করেছি।
Prescription-1 Dx
“Painful Rt knee / MRI partial tear of ACL” — এটাও ভুল নয়, তবে incomplete, কারণ provided MRI-তে medial meniscus injury ও effusion-ও আছে।
15. Differential Diagnosis / Associated pathology
এই report-set দেখে প্রধান diagnosis যথেষ্ট clear। Still clinically consider:
- Medial meniscus tear — possible displaced/bucket-handle pattern
- Reactive traumatic synovitis causing effusion
- ACL-related functional instability
- Early post-traumatic degenerative change
- Less likely significant PCL/bony injury, কারণ MRI সেগুলো normal বলেছে।
16. কখন urgent review লাগবে?
Knee পুরো straight করতে না পারা/true locking, recurrent giving-way with falls, rapidly increasing tense swelling, fever + red/hot knee, inability to bear weight after new trauma, অথবা neurovascular symptoms থাকলে দ্রুত orthopaedic assessment দরকার।
Overview / Summary
সব রিপোর্ট একত্রে সবচেয়ে defensible diagnosis হলো:
Right knee high-grade partial ACL tear (~70%) with medial meniscal injury, moderate joint effusion and periarticular soft-tissue swelling, with early radiographic degenerative changes.
বাংলায়:
ডান হাঁটুর ACL প্রায় ৭০% আংশিক ছিঁড়ে গেছে; সাথে medial meniscus injury, হাঁটুর ভিতরে মাঝারি fluid accumulation এবং soft-tissue swelling আছে। X-ray-এ খুব প্রাথমিক degenerative change আছে।
Overall diagnostic confidence: 0.97।
Bucket-handle meniscal tear: treating orthopaedic surgeon suspect করেছেন, কিন্তু supplied written MRI report একে independently confirm করেনি—confidence ~0.60–0.70 until MRI-image review/arthroscopy।
Actionable Plan / Steps
First priority: Sports Medicine/Knee Arthroscopy orthopaedic surgeon দিয়ে actual MRI film review + Lachman/Pivot-shift + ROM/locking assessment। যদি displaced bucket-handle tear/locked knee থাকে, arthroscopic meniscal repair-oriented management দ্রুত consider করা উচিত। যদি knee stable এবং locking না থাকে, structured rehabilitation reasonable; কিন্তু recurrent instability/high-demand pivoting activity/repairable meniscus থাকলে ACL reconstruction ± meniscal repair discuss করতে হবে। AAOS-এর guideline অনুযায়ী surgery indicated হলে unnecessary delay না করাই ভালো।
Prescription-এ provisional Dx হিসেবে সবচেয়ে clinically clean wording:
Dx: High-grade partial ACL tear, Rt knee (~70%) with medial meniscal injury and moderate joint effusion. ?Displaced/bucket-handle medial meniscal tear — for MRI film review/arthroscopic correlation.
General Quaries:- operation ki lagbe naki sudu medicine treatment and physiotherapy dile e valo hobe ?
আপনার দেওয়া MRI + X-ray + দুইটা prescription একসাথে দেখে আমার clinical assessment হলো: এখনই শুধু “70% ACL tear” দেখে operation mandatory বলা যাবে না; আবার শুধু medicine দিয়ে রেখে দেওয়াও ঠিক হবে না। Decisionটা সবচেয়ে বেশি নির্ভর করবে হাঁটু stable নাকি unstable, locking আছে কি না, এবং medial meniscus-এর injury সত্যিই displaced/bucket-handle tear কি না—এর ওপর।
এই patient-এর ক্ষেত্রে কী বেশি যুক্তিসঙ্গত?
MRI-তে high-grade partial ACL tear (~70%), medial meniscus injury এবং moderate effusion আছে। কিন্তু partial ACL tear-এর অনেক patient, যদি knee clinically stable থাকে, structured physiotherapy দিয়ে ভালো function ফিরে পেতে পারে। International ACL consensus অনুযায়ী straight-line activity করতে চাওয়া এবং functional instability না থাকা patient-এ non-operative structured rehabilitation গ্রহণযোগ্য। কিন্তু বারবার knee “giving way” করলে ACL reconstruction indicated হতে পারে।
Confidence: 0.94
এখানে সবচেয়ে গুরুত্বপূর্ণ বিষয় হচ্ছে medial meniscus। দ্বিতীয় orthopaedic doctor examination-এ medial joint-line tenderness + McMurray positive এবং “bucket-handle tear” সন্দেহ করেছেন। যদি সত্যিই displaced bucket-handle tear হয় এবং patient-এর হাঁটু আটকে যায় / পুরো straight হয় না, তাহলে শুধু medicine + physiotherapy দিয়ে অপেক্ষা করা ঠিক হবে না; arthroscopic treatment, preferably meniscal repair when repairable, প্রয়োজন হতে পারে। AAOS-ও displaced meniscal tear যেটা knee motion restrict করে সেখানে early surgical intervention-এর পক্ষে মত দেয়—যদিও তাদের 2024 isolated-meniscus guideline concomitant ACL tear-কে formal scope থেকে exclude করেছে।
Confidence: 0.93
কোন অবস্থায় আগে Physio trial করা যায়?
Operation না করে 6–12 সপ্তাহ supervised rehabilitation reasonable, যদি patient-এর knee পুরো bend/straight হয়, true locking না থাকে, হাঁটু হঠাৎ ভেঙে/give-way না করে, daily walking/stairs মোটামুটি stable থাকে এবং patient pivoting/contact sport-এ দ্রুত ফিরতে না চান।
Physiotherapy-তে প্রধান লক্ষ্য হবে effusion কমানো, full extension/flexion ফিরিয়ে আনা, quadriceps ও hamstring strengthening, hip/core strengthening, proprioception/balance এবং neuromuscular training। Medicine শুধু pain/swelling কমাবে; ACL বা meniscus জোড়া লাগানোর ওষুধ নেই।
Confidence: 0.96
কোন অবস্থায় Operation-এর দিকে যাব?
এই case-এ নিচের যেকোনোটি থাকলে surgery-এর probability অনেক বেড়ে যায়:
- True locking: হাঁটু পুরো straight করা যায় না / mechanical block অনুভব হয়।
- Repeated giving-way/instability, বিশেষ করে হাঁটা, সিঁড়ি বা direction change-এ।
- Clinical Lachman/Pivot-shift clearly positive এবং functional instability।
- MRI film review-এ displaced/bucket-handle medial meniscus tear confirmed।
- Patient football/cricket/badminton বা pivoting/cutting sport-এ ফিরতে চান এবং rehab-এর পরও instability থাকে।
- Adequate structured physiotherapy-এর পরও clinically important symptoms persist।
এই অবস্থায় সম্ভাব্য procedure হবে arthroscopic meniscal repair ± ACL reconstruction; ঠিক কোনটা লাগবে তা actual MRI sequences এবং examination ছাড়া বলা যায় না। ACL surgery indicated হলে অযথা দীর্ঘ delay secondary meniscal/cartilage injury-এর risk বাড়াতে পারে; AAOS acute ACL guideline-এ surgery indicated হলে early reconstruction-এর পক্ষে recommendation আছে।
Confidence: 0.93
আপনার patient-এর জন্য আমার বর্তমান judgement
আমি এখনই “অবশ্যই ACL operation করতে হবে” বলব না। কিন্তু “শুধু medicine খাওয়ালেই ভালো হয়ে যাবে” এটাও বলব না।
সবচেয়ে যুক্তিসঙ্গত next step হচ্ছে Knee Arthroscopy/Sports Orthopaedic Surgeon দিয়ে actual MRI film review + Lachman + Pivot-shift + ROM/locking পরীক্ষা। কারণ report-এর ACL partial tear একা operation-এর indication নয়; সম্ভাব্য bucket-handle meniscus tear-টাই এখানে operation decision বদলে দিতে পারে।
আমার বর্তমান probability-based assessment:
| Clinical situation | Preferred approach |
| Knee stable, locking নেই, full ROM | Physiotherapy first |
| Pain/swelling আছে কিন্তু instability নেই | Physio + short-term symptomatic medicine |
| Repeated giving-way | ACL reconstruction strongly consider |
| True locked knee / displaced bucket-handle tear | Early arthroscopic surgery likely required |
| High-demand pivoting athlete + significant instability | ACL reconstruction ± meniscal repair likely |
আমি Doctor হলে এখন prescription/plan-এ লিখতাম
Dx:
High-grade partial ACL tear, right knee (~70%) with medial meniscal injury and moderate joint effusion; ? displaced/bucket-handle medial meniscal tear.
Plan:
Sports/Knee arthroscopy consultation for MRI-film review and assessment of functional ACL instability and meniscal displacement. If no locking or instability → structured rehabilitation trial. If displaced meniscal tear/locking or persistent instability → arthroscopic meniscal repair ± ACL reconstruction.
Bottom line
শুধু 70% partial ACL tear = automatic operation নয়।
Medicine = শুধু symptom control।
Physiotherapy = non-operative treatment-এর মূল অংশ।
কিন্তু আপনার case-এ medial meniscus/bucket-handle suspicion আছে, তাই surgeon review ছাড়া শুধু medicine + physio চালিয়ে যাওয়া আমি recommend করব না। যদি locking বা repeated giving-way থাকে, operation-এর দিকে যাওয়ার indication যথেষ্ট শক্তিশালী।
Overall confidence: 0.94.
Overview / Summary
এই মুহূর্তে definitive surgery decision-এর জন্য সবচেয়ে missing information হলো true locking আছে কি না, Lachman/Pivot-shift result এবং actual MRI-তে meniscus displaced কি না। Stable knee হলে rehabilitation-এর যথেষ্ট সুযোগ আছে; unstable/locked knee হলে surgery বেশি appropriate।
Actionable Plan
আগামী orthopaedic review-এ সরাসরি তিনটি প্রশ্ন করুন: “ACL functionally unstable কি?”, “Medial meniscus সত্যিই bucket-handle/displaced tear কি?”, “Knee locked না হলে 6–12 weeks structured rehab trial safe কি?” এই তিনটার উত্তর পেলেই operation বনাম conservative treatment-এর সিদ্ধান্ত অনেক পরিষ্কার হবে।
Reference List
Textbooks: Blom A, Warwick D, Whitehouse M, eds. Apley & Solomon’s System of Orthopaedics and Trauma. 10th ed. CRC Press; 2018. Azar FM, Sawyer JR, Throckmorton TW, eds. Campbell’s Operative Orthopaedics. 15th ed. Elsevier; 2026—the current edition, including contemporary knee ligament/meniscal operative principles.
Guidelines: American Academy of Orthopaedic Surgeons. Management of Anterior Cruciate Ligament Injuries: Evidence-Based Clinical Practice Guideline. 2022. AAOS. Management of Acute Isolated Meniscal Pathology. 2024—note that the scope explicitly excludes concomitant ACL injuries. NICE NG226. Osteoarthritis in over 16s: diagnosis and management. 2022.
Peer-reviewed / DOI: Brophy RH, Lowry KJ. AAOS Clinical Practice Guideline Summary: Management of Anterior Cruciate Ligament Injuries. J Am Acad Orthop Surg. 2023;31:531-537. DOI: 10.5435/JAAOS-D-22-01020. Brophy RH, Best MJ, et al. AAOS Clinical Practice Guideline Summary: Management of Acute Isolated Meniscal Pathology. J Am Acad Orthop Surg. 2025;33:e724-e730. DOI: 10.5435/JAAOS-D-25-00135. Diermeier TA, et al. Treatment after ACL injury: Panther Symposium ACL Treatment Consensus Group. Br J Sports Med. 2021. DOI: 10.1136/bjsports-2020-102200.
Md.Rafiqul Islam Lipu