Report Image:-
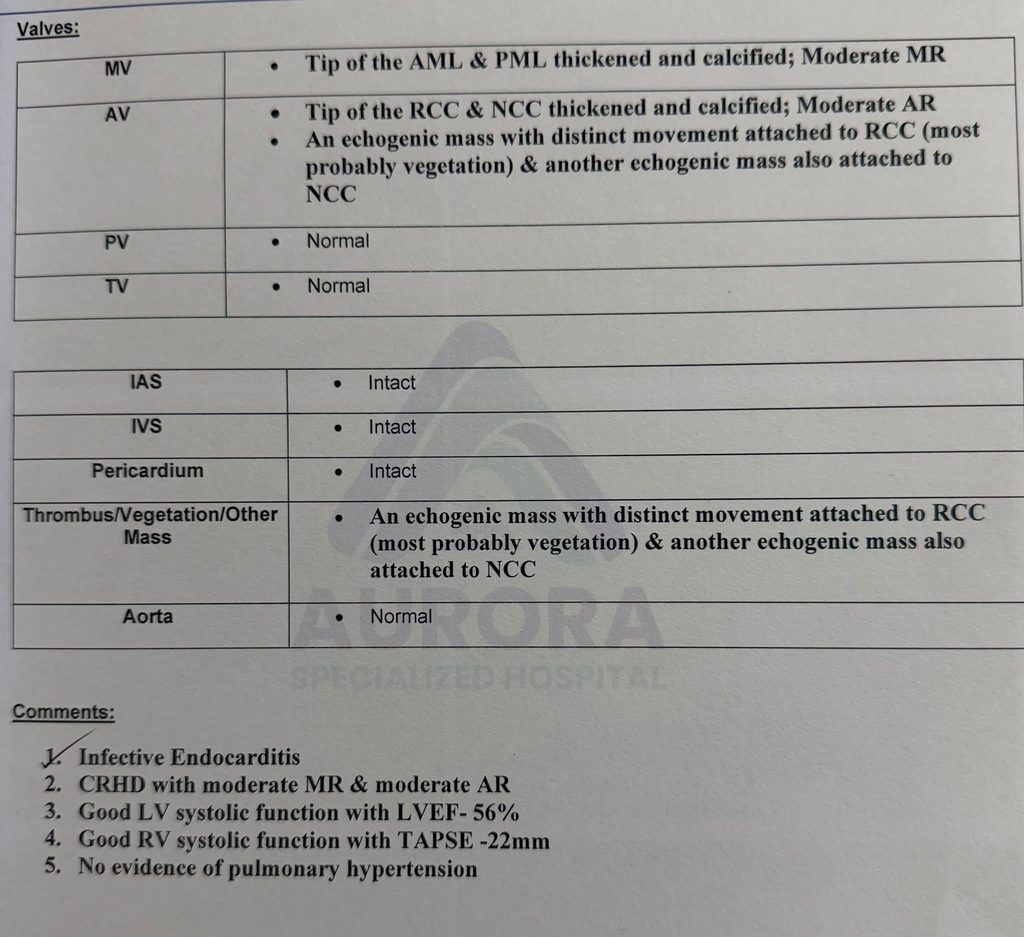
This information has been collected Dr.Mainuddin Sohel
Patient and Doctor er History:-
patient er complain silo gorali betha.
Thorough clinical examination এর বিকল্প নাই! !
ভদ্র মহিলার বয়স ছিলো 55 I গিরা ব্যথার জন্য ভোলা থেকে একজন FCPS ট্রেনি উনাকে আমার কাছে রেফার করে I
জয়েন্ট পেইন এর রুগীরা সাধারণত খুব ভালো হিস্ট্রি দেয়, কিন্তূ এই রুগী খুব ভালো হিস্ট্রি দিতে পারছিলেন না (আসলে উনার সমস্যাগুলি একটু vague ছিলো এবং কম শিক্ষিত ছিলেন)! Rhematologic examination করে দেখি রুগীর তেমন কিছু নাই (যদিও উনি already salazine, cortan মাঝেমধ্যে খাচ্ছিলেন)!
কোনো Rheumatic diagnosis এ পৌঁছাতে না পারার হতাশা নিয়ে যখন রুগীকে ছেড়ে দিবো ভাবছিলাম ঠিক তখনই একটু systemic examination করতে গেলাম (ভিজিট হালাল করার জন্য)! Prechordium এ স্টেথো বসাতেই দেখি murmur!!
একটা কিছু পেয়ে অন্তত হাফ ছেড়ে বাঁচলাম, যদিও এই murmur দিয়ে তখন পর্যন্ত আমি গিরা ব্যথার কারণ মেলাতে পারছিলাম না! তারপর আসলে কাজটা করে দিলেন দক্ষ কার্ডিওলজিস্ট MEHEDI Hasan ভাই! ইকো করে আমাকে ফোনে জানালেন উনার vegetations আছে! একটু পড়লাম, দেখতে পেলাম এইসব রুগীদের arthralgia / myalgia থাকতে পারে!
Actually it was a case of infective endocarditis! !!
Lesson of the story :
Thorough clinical examination এর বিকল্প নাইI
Artharlgia মানেই সবসময় বাত রোগ নয়! diagonosis ki hobe and gorali bethar sate ai report er ki somporkho?
Report analysis:-
এই Echo report-এ সবচেয়ে গুরুত্বপূর্ণ finding হলো aortic valve-এর RCC ও NCC-তে mobile echogenic mass—report অনুযায়ী “most probably vegetation”। তাই এটাকে শুধু valve leakage হিসেবে দেখা ঠিক হবে না; infective endocarditis (IE) urgently exclude/confirm করতে হবে। তবে Echo একা দেখে “definite IE” বলা technically ঠিক নয়—blood culture ও clinical criteria দরকার। ESC/Duke criteria অনুযায়ী vegetation characteristic of IE একটি major imaging criterion।
1. Report-এর abnormal অংশগুলো — 🔴 Marked
| Report finding | বাংলা clinical meaning | Interpretation | Confidence |
| 🔴 Tip of AML & PML thickened and calcified | Mitral valve-এর anterior ও posterior leaflet-এর মাথা মোটা ও calcium জমেছে | Chronic structural/rheumatic valve disease-এর সঙ্গে compatible | 0.95 |
| 🔴 Moderate MR | Mitral valve দিয়ে মাঝারি মাত্রায় রক্ত পিছনে ফিরে যাচ্ছে | Moderate mitral regurgitation | 0.99 |
| 🔴 RCC & NCC thickened and calcified | Aortic valve-এর Right Coronary Cusp ও Non-Coronary Cusp মোটা ও calcified | Chronic aortic valve disease | 0.95 |
| 🔴 Moderate AR | Aortic valve দিয়ে মাঝারি মাত্রায় রক্ত LV-তে ফিরে আসছে | Moderate aortic regurgitation | 0.99 |
| 🔴 Mobile echogenic mass attached to RCC — most probably vegetation | RCC-এর সঙ্গে নড়াচড়া করে এমন mass, যা infection-এর vegetation হওয়ার সম্ভাবনা বেশি | Highly suspicious for IE | 0.90 |
| 🔴 Another echogenic mass attached to NCC | NCC-তেও আরেকটি mass আছে | Second possible vegetation | 0.85 |
| 🔴 Comment: Infective Endocarditis | Echo reader-এর impression IE | Needs microbiological confirmation | 0.70 for definite IE from this report alone |
| 🔴 CRHD with moderate MR & moderate AR | Chronic Rheumatic Heart Disease-এর সঙ্গে moderate mitral ও aortic leak | Important predisposing valve disease | 0.95 |
AML = Anterior Mitral Leaflet, PML = Posterior Mitral Leaflet, MR = Mitral Regurgitation, RCC = Right Coronary Cusp, NCC = Non-Coronary Cusp, AR = Aortic Regurgitation.
2. ভালো / reassuring findings
PV (Pulmonary valve) normal, TV (Tricuspid valve) normal, IAS ও IVS intact, pericardium intact এবং aorta normal।
LVEF 56% → Left ventricular systolic pumping function বর্তমানে preserved/near-normal; overt LV systolic failure নেই।
TAPSE 22 mm → Right ventricular systolic function ভালো।
No pulmonary hypertension → এই report-এ pulmonary artery pressure বৃদ্ধির evidence নেই।
অর্থাৎ, বর্তমানে ventricular function ভালো, কিন্তু এটাতে infective endocarditis-এর গুরুত্ব কমে না।
3. সবচেয়ে accurate Working Diagnosis
Prescription/clinical diagnosis হিসেবে এখন আমি লিখব:
Possible Native Aortic Valve Infective Endocarditis (mobile vegetations over RCC & NCC), on background Chronic Rheumatic Valvular Heart Disease with Moderate AR and Moderate MR; preserved biventricular systolic function; no pulmonary hypertension.
Short form:
Possible NVE (Aortic valve) with CRHD — Moderate AR + Moderate MR.
কেন “Possible”, “Definite” নয়?
Echo-তে vegetation-type lesion পাওয়া major imaging criterion। আবার moderate pre-existing valvular regurgitation IE-এর একটি predisposing condition। কিন্তু definite IE করার জন্য blood-culture/clinical criteria এখনও দরকার। ESC criteria-তে definite IE সাধারণত 2 major criteria, অথবা নির্দিষ্ট major + minor combination দিয়ে established হয়।
তাই:
Echo-based suspected/possible IE confidence: 0.90
Definite active infective endocarditis confidence from this report alone: ~0.70
যদি typical organism ≥2 appropriate blood-culture sets-এ positive হয়, তখন imaging major + microbiological major মিলিয়ে Definite Infective Endocarditis হবে।
4. Definition & Pathophysiology
Infective Endocarditis হলো heart valve/endocardial surface-এর microbial infection, যেখানে platelet-fibrin ও microorganism মিলে vegetation তৈরি করতে পারে।
এই রোগীর ক্ষেত্রে আগে থেকেই abnormal rheumatic valve surface থাকার কারণে bacteremia হলে microorganism valve-এ attach করার সুযোগ বাড়ে। Common organisms-এর মধ্যে Staphylococcus aureus, streptococci এবং Enterococcus spp. গুরুত্বপূর্ণ।
5. Clinical features এখন specifically খুঁজতে হবে
Patient-এর history/physical examination-এ fever >38°C, chills, prolonged weakness, weight loss, new/worsening murmur, dyspnoea, petechiae, splenomegaly, hematuria, focal neurological deficit/stroke symptoms, back pain, abdominal/flank pain বা peripheral embolic phenomena আছে কি না খুঁজতে হবে।
বিশেষ করে fever + this echo finding থাকলে IE suspicion খুব high হবে।
6. এখন কোন investigations করব?
| Priority | Investigation | কেন |
| URGENT | Blood culture × 3 sets BEFORE antibiotics | Organism identify + antibiotic sensitivity |
| URGENT | TEE/TOE — Transesophageal Echo | Vegetation-এর exact size, mobility, valve destruction, perforation, abscess দেখা |
| High | CBC with differential | Leukocytosis/anemia/thrombocytopenia |
| High | CRP ± ESR | Inflammatory activity ও follow-up |
| High | Serum creatinine, urea, electrolytes | IE renal involvement + antibiotic dosing |
| High | LFT | Baseline before prolonged antibiotics |
| High | Urine R/M/E ± urine protein | Microscopic hematuria/glomerulonephritis |
| High | ECG | PR prolongation/new AV block → aortic root abscess suspicion |
| Depending on symptoms | CXR, BNP/troponin | HF/cardiac involvement |
| If neurological symptoms | CT/MRI brain | Septic embolus/stroke |
| If abdominal/flank symptoms | CT abdomen | Splenic/renal emboli or abscess |
| If persistent back pain | MRI spine | Spondylodiscitis/vertebral infection |
| If culture negative | Bartonella/Coxiella etc. work-up with microbiology/ID | Blood-culture-negative IE evaluation |
ESC specifically recommends at least 3 sets of peripheral blood cultures before antibiotics and strongly supports TEE even when TTE is already positive, because TEE is better for vegetation characterization and perivalvular complications.
এই report-এর সবচেয়ে বড় missing information
Vegetation-এর size (mm) লেখা নেই।
এটা অবশ্যই TEE-তে measure করা দরকার, কারণ vegetation size embolic risk এবং surgery decision-এ গুরুত্বপূর্ণ।
7. Treatment Plan
এটা routine outpatient oral-antibiotic case হিসেবে treat করা উচিত নয়। Left-sided aortic valve IE সন্দেহ হলে tertiary-care evaluation প্রয়োজন।
Doctor-এর immediate action plan
- আজই Cardiology/tertiary hospital assessment করুন। Patient febrile/septic, hypotensive, breathless, confused, নতুন weakness/paralysis, chest pain বা pulmonary edema থাকলে immediate admission/emergency management।
- Patient stable থাকলে antibiotic দেওয়ার আগে 3 sets blood culture নিতে হবে। ইতোমধ্যে antibiotic খেলে অবশ্যই name/dose/duration note করতে হবে—এতে culture negative হতে পারে।
- এরপর clinical suspicion যথেষ্ট থাকলে hospital-based IV empirical antibiotic শুরু হবে। Community-acquired native-valve IE-এর ESC empirical options-এর মধ্যে ampicillin + ceftriaxone, অথবা পরিস্থিতি অনুযায়ী ampicillin + (flu)cloxacillin + gentamicin রয়েছে; তবে renal function, allergy, previous antibiotics, MRSA/local resistance ও patient-specific factors দেখে Endocarditis/ID team regimen ঠিক করবে। Culture result পাওয়ার পর targeted antibiotic-এ change করতে হবে।
- TEE urgently করুন। Vegetation size, cusp perforation, aortic root abscess বা other local complication আছে কি না দেখতে হবে। Positive TTE-এর পরও TEE recommended।
- Organism পাওয়া গেলে antibiotic pathogen অনুযায়ী নির্বাচন হবে—যেমন susceptible streptococci-তে penicillin/ceftriaxone-based regimen, MSSA-তে anti-staphylococcal beta-lactam, MRSA-তে vancomycin/daptomycin-based regimen, এবং E. faecalis-এ ampicillin + ceftriaxone commonly used। Left-sided NVE-তে treatment সাধারণত prolonged IV therapy এবং organism অনুযায়ী প্রায় 4–6 weeks হয়; exact duration culture এবং complications-এর ওপর নির্ভর করে।
- Cardiac surgery/CTVS early opinion নিন—এর মানে এখনই surgery লাগবে এমন নয়। এই report-এ moderate AR/MR, preserved ventricular function ও no pulmonary hypertension থাকায় শুধু এই echo report দেখে immediate valve replacement indication প্রমাণিত হয়নি। Surgery প্রয়োজন হয় বিশেষত heart failure/severe acute valve dysfunction, abscess বা uncontrolled infection, persistent sepsis/positive cultures, কিংবা significant embolic-risk vegetation-এর ক্ষেত্রে।
8. Surgery লাগবে কি?
এই report দেখে এখনই “operation অবশ্যই লাগবে” বলা যাবে না।
বর্তমানে আছে moderate AR + moderate MR, LVEF 56%, good RV function এবং pulmonary hypertension নেই। তাই hemodynamic picture আপাতত relatively preserved।
কিন্তু TEE-তে যদি vegetation ≥10 mm, abscess, leaflet perforation বা increasing vegetation পাওয়া যায়; অথবা embolism, persistent infection কিংবা severe regurgitation/HF হয়—তখন early/urgent surgery consideration অনেক শক্তিশালী হবে। ESC অনুযায়ী প্রধান surgical indications হলো heart failure, uncontrolled infection এবং prevention of septic embolization।
আরেকটি গুরুত্বপূর্ণ কথা: antibiotic infection cure করতে পারে, কিন্তু pre-existing rheumatic/calcified valve damage বা moderate MR/AR সরাসরি “সারিয়ে” দেয় না। Infection cure হওয়ার পর residual valve disease follow-up করতে হবে।
9. Differential Diagnosis
Echo masses-এর ক্ষেত্রে alternative possibilities হলো degenerative/calcific valvular lesion, Lambl’s excrescence, papillary fibroelastoma, thrombus অথবা non-bacterial thrombotic endocarditis। কিন্তু এই report-এ mobile mass + RCC/NCC involvement এবং reporting cardiologist-এর “most probably vegetation / infective endocarditis” impression থাকার কারণে infective vegetation বর্তমানে প্রধান concern।
TEE + blood cultures differential narrow করবে।
10. কোন Doctor-এর কাছে Refer করবেন?
সবচেয়ে ভালো হলো Endocarditis Team:
Cardiologist + Infectious Disease/Internal Medicine specialist + Cardiothoracic/Cardiac Surgeon + Clinical Microbiology।
Complicated IE হলে Heart Valve Centre/centre with cardiac surgery facilities-এ management guideline-supported।
Prescription-এ Referral Note এভাবে লিখতে পারেন:
Urgent referral to Cardiology/Endocarditis Team (Cardiology + ID/Medicine + CTVS). Echocardiography shows mobile echogenic masses attached to RCC and NCC of native aortic valve, highly suspicious for vegetations, with CRHD, moderate AR and moderate MR; LVEF 56%, TAPSE 22 mm, no pulmonary hypertension. Kindly evaluate for native aortic valve infective endocarditis. Please obtain blood cultures before antimicrobial therapy where clinically feasible, arrange urgent TEE for vegetation size/local complications, initiate appropriate IV antimicrobial therapy and assess need for early cardiac surgery.
Prescription-এর Dx line:
Dx: Possible Native Aortic Valve Infective Endocarditis (vegetations over RCC & NCC) with CRHD—Moderate AR + Moderate MR.
Blood culture/clinical criteria confirm হলে:
Dx: Definite Native Aortic Valve Infective Endocarditis with CRHD—Moderate AR + Moderate MR.
প্রেসক্রিপশনে যে Diagnosis-টা লিখতে বলেছিলাম, তার সহজ বাংলা হবে:
সম্ভাব্য নেটিভ অ্যাওর্টিক ভালভ ইনফেকটিভ এন্ডোকার্ডাইটিস—অর্থাৎ নিজের অ্যাওর্টিক ভালভে সংক্রমণ হয়েছে বলে প্রবল সন্দেহ এবং ভালভের RCC ও NCC অংশে নড়াচড়া করা vegetation/সংক্রমিত জমাট অংশ দেখা যাচ্ছে। এর সঙ্গে পুরোনো Rheumatic Heart Disease আছে, যার কারণে Mitral valve ও Aortic valve—দুটিতেই মাঝারি মাত্রায় রক্ত লিক করছে (Moderate MR + Moderate AR)। তবে বর্তমানে হার্টের বাম ও ডান পাশের pumping function ভালো আছে এবং Pulmonary Hypertension নেই।
আরও সহজভাবে রোগীকে বলতে পারেন
হার্টের একটি ভালভে জীবাণুর সংক্রমণ হয়েছে বলে রিপোর্টে সন্দেহ করা হয়েছে। ভালভে infection-এর কারণে ছোট নড়াচড়া করা মাংসপিণ্ডের মতো vegetation দেখা যাচ্ছে। একই সঙ্গে পুরোনো rheumatic valve disease-এর কারণে দুটি valve মাঝারি মাত্রায় leak করছে। তবে ভালো দিক হলো, বর্তমানে হার্টের pumping ক্ষমতা ভালো আছে।
Prescription-এ Dx লিখবেন
Possible Native Aortic Valve Infective Endocarditis with CRHD, Moderate MR & Moderate AR.
বাংলায়:
সম্ভাব্য অ্যাওর্টিক ভালভ সংক্রমণ (Infective Endocarditis) সহ Chronic Rheumatic Heart Disease, Moderate Mitral ও Aortic Regurgitation।
⚠️ এখানে “Possible” লেখা গুরুত্বপূর্ণ—শুধু Echo দেখে ১০০% নিশ্চিত Infective Endocarditis বলা যাবে না। Blood culture + clinical findings + TEE মিলিয়ে নিশ্চিত করতে হবে।
গোড়ালির ব্যথার সঙ্গে ইকোকার্ডিওগ্রামের রিপোর্টের পরোক্ষ কিন্তু গুরুত্বপূর্ণ সম্পর্ক থাকতে পারে।
Lets Exclude the cause:- ইকোতে হার্টের ভালভে সংক্রমণের জমাট অংশ বা ভেজিটেশন (Infective Endocarditis-এর সন্দেহ) দেখা গেছে। এই ধরনের হার্টের ভালভের সংক্রমণ হলে শরীরে প্রদাহ ও রোগপ্রতিরোধজনিত প্রতিক্রিয়া তৈরি হয়, যার কারণে গোড়ালি, হাঁটু বা অন্যান্য জয়েন্টে ব্যথা (Arthralgia) হতে পারে।
সহজভাবে লিখতে পারেন:
“রোগীর গোড়ালির ব্যথা শুধুমাত্র বাতজনিত নাও হতে পারে। ইকোকার্ডিওগ্রামে হার্টের ভালভে সংক্রমণজনিত ভেজিটেশন দেখা যাওয়ায়, Infective Endocarditis-এর systemic manifestation হিসেবে এই গোড়ালির ব্যথা হতে পারে।”
আরও ছোট করে:
“হার্টের ভালভের সংক্রমণের কারণে শরীরে প্রদাহ তৈরি হয়ে গোড়ালিসহ বিভিন্ন জয়েন্টে ব্যথা হতে পারে; তাই এই রোগীর গোড়ালির ব্যথার সঙ্গে ইকোর অস্বাভাবিক finding-এর সম্পর্ক থাকতে পারে।”
হ্যাঁ—এই রোগীর গোড়ালি/জয়েন্টের ব্যথার সঙ্গে Echo-তে দেখা suspected infective endocarditis-এর সম্পর্ক থাকতে পারে, এবং clinically এটা যথেষ্ট গুরুত্বপূর্ণ association।
সবচেয়ে যুক্তিসঙ্গত Working Diagnosis
Possible native aortic valve infective endocarditis with musculoskeletal manifestation (arthralgia), on background CRHD with moderate AR + moderate MR.
বাংলায়: পুরোনো rheumatic valvular heart disease-এর ওপর aortic valve-এ সম্ভাব্য সংক্রমণ/vegetation, যার systemic manifestation হিসেবে গোড়ালিসহ জয়েন্টে ব্যথা হতে পারে।
Confidence: 0.90 যে Echo-টি IE-এর জন্য highly suspicious।
Confidence: ~0.75 যে গোড়ালির ব্যথাটি IE-related arthralgia—কারণ joint examination, fever history, inflammatory markers ও blood culture এখনও জানা নেই।
গোড়ালি ব্যথা কেন হতে পারে?
Infective endocarditis শুধু হার্টের রোগ নয়; এটি একটি systemic infection। এতে inflammatory cytokine ও immune response-এর কারণে arthralgia (জয়েন্টে ব্যথা), myalgia, back pain হতে পারে। পুরোনো ESC data-তে IE রোগীদের প্রায় 10% এ arthralgia এবং প্রায় 14% এ peripheral arthritis reported হয়েছে। কখনও rheumatological symptom-ই রোগের প্রথম presentation হতে পারে।
আরও গুরুত্বপূর্ণ হলো, bacteremia থেকে জীবাণু সরাসরি কোনো joint-এ গেলে septic arthritis হতে পারে। তাই গোড়ালি যদি ফোলা + গরম + লাল + খুব tender + নড়াতে প্রচণ্ড ব্যথা হয়, তখন এটাকে simple arthralgia ধরে নেওয়া যাবে না—septic arthritis urgently exclude করতে হবে।
এই রোগীর ক্ষেত্রে সম্পর্কটা আমি এভাবে দেখব
Echo: RCC ও NCC-তে mobile echogenic mass → vegetation সন্দেহ → IE-এর major imaging evidence হিসেবে গুরুত্বপূর্ণ।
Symptom: vague ankle/joint pain → IE-এর পরিচিত musculoskeletal manifestation হতে পারে।
Murmur + valve disease + vegetation + joint pain একসাথে থাকলে IE-এর clinical suspicion যথেষ্ট বেড়ে যায়।
তবে joint pain Duke criterion নয়। তাই “গোড়ালি ব্যথা আছে + vegetation আছে = definite IE”—এভাবে diagnosis করা যাবে না। Definite diagnosis-এর জন্য বিশেষ করে blood culture + clinical criteria প্রয়োজন।
কোন পরিস্থিতিতে অন্য কারণ বেশি ভাববেন?
যদি ব্যথা শুধু heel-এর নিচে হয়, সকালে প্রথম হাঁটার সময় বেশি হয় এবং joint swelling না থাকে, তাহলে plantar fasciitis-এর মতো local cause বেশি সম্ভাব্য। আবার acute red-hot swollen joint হলে septic arthritis বা crystal arthritis; symmetrical small-joint swelling/morning stiffness থাকলে inflammatory rheumatic disease আলাদাভাবে evaluate করতে হবে।
এখন Doctor-এর practical action
৩ সেট blood culture antibiotic দেওয়ার আগে, CBC, CRP/ESR, creatinine, urine R/M/E এবং TEE করা সবচেয়ে গুরুত্বপূর্ণ। Ankle joint ফোলা থাকলে ultrasound ± joint aspiration for cell count, Gram stain and culture করতে হবে। Echo-তে vegetation IE-এর major imaging criterion; TEE vegetation-এর size ও abscess/perforation ভালোভাবে নির্ধারণ করতে সাহায্য করে।
আর রোগী যদি rheumatic pain ভেবে Cortan/steroid বা অন্য immunosuppressive drug খেয়ে থাকেন, infection exclude না করে dose বাড়ানো উচিত নয়। দীর্ঘদিন steroid খেলে আবার হঠাৎ বন্ধও করা যাবে না—dose/duration দেখে physician taper করবেন।
Prescription-এ Diagnosis:-
Dx: Possible Native Aortic Valve Infective Endocarditis with IE-associated Arthralgia, on background CRHD with Moderate AR & Moderate MR.
আর যদি blood culture/অন্যান্য Duke criteria পূরণ হয়:
Definite Native Aortic Valve Infective Endocarditis with musculoskeletal manifestation (arthralgia), CRHD with Moderate AR & MR.
Overview / Summary
হ্যাঁ, গোড়ালি/জয়েন্টের ব্যথা এই infective endocarditis-এর manifestation হতে পারে। IE অনেক সময় rheumatologic disease-এর মতো arthralgia/myalgia দিয়ে প্রথমে ধরা দেয়। কিন্তু isolated ankle pain-এর অন্য কারণও আছে, তাই causal relation নিশ্চিত করতে examination ও microbiological confirmation দরকার।
Actionable Plan
Blood culture ×3 → CBC/CRP/ESR/renal profile/urine → TEE → ankle examination → swollen joint হলে aspiration → Cardiology + Medicine/ID review → culture-guided IE treatment।
References
Delgado V, et al. 2023 ESC Guidelines for the management of endocarditis. Eur Heart J. 2023;44:3948–4042. DOI: 10.1093/eurheartj/ehad193.
Fowler VG Jr, et al. 2023 Duke-ISCVID Criteria for Infective Endocarditis. Clin Infect Dis. 2023;77:518–526. DOI: 10.1093/cid/ciad271.
Habib G, et al. 2015 ESC Guidelines for the management of infective endocarditis—musculoskeletal manifestations section. Eur Heart J. 2015;36:3075–3128. DOI: 10.1093/eurheartj/ehv319.
Overview / Summary
এই report-এর সবচেয়ে serious abnormality হলো aortic valve RCC এবং NCC-তে suspected vegetation। Background-এ Chronic Rheumatic Heart Disease with moderate MR and moderate AR রয়েছে। Positive দিক হলো LVEF 56%, TAPSE 22 mm, no pulmonary hypertension।
Final working diagnosis: Possible native aortic-valve infective endocarditis on CRHD. Echo suspicion high (0.90), কিন্তু definite IE বলার জন্য blood culture/clinical Duke criteria দরকার (বর্তমান data-তে confidence ~0.70)।
Actionable Plan / Steps
Same-day Cardiology/Endocarditis-Team review → 3 sets blood cultures before antibiotics → CBC/CRP/renal/LFT/urine/ECG → urgent TEE → IV antibiotic based on clinical setting → culture-directed therapy → early CTVS review → screen for embolic/abscess complications when indicated.
Patient যদি বর্তমানে high fever/sepsis, BP low, severe breathlessness, pulmonary edema, confusion, sudden weakness/paralysis বা chest pain-এ থাকে, outpatient investigation না করে emergency hospital admission উপযুক্ত।
Reference List
Textbook: Harrison’s Principles of Internal Medicine, 22nd ed. McGraw Hill. Section/Chapter on Infective Endocarditis and valvular heart disease. Page numbering print/eBook অনুযায়ী ভিন্ন হওয়ায় আমি unverified page number দিচ্ছি না।
Guideline: Delgado V, et al. 2023 ESC Guidelines for the management of endocarditis. European Heart Journal. 2023;44:3948–4042. DOI: 10.1093/eurheartj/ehad193.
Diagnostic criteria: Fowler VG Jr, et al. The 2023 Duke–International Society for Cardiovascular Infectious Diseases Criteria for Infective Endocarditis. Clinical Infectious Diseases. 2023;77:518–526. DOI: 10.1093/cid/ciad271. Valvular guideline: Otto CM, et al. 2020 ACC/AHA Guideline for the Management of Patients With Valvular Heart Disease. Circulation. DOI: 10.1161/CIR.0000000000000923.
Md.Rafiqul Islam Lipu.