বাংলাDX: ভাইরাসজনিত জ্বরসহ উপরের শ্বাসতন্ত্রের সংক্রমণ।
(Prescription+Report)attached:-
Shortcut:
Viral → WBC normal/low + neutrophil normal/low + lymphocyte relatively high
Bacterial → WBC high + neutrophil high + left shift (Left shift মানে CBC/differential-এ immature neutrophil, বিশেষ করে band neutrophil বেশি পাওয়া। Neutrophilia + bands/immature granulocytes ↑ = left shift)
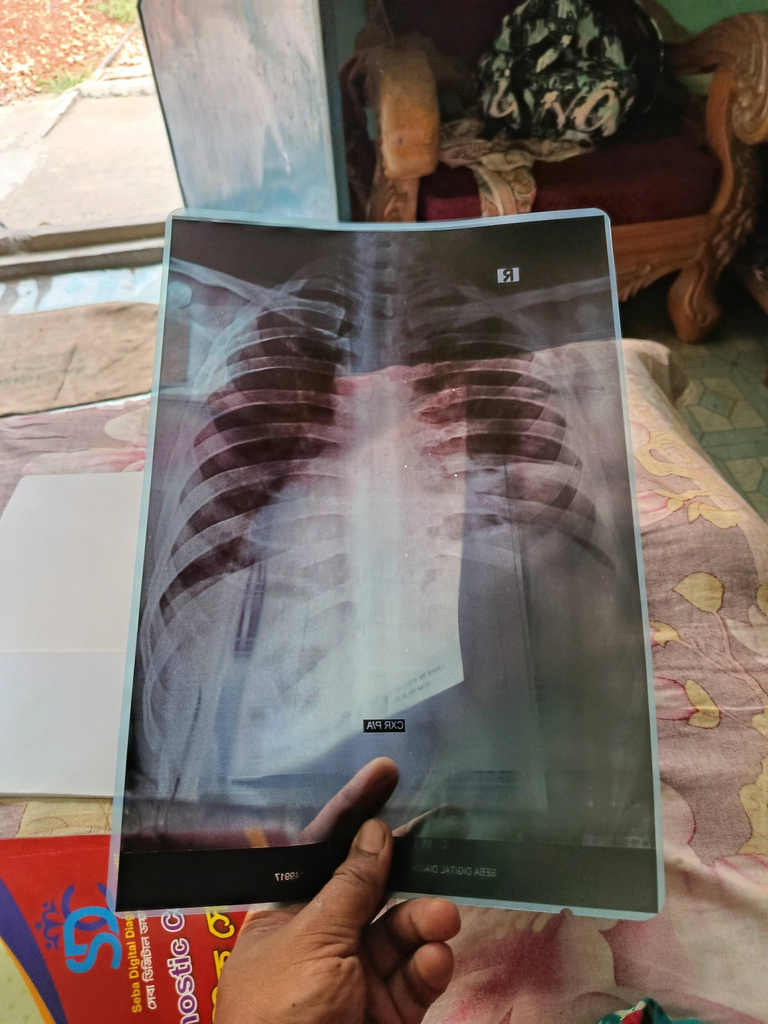
আমি ৪টি ছবিই মিলিয়ে দেখেছি—Urine R/E, Dengue serology, CBC এবং CXR film। সবচেয়ে গুরুত্বপূর্ণ কথা হলো: এই রিপোর্টগুলো থেকে “confirmed dengue”, “confirmed UTI” বা “confirmed pneumonia” লেখা ঠিক হবে না। সবচেয়ে defensible clinical working diagnosis হচ্ছে acute febrile/inflammatory illness, source not yet established। কারণ ইতিহাস—জ্বর কতদিন, কাশি/শ্বাসকষ্ট, dysuria, abdominal symptoms, BP/SpO₂—দেওয়া নেই এবং CXR-এর ছবিটি formal diagnostic-quality image নয়।
1. প্রধান abnormal findings — marked
| Finding | Result | Clinical interpretation / বাংলা অর্থ | Confidence |
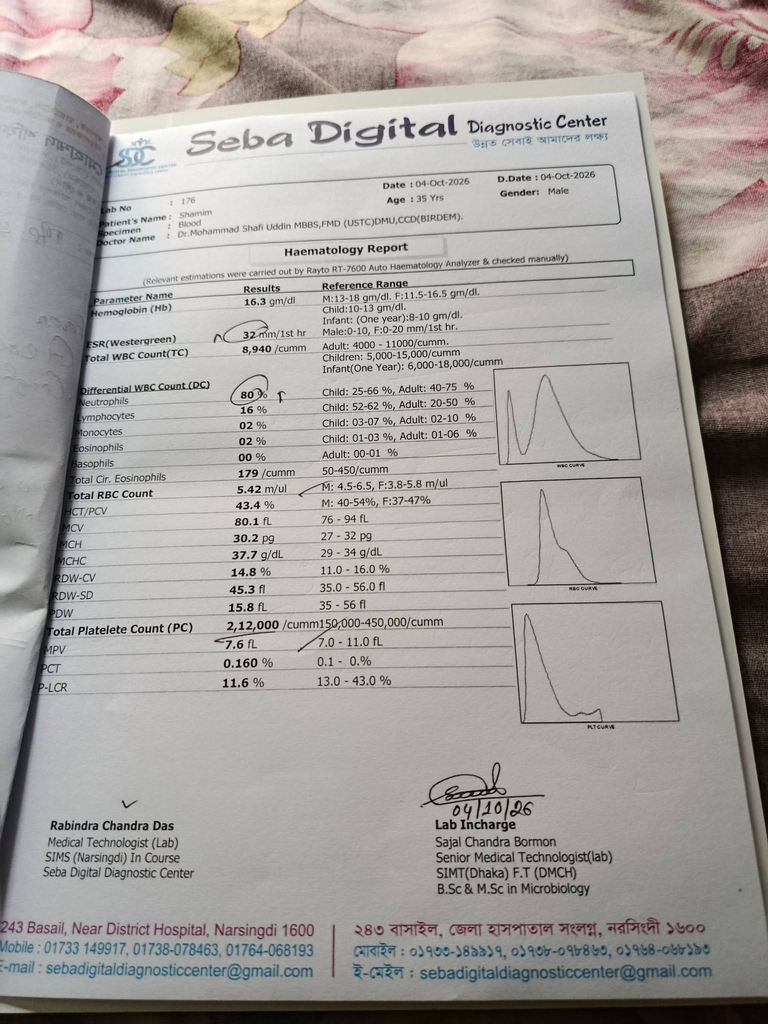
| 🔴 ESR | 32 mm/1st hr | Raised ESR — প্রদাহ/সংক্রমণের nonspecific marker বৃদ্ধি পেয়েছে। এটি একা কোনো রোগ diagnose করে না। | 0.98 |
| 🔴 Neutrophils | 80% | Relative neutrophilia — neutrophil percentage বেশি। Infection/inflammation, stress response ইত্যাদিতে হয়। | 0.98 |
| 🟡 Lymphocytes | 16% | Percentage কম; কিন্তু calculated absolute lymphocyte count ≈ 1.43 ×10⁹/L, তাই severe absolute lymphopenia নয়। | 0.94 |
| 🔴 MCHC | 37.7 g/dL | Reference-এর ওপরে। Isolated high MCHC অনেক সময় analyzer/sample artifact; repeat CBC + peripheral smear দরকার হলে confirm করা যায়। | 0.90 |
| 🟡 P-LCR | 11.6% | Lab reference 13–43%; সামান্য কম। Platelet count স্বাভাবিক থাকায় isolated finding সাধারণত major concern নয়। | 0.88 |
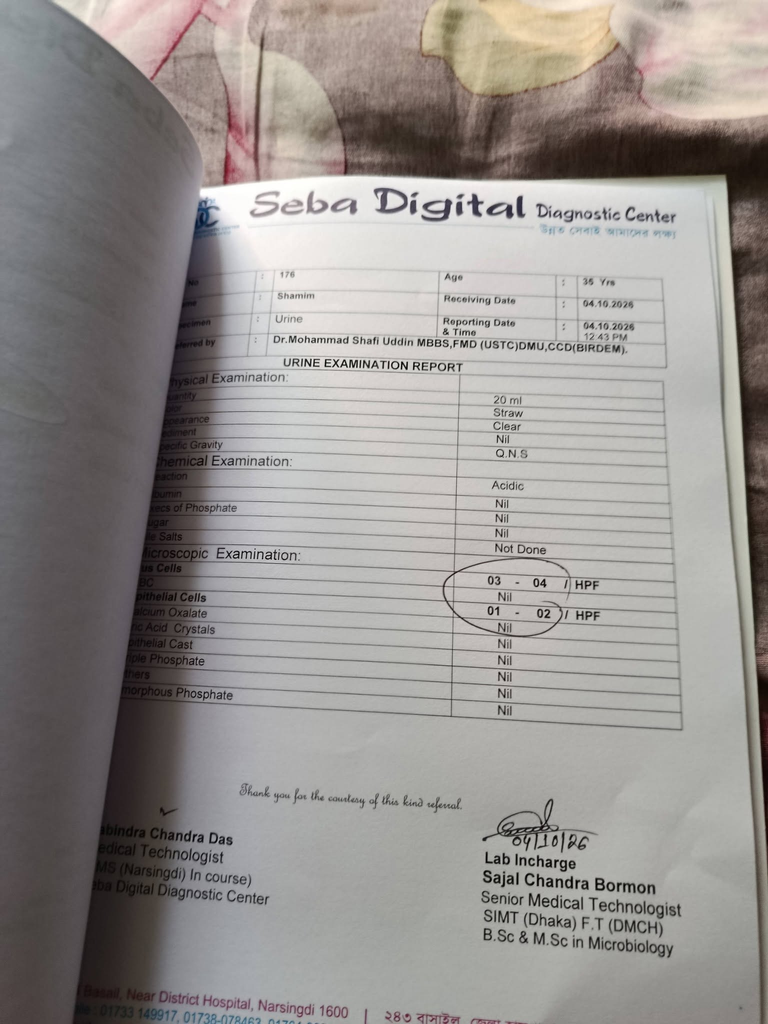
| 🟡 Urine pus cell | 3–4/HPF | Very mild/borderline pyuria. এটা দিয়ে UTI diagnose করা যায় না, বিশেষ করে urinary symptoms না থাকলে। | 0.97 |
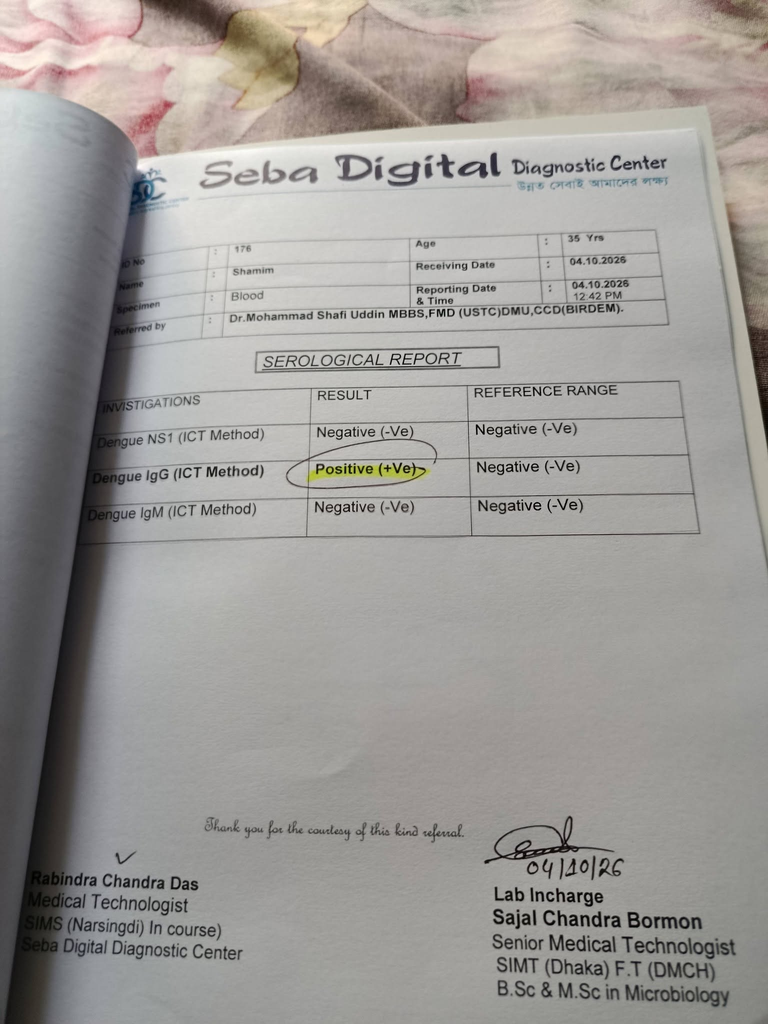
| 🔴 Dengue IgG | Positive | Dengue antibody আছে—সাধারণত previous dengue exposure/infection নির্দেশ করে; একক IgG acute dengue প্রমাণ করে না। | 0.97 |
| 🟢 Dengue NS1 | Negative | Current early dengue-এর laboratory confirmation পাওয়া যায়নি। তবে খুব early/late sample হলে negative test একেবারে exclude করে না। | 0.94 |
| 🟢 Dengue IgM | Negative | Recent dengue-এর serologic evidence নেই। Illness >7 দিন হলে recent dengue আরও কম সম্ভাব্য। | 0.93 |
| 🟢 Platelet | 212,000/cumm | স্বাভাবিক; thrombocytopenia নেই। | 0.99 |
CDC স্পষ্টভাবে বলে, একটি single positive dengue IgG acute dengue diagnosis-এর জন্য ব্যবহার করা উচিত নয়; acute phase-এ NS1/NAAT-এর সঙ্গে IgM interpretation করতে হয়।
2. CBC / Haematology — English + বাংলা interpretation
| Test | Result | Interpretation |
| Hemoglobin (Hb) | 16.3 g/dL | Normal male Hb — রক্তস্বল্পতা নেই |
| 🔴 ESR | 32 mm/hr | High — প্রদাহ/ইনফেকশনের nonspecific evidence |
| Total WBC | 8,940/cumm | Normal — মোট শ্বেতকণিকা স্বাভাবিক |
| 🔴 Neutrophils | 80% | High percentage — relative neutrophilia |
| 🟡 Lymphocytes | 16% | Relative low percentage |
| Monocytes | 2% | Normal/lower end |
| Eosinophils | 2% | Normal |
| Basophils | 0% | Normal |
| Total circulating eosinophil | 179/cumm | Normal |
| RBC count | 5.42 million/µL | Normal |
| HCT/PCV | 43.4% | Normal |
| MCV | 80.1 fL | Low-normal; overt microcytosis নেই |
| MCH | 30.2 pg | Normal |
| 🔴 MCHC | 37.7 g/dL | Raised — repeat CBC/smear if persistent |
| RDW-CV | 14.8% | Normal |
| RDW-SD | 45.3 fL | Normal |
| PDW | 15.8 fL | Acceptable |
| Platelet | 212,000/cumm | Normal platelet count |
| MPV | 7.6 fL | Normal-low range |
| PCT | 0.160% | Generally acceptable; report reference printing appears unclear |
| 🟡 P-LCR | 11.6% | Mildly low; isolated finding usually insignificant |
একটা গুরুত্বপূর্ণ nuance: WBC 8,940 × neutrophil 80% ≈ ANC 7.15 ×10⁹/L। অর্থাৎ percentage neutrophilia আছে, কিন্তু severe absolute neutrophilia নয়। তাই শুধু এই CBC দেখে “bacterial infection confirmed” বলা যাবে না।
3. Dengue report — clinically সবচেয়ে গুরুত্বপূর্ণ অংশ
NS1 Negative + IgM Negative + IgG Positive এর সবচেয়ে সম্ভাব্য অর্থ:
Past dengue infection/exposure — acute dengue NOT confirmed
Confidence: 0.94
IgG অনেক বছর, এমনকি দীর্ঘমেয়াদে positive থাকতে পারে। তাই শুধু IgG positive দেখে prescription-এ “Dengue Fever” লেখা উচিত নয়। CDC অনুযায়ী acute illness-এর প্রথম 0–7 দিনে NS1 + IgM অথবা NAAT/RT-PCR + IgM সবচেয়ে উপযুক্ত; NS1 negative হলেও clinical suspicion থাকলে dengue পুরোপুরি exclude হয় না। >7 দিন illness হলে IgM প্রধান test।
একটি caveat: secondary dengue-তে IgG early rise করতে পারে এবং NS1 sensitivity কম হতে পারে। তাই যদি বর্তমানে classic dengue symptoms থাকে এবং illness-এর day জানা যায়, testing strategy পুনর্বিবেচনা করা উচিত।
4. Urine R/E — English + বাংলা
| Parameter | Result | Meaning |
| Quantity | 20 mL | Sample volume |
| Color | Straw | Normal — স্বাভাবিক রং |
| Appearance | Clear | Normal — পরিষ্কার |
| Sediment | Nil | Normal |
| Specific gravity | QNS | Proper result পাওয়া যায়নি / inadequate for measurement |
| Reaction | Acidic | Normal physiological finding |
| Albumin | Nil | Proteinuria নেই |
| Phosphate | Nil | No significant abnormality |
| Sugar | Nil | Urine glucose নেই |
| Bile salts | Not done | পরীক্ষা করা হয়নি |
| 🟡 Pus cells | 3–4/HPF | Mild/borderline WBC; alone ≠ UTI |
| RBC | Nil | Hematuria নেই |
| Epithelial cells | 1–2/HPF | Small amount, acceptable |
| Calcium oxalate | Nil | No crystals |
| Uric acid crystals | Nil | No crystals |
| Epithelial cast | Nil | No cast detected |
| Triple phosphate | Nil | No crystals |
| Others | Nil | No additional finding |
| Amorphous phosphate | Nil | No significant finding |
UTI diagnosis এখানে established নয়। Dysuria, frequency, urgency, suprapubic pain, fever/CVA tenderness ইত্যাদি clinical symptoms ছাড়া borderline pyuria-র জন্য antibiotic শুরু করা উচিত নয়। IDSA-ও UTI diagnosis-এ symptoms ও appropriate urine testing/culture-কে গুরুত্ব দেয়।
5. Chest X-ray
এখানে সবচেয়ে গুরুত্বপূর্ণ limitation আছে। Filmটি হাতে ধরে photograph করা হয়েছে; film curved, reflection/glare আছে, lower lung/cardiac regions partly obscured, এবং “R” marker/photo orientation mirrored মনে হচ্ছে। তাই এই photograph থেকে pneumonia, TB, cardiomegaly বা hilar pathology confidently diagnose করা নিরাপদ নয়।
আমার assessment:
CXR = technically inadequate for definitive radiological diagnosis from this photograph. Confidence 0.99.
আমি এটাকে দেখে “pneumonia আছে” বা “CXR normal” কোনোটাই confidently লিখব না। Original digital image অথবা radiologist-written report / repeat proper PA chest দরকার।
6. সবচেয়ে যুক্তিসঙ্গত Working Diagnosis
Prescription-এ বর্তমানে লিখতে চাইলে সবচেয়ে clinically defensible wording:
Working Dx
Acute febrile/inflammatory illness – etiology under evaluation, with relative neutrophilia and raised ESR. Acute dengue not confirmed; isolated dengue IgG positivity consistent with previous exposure. Mild pyuria without established UTI.
বাংলায়:
তীব্র জ্বর/প্রদাহজনিত অসুস্থতা—কারণ এখনো নিশ্চিত নয়; neutrophil percentage ও ESR বৃদ্ধি পেয়েছে। বর্তমান পরীক্ষায় acute dengue প্রমাণিত নয়; dengue IgG positivity পূর্বের infection/exposure-এর পক্ষে। Urine-এ সামান্য pus cell আছে, কিন্তু UTI নিশ্চিত নয়।
Overall confidence: 0.93.
যেগুলো এখন লেখা ঠিক হবে না
“Confirmed Dengue Fever” — না।
“Confirmed UTI” — না।
“Bacterial pneumonia” — এই CXR photograph দিয়ে না।
7. Differential Diagnosis
বর্তমানে clinical symptoms না থাকায় differential থাকবে acute viral febrile illness, bacterial inflammatory/infective illness with source yet unidentified, এবং symptoms থাকলে lower respiratory tract infection/CAP বা symptomatic UTI। Acute dengue এখন laboratory-confirmed নয়, তবে illness-এর exact day না জানার কারণে 100% exclude করা যাচ্ছে না।
8. এখন Doctor-এর Action Plan
- আজই clinical reassessment: temperature, BP, pulse, respiratory rate, SpO₂, hydration, urine output; chest auscultation, abdomen, rash/bleeding, CVA tenderness দেখবেন।
- Repeat CBC + HCT + Platelet যদি জ্বর চলমান থাকে, বিশেষ করে dengue suspicion থাকলে 24 ঘণ্টার মধ্যে। Dengue-এর critical phase সাধারণত defervescence-এর আশেপাশে আসে, তাই platelet-এর পাশাপাশি HCT trend গুরুত্বপূর্ণ।
- CRP করা যেতে পারে। Persistent significant fever/systemic illness হলে renal function (serum creatinine, urea, electrolytes) এবং LFT—AST, ALT, bilirubin করা যুক্তিযুক্ত।
- Dengue suspicion থাকলে illness day অনুযায়ী test: day 0–7 → Dengue RT-PCR/NAAT + IgM অথবা validated NS1 + IgM; >7 days → repeat/confirmatory IgM বেশি informative।
- Dysuria/frequency/urgency/flank pain থাকলে fresh midstream urine R/E + urine culture & sensitivity BEFORE antibiotic।
- Cough, chest pain, respiratory difficulty বা abnormal auscultation থাকলে proper digital CXR PA ± lateral with radiologist report; SpO₂ অবশ্যই দেখবেন।
- MCHC আবারও >36 g/dL থাকলে repeat CBC + peripheral blood film। প্রয়োজন হলে reticulocyte count, bilirubin, LDH/haptoglobin দিয়ে hemolysis assess করবেন।
9. Treatment plan — এখন কী করবেন?
যদি patient haemodynamically stable, oral intake ভালো এবং warning sign না থাকে, তাহলে supportive management সবচেয়ে উপযুক্ত: rest, adequate oral fluids/ORS এবং fever/pain-এর জন্য paracetamol/acetaminophen। Dengue clinically এখনও completely excluded না হলে aspirin, ibuprofen, diclofenac/other NSAIDs avoid করাই নিরাপদ। CDC-ও suspected dengue-তে acetaminophen ও oral hydration এবং NSAID avoidance recommend করে।
এই রিপোর্টগুলো দেখে empiric antibiotic শুরু করার যথেষ্ট evidence নেই। Source identify করা, clinical examination ও প্রয়োজনমতো culture/CXR-এর পরে antibiotic decision নেওয়া ভালো।
Emergency / admission triggers
Severe abdominal pain, persistent vomiting, mucosal bleeding, hematemesis/melena, marked lethargy/restlessness, hypotension, reduced urine output, breathlessness, SpO₂ কমে যাওয়া, altered consciousness অথবা rising HCT with falling platelet হলে immediate hospital assessment। এগুলো dengue warning/severe illness signs।
10. কাকে Refer করবেন?
First choice: Consultant in Internal Medicine / Medicine Specialist (MD/FCPS Medicine)
কারণ এখনও infection-এর source established নয় এবং CBC + dengue testing + urine + CXR—সবগুলো একত্রে correlate করতে হবে।
যদি prominent cough/respiratory symptoms বা repeat CXR abnormal হয়, এরপর Chest Medicine / Pulmonology referral উপযুক্ত।
Prescription-এর জন্য ready-made Referral Note
Referred to Consultant, Internal Medicine for evaluation of acute febrile/inflammatory illness of undetermined etiology. CBC shows raised ESR (32 mm/1st hr) with relative neutrophilia (80%), normal total WBC and platelet count (212,000/cumm). Dengue NS1 and IgM are negative with isolated IgG positivity, suggesting previous exposure; acute dengue is not confirmed. Urine R/E shows borderline pyuria (pus cells 3–4/HPF) without hematuria; UTI is not established. CXR photograph is technically inadequate for definitive interpretation. Kindly evaluate clinically and consider repeat CBC/HCT/platelet, CRP, dengue confirmatory testing according to illness day, urine C/S if urinary symptoms are present, and formal/repeat chest imaging if respiratory symptoms are present.
Short prescription version:
“Acute febrile illness – etiology under evaluation; relative neutrophilia + raised ESR. Dengue NS1/IgM negative, IgG positive (past exposure). Mild pyuria; UTI not established. Referred to Medicine Specialist for further evaluation.”
Overview / Summary
সব রিপোর্ট মিলিয়ে acute dengue confirmed নয়, UTI confirmed নয় এবং CXR photograph দিয়ে pneumonia confirm করা যাচ্ছে না। প্রধান objective abnormalities হলো ESR 32, relative neutrophilia 80%, isolated high MCHC 37.7 এবং borderline urine pus cells 3–4/HPF। Platelet, total WBC, Hb/HCT মোটামুটি reassuring।
Actionable Plan / Steps
Medicine specialist evaluation → vitals/SpO₂/examination → repeat CBC/HCT/platelet if fever persists → CRP + renal/LFT as clinically indicated → dengue testing according to fever day → urine C/S only if urinary symptoms → proper digital CXR/report if respiratory symptoms → no unnecessary antibiotic; supportive treatment meanwhile.
Reference List
Textbook: Harrison’s Principles of Internal Medicine, 22nd ed. McGraw Hill; sections on dengue/arboviral infection, fever and interpretation of leukocyte abnormalities. Page numbering varies by print/eBook edition.
Guidelines: CDC. Clinical Testing Guidance for Dengue. Updated 2025.
CDC. Clinical Care of Dengue. Updated April 2026.
WHO. Dengue: Guidelines for Diagnosis, Treatment, Prevention and Control.
IDSA. 2025 Guideline Update on Complicated Urinary Tract Infections.
Peer-reviewed journals / DOI: Simmons CP, Farrar JJ, Chau NVV, Wills B. Dengue. N Engl J Med. 2012;366:1423–1432. doi:10.1056/NEJMra1110265.
Sharp TM, et al. Dengue and Zika Virus Diagnostic Testing. MMWR Recomm Rep. 2019;68:1–10. doi:10.15585/mmwr.rr6801a1.
Trautner BW, et al. IDSA 2025 Guideline—Complicated UTI. Clinical Infectious Diseases. 2026;82(Suppl 3):i36–i67. doi:10.1093/cid/ciaf460.
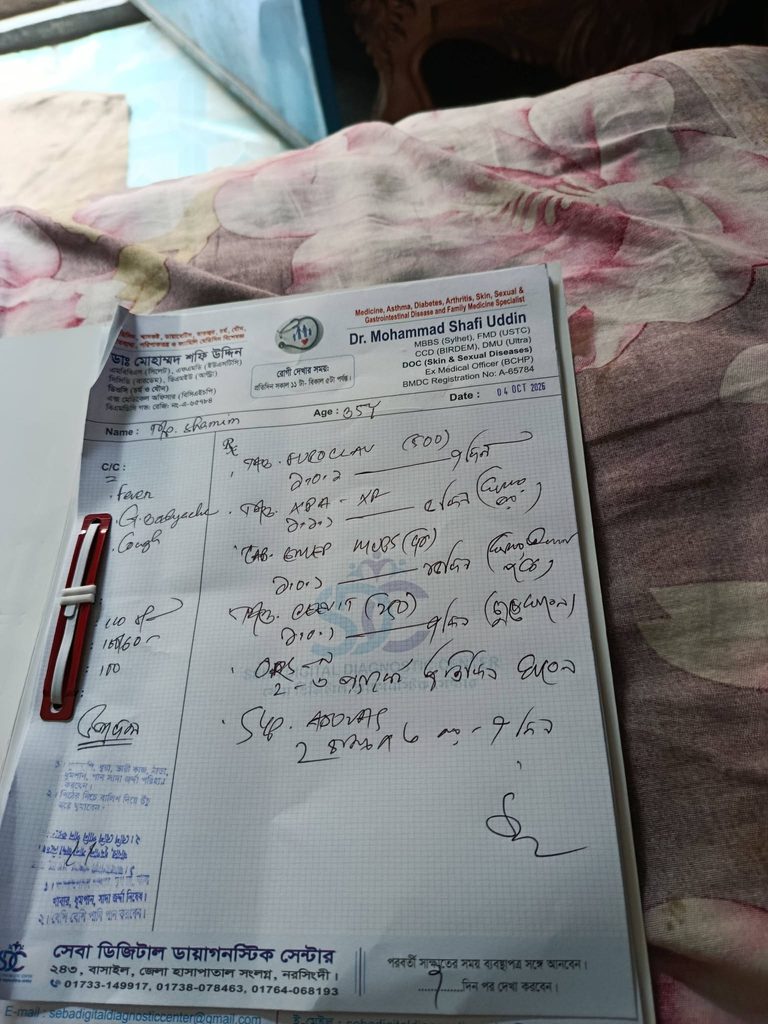
Prescription Analysis:-
আমি prescription-টা zoom করে আগের CBC, Dengue serology, Urine R/E এবং CXR-এর সঙ্গে মিলিয়ে review করেছি। Handwriting-এর যেসব অংশ পুরোপুরি legible নয় সেগুলোকে আমি “probable” হিসেবে দিচ্ছি—ওষুধের নাম বা dose নিয়ে অনুমানকে “exact” বলে দেখানো নিরাপদ হবে না।
1. Prescription-এ Doctor কী লিখেছেন
| Section | Prescription reading | বাংলা clinical meaning | Confidence |
| C/C | Fever | জ্বর | 0.99 |
| G. bodyache | Generalized body ache = সারা শরীর ব্যথা | 0.99 | |
| Cough | কাশি | 0.99 | |
| O/E | Temp ≈100°F | Low-grade fever | 0.85 |
| BP ≈100/60 mmHg | Low-normal blood pressure | 0.88 | |
| Pulse ≈100/min | Upper-normal / mild tachycardic range | 0.82 | |
| Dx | Handwriting appears “ভাইরাল” | সম্ভবত Viral fever / viral illness | 0.78 |
| Follow-up | 7 days | ৭ দিন পর পুনরায় দেখা | 0.96 |
Doctor-এর documented patient history
Doctor স্পষ্টভাবে লিখেছেন:
Fever + generalized body ache + cough.
কিন্তু prescription-এ fever duration, sputum, sore throat, dyspnea, chest pain, vomiting/diarrhea, urinary symptoms, previous disease, drug allergy, RR বা SpO₂ লেখা নেই। এগুলো respiratory febrile illness differentiate করার জন্য clinically গুরুত্বপূর্ণ।
2. Investigation কী কী দিয়েছেন?
এই prescription sheet-এর মধ্যে আলাদা করে নতুন investigation list লেখা দেখা যাচ্ছে না। তবে আপনার আগের একই রোগীর একই দিনের reports-এ referring doctor একই physician এবং নিচের tests করা হয়েছে:
- CBC + ESR
- Dengue NS1
- Dengue IgM
- Dengue IgG
- Urine R/E
- Chest X-ray PA view
আগের results অনুযায়ী significant findings ছিল ESR 32 mm/hr, neutrophils 80%, platelet 212,000/cumm, WBC 8,940/cumm, urine pus cell 3–4/HPF, Dengue IgG positive কিন্তু NS1/IgM negative।
একটি isolated dengue IgG positive result acute dengue confirm করে না; CDC-ও single-specimen IgG-কে acute dengue diagnosis-এর জন্য recommend করে না।
3. Prescription-এর Drug-by-Drug analysis
1) Tab. FUROCLAV 500
Prescription-এ এটি সবচেয়ে পরিষ্কারভাবে পড়া যাচ্ছে। সম্ভবত 1+0+1 × 7 days লেখা।
Generic name: Cefuroxime Axetil 500 mg + Clavulanic Acid 125 mg
Bangladesh Brand: Furoclav 500 mg+125 mg – Renata PLC
MedEx Therapeutic Class: Second generation cephalosporins
Pharmacological class: Cefuroxime = second-generation cephalosporin β-lactam antibiotic; Clavulanic acid = β-lactamase inhibitor.
Price: Unit ৳60; strip ৳420. MedEx-এ 250+62.5 mg tablet এবং suspension-ও available দেখানো আছে।
কোন রোগে ব্যবহার হয়?
MedEx অনুযায়ী sensitive bacterial infection যেমন pharyngitis/tonsillitis, otitis media, bacterial sinusitis, lower respiratory infection including pneumonia, bacterial exacerbation of bronchitis, uncomplicated UTI, skin infection ইত্যাদিতে ব্যবহার হয়।
এই patient-কে কেন দিয়েছেন?
সবচেয়ে সম্ভাব্য কারণ:
Fever + cough দেখে bacterial respiratory infection বা secondary bacterial infection cover করার উদ্দেশ্যে।
Confidence: 0.75.
তবে এখানে গুরুত্বপূর্ণ clinical issue আছে: report alone থেকে bacterial infection proven নয়। WBC স্বাভাবিক, neutrophil percentage বেশি হলেও সেটি bacterial infection-এর definitive evidence নয় এবং CXR photograph থেকে pneumonia establish করা যায়নি।
যদি doctor’s diagnosis সত্যিই শুধু viral fever/viral URTI হয়ে থাকে এবং patient systemically খুব অসুস্থ না হন, routine antibiotic generally recommended নয়। NICE acute cough/URTI guideline-ও uncomplicated acute cough/URTI বা acute bronchitis-এ routine antibiotic না দিতে বলে।
Bangladesh alternatives — same generic
MedEx-এ Fuclav, Famiclav, Fixcef Plus, Furotil Plus, Kefuclav, Furoget CVসহ বিভিন্ন cefuroxime+clavulanate brand আছে।
Important: brand বদলানো বা antibiotic নিজে থেকে শুরু/বন্ধ করা উচিত নয়।
2) Tab. NAPA-XR — probable reading
এখানে handwriting “NAPA-XR” বলে মনে হচ্ছে। Current MedEx/DGDA nomenclature অনুযায়ী সবচেয়ে likely product হচ্ছে Napa Extend 665 mg XR।
Identification confidence: 0.78.
Generic name: Paracetamol / Acetaminophen 665 mg extended-release
Bangladesh Brand: Napa Extend – Beximco Pharmaceuticals Ltd.
MedEx Therapeutic Class: Non-Opioid Analgesics
Pharmacological class: Analgesic + antipyretic; para-aminophenol derivative.
Price: Unit ৳2; current listed strip ৳48.
কেন দিয়েছেন?
এই patient-এর জন্য সরাসরি দুটো indication:
Fever → জ্বর কমানো
Generalized body ache → শরীর ব্যথা কমানো
Paracetamol fever, influenza/common cold, headache, bodyache ও myalgia-তে ব্যবহৃত হয়।
অন্য Bangladesh XR brands
MedEx-এর paracetamol list-এ Momodol XR, Longpara, Napa Extend ইত্যাদি 665 mg extended-release products আছে।
Clinical caution: একই সঙ্গে অন্য paracetamol-containing cold/fever medicine নিলে total dose unintentionally বেশি হয়ে hepatotoxicity হতে পারে।
3) Tab. EMEP MUPS 40
এটি prescription-এ পরিষ্কার।
Generic name: Esomeprazole 40 mg
Brand: Emep MUPS 40 – Aristopharma Ltd.
MedEx Therapeutic Class: Proton Pump Inhibitor
Pharmacological class: Gastric H⁺/K⁺-ATPase proton-pump inhibitor.
Price: Unit ৳17; strip ৳170. 20 mg MUPS-ও available।
কোন রোগে ব্যবহার হয়?
মূলত:
GERD / acid reflux, erosive esophagitis, peptic-acid related symptoms, NSAID-associated ulcer prevention/treatment, Zollinger–Ellison syndrome এবং H. pylori regimen-এর অংশ হিসেবে।
এই patient-কে কেন দিয়েছেন?
সম্ভবত gastric acid suppression / dyspepsia protection, বিশেষ করে acute illness ও multiple oral medicine চলার সময়।
Confidence: 0.85.
এটি fever বা infection cure করে না।
একটি clinically relevant point
Furoclav-এর MedEx monograph-এ বলা আছে, gastric acidity কমানো ওষুধ cefuroxime-এর bioavailability কমাতে পারে। তাই esomeprazole + cefuroxime-containing Furoclav co-prescription-এর necessity prescriber-এর clinical indication অনুযায়ী হওয়া উচিত।
এ কারণে আমি নিজে থেকে Emep বন্ধ করতে বলছি না; শুধু prescription review-এ এটি একটি interaction consideration।
Bangladesh alternatives
Esomeprazole-এর বহু brand আছে—যেমন Maxpro, Nexum, Sergel, Sompraz ইত্যাদি।
4) Tab. CEEVIT 250
Handwriting থেকে Ceevit 250 বেশ পরিষ্কার।
Generic name: Vitamin C / Ascorbic Acid 250 mg
Brand: Ceevit 250 – Square Pharmaceuticals PLC
MedEx Therapeutic Class: Vitamin-C Preparations
Pharmacological class: Water-soluble vitamin; antioxidant/cofactor.
Price: Unit ৳1.90; strip ৳19. Other forms include 500 mg chewable, 1000 mg effervescent and 100 mg/5 mL syrup.
কেন দিয়েছেন?
সম্ভবত supportive vitamin supplementation during febrile respiratory illness।
MedEx অনুযায়ী vitamin C deficiency/scurvy prevention, collagen formation, wound healing এবং iron absorption-এ role আছে।
তবে এটি viral infection-এর specific antiviral treatment নয়।
Bangladesh alternatives হিসেবে Ceeta, Cevalin, Cevion, Chewce, Citrux-C ইত্যাদি পাওয়া যায়।
5) ORS
Prescription-এ সম্ভবত 2–3 packet/day ধরনের instruction লেখা হয়েছে।
Generic: Oral Rehydration Salt, glucose based
MedEx Therapeutic Class: Oral electrolytes preparations
Pharmacological class: Glucose-electrolyte oral replacement solution.
কেন দিয়েছেন?
জ্বর হলে sweating, কম পানি খাওয়া বা poor intake থেকে dehydration prevent/correct করতে।
ORS sodium, potassium, citrate ও glucose দিয়ে fluid/electrolyte replacement করে। MedEx-এ dehydration, vomiting, diarrhea ও inadequate intake-related fluid loss-এর জন্য এটি listed।
Bangladesh-এ ACI ORS, Neosaline, Oral Saline-I, ORS ইত্যাদি available; sachet প্রায় ৳5–6 range-এর অনেক product আছে।
6) Syp. ADOVAS
Brand: Adovas – Square Pharmaceuticals PLC
Generic/Composition: Herbal cough syrup / Vasakarista preparation; contains multiple herbal extracts including Adhatoda vasica, Piper longum, Glycyrrhiza glabra etc.
MedEx Therapeutic Class: Herbal and Nutraceuticals
Pharmacological description: Herbal cough-relieving/expectorant-type preparation; conventional single-drug pharmacological class নেই।
Price: 100 mL ৳70; 200 mL ৳110.
কেন দিয়েছেন?
Prescription-এর cough symptom-এর জন্য।
MedEx এটিকে phlegm liquefaction, throat irritation, hoarseness এবং dry/allergic/smoker cough-এর symptomatic relief-এর জন্য lists করে।
Prescription-এর নিচের dose সম্ভবত “২ চামচ … ৭ দিন”, কিন্তু interval-এর handwriting আমি যথেষ্ট confidently read করতে পারছি না। এই অংশ pharmacy/prescriber দিয়ে confirm করাই ঠিক।
4. Doctor-এর Dx কী?
Left lower part-এর underlined handwriting সবচেয়ে সম্ভবত:
“ভাইরাল” / Viral illness
সম্ভবত doctor-এর intended diagnosis:
Viral Fever / Viral Respiratory Tract Infection
বাংলা: ভাইরাসজনিত জ্বর / ভাইরাসজনিত শ্বাসতন্ত্রের সংক্রমণ।
Handwriting interpretation confidence: 0.78.
Prescription-এ আলাদা করে Pneumonia, Dengue বা UTI লেখা আমি দেখতে পাচ্ছি না।
5. আমার Integrated Working Diagnosis
আগের reports + এখন prescription-এর C/C একসঙ্গে নিলে আমার preferred clinical wording হবে:
Acute febrile respiratory illness, most likely viral upper respiratory tract infection / viral syndrome; bacterial respiratory superinfection not established. Acute dengue not confirmed.
বাংলায়:
জ্বর, সারা শরীর ব্যথা ও কাশি-সহ তীব্র শ্বাসতন্ত্রের সংক্রমণ—সবচেয়ে বেশি সম্ভাবনা ভাইরাসজনিত জ্বর/ভাইরাল শ্বাসনালীর সংক্রমণ। ব্যাকটেরিয়াল সংক্রমণ এখনো প্রমাণিত নয় এবং বর্তমান পরীক্ষায় acute dengue নিশ্চিত হয়নি।
Overall confidence: 0.84.
কেন?
Viral illness-এর পক্ষে: fever + body ache + cough; WBC normal; platelet normal; Dengue NS1/IgM negative; severe bacterial infection-এর strong laboratory evidence নেই।
Bacterial infection পুরো বাদ দিতে পারছি না: neutrophils 80% এবং ESR 32 elevated; তবে এগুলো nonspecific। Proper chest examination, SpO₂, respiratory rate এবং diagnostic-quality CXR/report নেই।
6. Doctor-এর Dx আর আমার Dx কি Similar?
হ্যাঁ—মূল diagnosis substantially similar।
Similarity confidence: ~0.88.
Doctor সম্ভবত “Viral” লিখেছেন। আমার diagnosis-ও most likely viral febrile respiratory infection।
তবে আমার wording একটু বেশি cautious:
Doctor: Viral illness → তুলনামূলক definitive।
My assessment: Viral illness most likely, কিন্তু bacterial respiratory infection এখনো differential-এ থাকবে যতক্ষণ chest examination/CXR adequately exclude না করে।
সবচেয়ে বড় inconsistency
যদি diagnosis সত্যিই শুধুমাত্র viral fever/viral URTI হয়, তাহলে Furoclav antibiotic routine requirement নয়। NICE guideline uncomplicated acute cough/URTI/acute bronchitis-এ antibiotics routinely না দিতে বলে—unless patient systemically very unwell বা complication risk বেশি।
Doctor face-to-face examination-এ bacterial component suspect করে থাকতে পারেন—যেমন chest signs, purulent sputum বা other clinical finding—কিন্তু prescription-এ সেটা documented নেই। তাই antibiotic-কে “wrong” বলা সম্ভব নয়, তবে written evidence থেকে indication fully demonstrated নয়।
7. এখন Clinical Action Plan
যদি fever/cough এখনও থাকে, আমি SpO₂, respiratory rate, temperature, pulse/BP এবং full chest auscultation আবার document করতাম। Persistent/worsening fever হলে repeat CBC with differential + CRP, এবং respiratory symptoms significant হলে proper digital CXR PA with radiologist report করা উচিত। Productive/severe cough থাকলে selected cases-এ sputum evaluation/culture; urinary symptoms থাকলে urine culture।
Dengue suspicion clinically থাকলে illness day অনুযায়ী testing করতে হবে; isolated IgG positivity-কে acute dengue ধরা যাবে না।
যদি breathlessness, SpO₂ <94%, hypotension, confusion, persistent vomiting, bleeding, severe chest pain বা marked deterioration হয়, তখন outpatient review না করে urgent hospital assessment প্রয়োজন।
8. এই ধরনের রোগে Evidence-based commonly used medicines
Probable uncomplicated viral febrile RTI হলে মূল treatment: paracetamol for fever/bodyache + adequate oral fluid/ORS + symptom-directed cough management। Routine antibiotic প্রয়োজন হয় না।
যদি clinical/imaging evidence-এ bacterial pneumonia/respiratory infection establish হয়, antibiotic selection patient age, comorbidity, allergy, severity এবং local resistance অনুযায়ী করা হয়। ATS/IDSA guidance-এ selected outpatient CAP-এ amoxicillin, doxycycline, অথবা appropriate circumstances-এ macrolide/combination regimens ব্যবহারের কথা আছে। Updated ATS guidance-ও bacterial coinfection likelihood অনুযায়ী antibiotic individualize করার ওপর জোর দেয়।
Furoclav নিজে থেকে replace/add করা উচিত নয়।
Overview / Summary
Prescription-এ সবচেয়ে সম্ভবত diagnosis “Viral”। C/C হলো fever + generalized bodyache + cough। Drugs হলো Furoclav 500, probable Napa-XR, Emep MUPS 40, Ceevit 250, ORS এবং Adovas syrup। Doctor-এর diagnosis ও আমার integrated diagnosis largely similar, কিন্তু bacterial respiratory infection documentedভাবে proven নয় এবং acute dengue-ও confirmed নয়।
Actionable Plan / Steps
বর্তমানে সবচেয়ে গুরুত্বপূর্ণ missing clinical data হলো SpO₂, RR এবং chest findings। এগুলো check করুন; symptoms persist/worsen করলে CBC/CRP ± proper CXR করুন। Antibiotic course বা dose নিজে পরিবর্তন না করে prescriber-এর সঙ্গে bacterial indication verify করুন—বিশেষ করে যেহেতু written Dx viral মনে হচ্ছে।
References
Textbooks: Harrison’s Principles of Internal Medicine, 22nd ed.—chapters on acute respiratory infections, pneumonia and dengue; Davidson’s Principles and Practice of Medicine, 25th ed.—respiratory infections and pyrexia.
Guidelines: NICE NG120, Cough (acute): antimicrobial prescribing. CDC, Clinical Testing Guidance for Dengue. ATS Clinical Practice Guideline, Diagnosis and Management of Community-acquired Pneumonia.
Peer-reviewed DOI: Jones BE, et al. Diagnosis and Management of Community-acquired Pneumonia. Am J Respir Crit Care Med. 2026;212:24–44. doi:10.1164/rccm.202507-1692ST.
Metlay JP, et al. Diagnosis and Treatment of Adults with Community-acquired Pneumonia. Am J Respir Crit Care Med. 2019;200:e45–e67. doi:10.1164/rccm.201908-1581ST.
Md.Rafiqul Islam Lipu.