Image attached:-
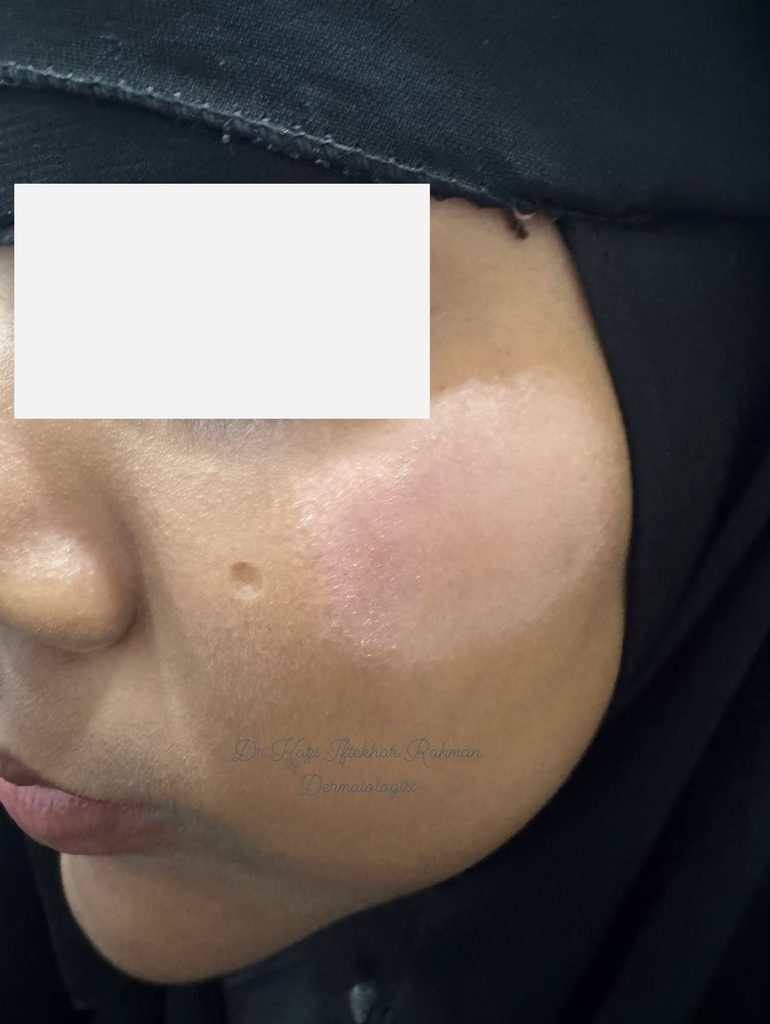
This information has been collected by ডা. কাজী ইফতিখার রহমান
চর্ম ও যৌনরোগ বিশেষজ্ঞ
লেজার ও কসমেটিক ডার্মাটোসার্জন
মুখে সাদা দাগ দেখলেই কি শ্বেতী?
একদমই না!
অনেকেই মুখে একটু সাদা/ফ্যাকাশে দাগ দেখলেই ভয় পেয়ে বলেন—
“শ্বেতী হয়ে গেছে!”
কিন্তু বাস্তবতা হলো, ত্বকের রঙ কমে যাওয়ার অনেক কারণ থাকতে পারে।
Vitiligo (শ্বেতী)
Pityriasis alba
Post-inflammatory hypopigmentation
Tinea versicolor
Nevus depigmentosus
আরও কিছু ত্বকের রোগেও এমন সাদা বা ফ্যাকাশে দাগ দেখা যেতে পারে।
তাই শুধু ছবি দেখে বা দাগের রঙ দেখে নিজে নিজে শ্বেতী ধরে নেওয়া ঠিক নয়।
কী দেখে পার্থক্য করা হয়?
দাগটি পুরোপুরি সাদা নাকি শুধু ফ্যাকাশে,
দাগের সীমানা কেমন,
কোনো স্কেলিং আছে কি না,
দাগটি কতদিন ধরে আছে ও বাড়ছে কি না,
শরীরের অন্য কোথাও এমন দাগ আছে কি না—
এসব তথ্যের পাশাপাশি প্রয়োজন হলে Wood’s lamp examination-এর মতো পরীক্ষা রোগ নির্ণয়ে সাহায্য করতে পারে।
সবচেয়ে গুরুত্বপূর্ণ কথা
সাদা দাগ মানেই শ্বেতী নয়।
আবার শ্বেতী হলেও ভয় পাওয়ার কিছু নেই।
ভুল রোগ ধরে নিয়ে নিজে থেকে স্টেরয়েড/ফর্সা করার ক্রিম/অ্যান্টিফাঙ্গাল ব্যবহার না করে সঠিক রোগ নির্ণয় করান।
ত্বকের রঙের সামান্য পরিবর্তন—সঠিক রোগ নির্ণয়ই পারে আসল কারণটা খুঁজে বের করতে।
This Information has been collected by Chat Gpt:-
ছবিটি দেখে সবচেয়ে সম্ভাব্য diagnosis: Pityriasis alba / post-inflammatory hypopigmentation।
Confidence: ~0.75
ছবিতে cheek-এর patchটি পুরো chalk-white depigmented নয়, border-ও খুব sharply demarcated নয়; বরং একটি ill-defined hypopigmented patch, সঙ্গে সামান্য erythematous/pinkish background আছে বলে মনে হচ্ছে। এই morphology pityriasis alba-র সঙ্গে বেশি মেলে। Pityriasis alba সাধারণত মুখে, বিশেষ করে cheek-এ, poorly defined hypopigmented patch হিসেবে দেখা যায় এবং কখনও fine scaling বা preceding mild erythema থাকতে পারে।
Differential diagnosis
| Diagnosis | এই ছবির সঙ্গে মিল | আমার assessment |
| Pityriasis alba | Ill-defined, incomplete hypopigmentation, cheek involvement | Most likely — 0.75 |
| Post-inflammatory hypopigmentation | আগে eczema/irritation/rash থাকলে এমন হতে পারে | Possible — 0.60 |
| Tinea versicolor | Fine scale থাকলে সম্ভব, তবে সাধারণত trunk/neck বেশি affected | Less likely — 0.35 |
| Vitiligo | সাধারণত complete/milky-white depigmentation ও clearer margin | বর্তমান ছবিতে less likely — 0.25 |
| Nevus depigmentosus | সাধারণত longstanding/stable, often early-life onset | History ছাড়া low probability |
Tinea versicolor-এ সাধারণত fine scale থাকে এবং KOH examination-এ Malassezia-এর yeast/hyphae দেখা যেতে পারে।
কেন Vitiligo আমার প্রথম diagnosis নয়?
Typical vitiligo-তে pigment loss সাধারণত complete depigmentation হয় এবং Wood’s lamp-এর নিচে lesion bright/striking white ও sharply delineated হয়ে ওঠে। এই ছবিতে visible light-এ সেই classic appearance পরিষ্কার নয়।
তবে শুধু একটি photograph থেকে vitiligo 100% exclude করা যায় না, বিশেষ করে early/incomplete vitiligo হলে।
Diagnosis confirm করার সবচেয়ে practical way
1. Wood’s lamp examination — first choice
- Bright blue/white, sharply enhanced → vitiligo strongly supported
- শুধু mild accentuation / no complete fluorescence → pityriasis alba বা অন্য hypopigmentation বেশি likely.
2. যদি fine scaling থাকে → KOH scraping
- Positive yeast + short hyphae → tinea versicolor.
3. History খুব গুরুত্বপূর্ণ
আগে eczema/itching/red rash, নতুন cosmetic/cream, rubbing, acne/inflammation হয়েছিল কিনা জানতে হবে।
Overview / Summary
Photo-based working diagnosis: Pityriasis alba, সম্ভবত inflammatory/post-inflammatory hypopigmentation spectrum।
Vitiligo বর্তমানে আমার first diagnosis নয়।
Overall confidence: 0.75 — কারণ clinical examination, scale testing এবং Wood’s lamp করা হয়নি।
Actionable Plan
এই patient সামনে থাকলে আমি প্রথমে Wood’s lamp করতাম। Fine scale থাকলে KOH scraping করতাম। Wood’s lamp-এ vitiligo pattern না থাকলে এবং lesion mildly dry/ill-defined হলে pityriasis alba হিসেবে clinical management বিবেচনা করা যায়। Diagnosis নিশ্চিত হওয়ার আগে potent steroid, antifungal বা “whitening” combination cream empirically দেওয়া ঠিক হবে না।
Lets know the topics detailed :-
Working Clinical Assessment
আপনার দেওয়া ছবিতে cheek-এর lesionটি সম্পূর্ণ chalk-white depigmented নয়, margin তুলনামূলকভাবে ill-defined এবং হালকা pink/hypopigmented appearance আছে। তাই Pityriasis alba আমার প্রধান working diagnosis। তবে photograph থেকে scale, sensation ও Wood’s lamp response দেখা যায় না—তাই এটিকে definitive diagnosis বলা যাবে না।
Working diagnosis: Facial Pityriasis alba — confidence 0.75.
নিকটতম differential হলো post-inflammatory hypopigmentation। Vitiligo ও tinea versicolor বর্তমানে কম সম্ভাব্য, তবে examination ছাড়া বাদ দেওয়া যাবে না। Pityriasis alba সাধারণত cheek-এ poorly defined, mildly scaly hypopigmented patch হিসেবে দেখা যায়।
1. Pityriasis alba — Definition
Pityriasis alba হলো একটি benign, low-grade eczematous/hypopigmentary skin disorder, যেখানে ত্বকে প্রথমে সামান্য erythema ও fine scaling দেখা দিতে পারে এবং পরে সেই অংশটি আশপাশের ত্বকের তুলনায় ফ্যাকাশে বা hypopigmented হয়ে যায়।
এটি Vitiligo নয়, কারণ সাধারণত melanocyte সম্পূর্ণ নষ্ট হয় না এবং lesion সম্পূর্ণ depigmented/chalk-white হয় না। Histologic studies-এ lesional skin-এ melanin কম থাকলেও melanocyte number উল্লেখযোগ্যভাবে কমে যাওয়ার প্রমাণ পাওয়া যায়নি।
Confidence: 0.95
2. কারণ ও Pathophysiology
Pityriasis alba-এর একটি নির্দিষ্ট প্রমাণিত কারণ নেই। বর্তমানে এটিকে atopic/eczema spectrum-এর একটি mild inflammatory disorder হিসেবে দেখা হয়।
প্রধান association/triggerগুলো হলো:
- Atopic dermatitis / atopic tendency: eczema, asthma বা allergic tendency থাকা রোগীদের মধ্যে বেশি দেখা যায়।
- Dry skin বা xerosis: skin-barrier দুর্বল হলে transepidermal water loss বাড়ে এবং low-grade inflammation তৈরি হতে পারে।
- Mild inflammation: inflammation-এর পরে melanogenesis বা melanin transfer সাময়িকভাবে কমে গিয়ে hypopigmentation হয়।
- Sun exposure: সূর্য সাধারণত মূল cause নয়; surrounding normal skin tan হয়ে গেলে pale patchটি অনেক বেশি স্পষ্ট হয়ে ওঠে।
- Harsh soap, frequent washing, rubbing, scrubbing: skin barrier damage করে lesion trigger বা worsen করতে পারে।
- Cold/dry weather: dryness ও fine scale বেশি দৃশ্যমান হতে পারে।
- কিছু literature-এ microorganisms, trace elements বা nutritional factors নিয়ে আলোচনা আছে, কিন্তু কোনো নির্দিষ্ট vitamin/mineral deficiency Pityriasis alba-এর established cause নয়। তাই calcium/vitamin দিলেই রোগ সেরে যাবে—এমন evidence নেই।
Confidence: 0.88
3. Symptoms / Clinical Features
- সবচেয়ে বেশি হয় cheek ও chin-এ; neck, shoulder ও upper arm-এও হতে পারে।
- সাধারণত round, oval অথবা irregular pale patch।
- Size প্রায় 0.5–5 cm হতে পারে।
- Border সাধারণত ill-defined/blurred, vitiligo-এর মতো অত্যন্ত sharp নয়।
- Lesion সম্পূর্ণ সাদা নয়; normal skin-এর তুলনায় হালকা।
- প্রথম stage-এ হালকা pink/red এবং সামান্য scaly হতে পারে।
- পরে hypopigmented + fine scale হয়।
- শেষে scale চলে গিয়ে শুধু pale macule থাকে এবং ধীরে ধীরে normal pigmentation ফিরে আসে।
- Itching সাধারণত নেই বা খুব সামান্য।
- Hair সাধারণত normal colour থাকে।
- Summer-এ surrounding skin dark হওয়ায় lesion বেশি চোখে পড়ে; winter-এ dryness/scale বেশি হতে পারে।
রোগটি benign এবং pigmentation ফিরে আসতে কয়েক মাস লাগতে পারে; average clearance প্রায় এক বছর, যদিও কয়েক মাস থেকে 2–3 বছরও লাগতে পারে।
Confidence: 0.95
4. Clinical Diagnosis ও Investigation
A. Clinical diagnosis
Pityriasis alba মূলত clinical diagnosis। Examine করতে হবে:
- lesion সম্পূর্ণ depigmented নাকি hypopigmented;
- border sharp নাকি ill-defined;
- fine scale আছে কি না;
- erythema আছে কি না;
- itch/dryness আছে কি না;
- previous eczema/rash ছিল কি না;
- নতুন cosmetic/soap/steroid ব্যবহার করেছে কি না;
- lesion বাড়ছে কি না;
- শরীরের অন্য জায়গায় lesion আছে কি না;
- lesion-এর touch/pain/temperature sensation normal কি না।
শেষ pointটি গুরুত্বপূর্ণ: hypopigmented patch-এ definite sensory loss থাকলে leprosy/Hansen disease differential হিসেবে দেখতে হবে; WHO এটিকে leprosy-এর cardinal signs-এর একটি হিসেবে উল্লেখ করে।
B. Wood’s lamp examination
Pityriasis alba-তে সাধারণত:
Wood’s lamp → significant enhancement হয় না এবং fluorescence থাকে না।
এর বিপরীতে classic vitiligo-তে depigmentation Wood’s lamp-এ অনেক বেশি sharply accentuated হয়।
এই ছবির ক্ষেত্রে আমি Wood’s lamp-কে সবচেয়ে useful next examination বলব।
C. KOH examination / Skin scraping
Fine scaling থাকলে lesion-এর edge থেকে scraping নিয়ে 10–20% KOH microscopy করা যায়।
Pityriasis alba হলে fungal elements negative হবে। Positive fungal hyphae/yeast পাওয়া গেলে tinea versicolor diagnosis-এর দিকে যেতে হবে।
D. Dermoscopy
দেখা যেতে পারে:
- poorly defined pale area;
- faint pigment network;
- superficial white scale;
- white structureless area;
- normal hair pigmentation।
E. Skin biopsy
Routine নয়। Diagnostic uncertainty থাকলে করা যায়। Mild spongiotic dermatitis এবং epidermal melanin reduction পাওয়া যেতে পারে।
F. Routine blood test
Typical Pityriasis alba-তে সাধারণত CBC, thyroid, vitamin D, calcium, ANA ইত্যাদি routinely প্রয়োজন নেই।
Diagnostic confidence after appropriate Wood’s lamp + clinical examination: >0.90, যদি findings typical হয়।
5. গুরুত্বপূর্ণ Differential Diagnosis
Vitiligo: chalk/milky white, বেশি complete depigmentation, সাধারণত clearer margin; Wood’s lamp-এ marked enhancement।
Tinea versicolor: fine scale বেশি; KOH positive হলে diagnosis confirmed।
Post-inflammatory hypopigmentation: আগে eczema, acne, dermatitis, burn বা অন্য inflammatory lesion থাকার history থাকে।
Nevus depigmentosus: সাধারণত childhood থেকেই present এবং তুলনামূলক stable।
Leprosy: hypopigmented/reddish patch + definite sensory loss অথবা thickened peripheral nerve থাকলে অবশ্যই exclude করতে হবে।
6. Complications — রোগীকে কীভাবে বোঝাবেন
Pityriasis alba সাধারণত dangerous disease নয় এবং systemic complication করে না।
তবে:
- pigment normal হতে অনেক সময় লাগতে পারে;
- lesion recur করতে পারে;
- darker skin-এ cosmetic contrast বেশি হওয়ায় anxiety হতে পারে;
- ভুল করে vitiligo মনে করে unnecessary treatment নেওয়া হতে পারে;
- prolonged potent steroid ব্যবহার করলে steroid-related skin atrophy, telangiectasia, acneiform eruption ইত্যাদি হতে পারে;
- fungal lesion ভুল করে PA ধরে steroid দিলে tinea mask/worsen হতে পারে।
Pityriasis alba সাধারণত scar বা permanent depigmentation তৈরি করে না, এবং pigmentation শেষ পর্যন্ত normal হওয়ার সম্ভাবনা খুব বেশি।
Confidence: 0.94
7. Treatment & Management
সব medicine একসঙ্গে ব্যবহার করতে হবে না। Practical hierarchy হলো:
Mild/asymptomatic disease → moisturizer + sun protection।
Redness/itch/inflammation থাকলে → short-course mild hydrocortisone।
Persistent/recurrent facial lesion বা steroid avoidance প্রয়োজন হলে → tacrolimus OR pimecrolimus-এর মতো steroid-sparing agent বিবেচনা করা যায়।
Calcineurin inhibitors-এর Pityriasis alba use মূলত off-label, যদিও clinical studies ও dermatology references-এ efficacy reported হয়েছে।
1. Generic name: Light Liquid Paraffin + White Soft Paraffin + Glycerine
Strength: 10% + 5% + 10%
MedEx Therapeutic Class: Emollients & combined preparations
Pharmacological class: Emollient + occlusive moisturiser + humectant.
Purpose of use: Pityriasis alba-তে dryness, fine scaling ও impaired skin barrier কমানোর জন্য। Paraffin water loss কমায় এবং glycerine skin hydration বাড়ায়।
Dose: affected area-তে thin layer সাধারণত দিনে 2–4 বার, বিশেষ করে washing/bathing-এর পরে এবং রাতে।
Duration: অন্তত কয়েক সপ্তাহ; dryness থাকলে দীর্ঘমেয়াদেও ব্যবহার করা যায়।
Side effects: সাধারণত খুব safe। Rarely irritation/contact reaction বা occlusive folliculitis হতে পারে।
Interaction: clinically significant systemic interaction নেই। অন্য topical medicine-এর সঙ্গে একই সময়ে mix না করে 20–30 মিনিট gap রাখা ভালো, যাতে active drug dilute না হয়।
Bangladesh MedEx-listed brands — exact same generic:
Emolent Plus 10%+5%+10% — Square — 50 gm ৳200; Softderm 10%+5%+10% — General — 50 gm ৳200; XeroSoft Max 10%+5%+10% — UniMed UniHealth — 50 gm ৳200।
এগুলো topical tube—তাই unit tablet price/strip price applicable নয়।
Confidence: 0.94
2. Generic name: Hydrocortisone Acetate
Strength: 1% ≈ 10 mg/g
MedEx Therapeutic Class: Other Topical corticosteroids
Pharmacological class: Low-potency topical corticosteroid.
Purpose of use: Pityriasis alba-তে রঙ সাদা বলে steroid দেওয়া হয় না। Redness, inflammation, itching বা active eczematous scaling থাকলে inflammation suppress করার জন্য ব্যবহার করা হয়। DermNet mild topical 0.5–1% hydrocortisone সমর্থন করে।
Pityriasis alba facial regimen: খুব পাতলা layer দিনে 1 বার, প্রায় 5–7 দিন; প্রয়োজন হলে চিকিৎসকের assessment অনুযায়ী সর্বোচ্চ 1–2 সপ্তাহ। MedEx-এর general dermatologic label-এ দিনে 2–3 বার বলা আছে, তবে face-এ prolonged corticosteroid undesirable বলে MedEx নিজেই সতর্ক করেছে।
Side effects: short course-এ সাধারণত mild burning/irritation ছাড়া significant problem কম। Prolonged বা inappropriate facial use-এ skin thinning/atrophy, telangiectasia, acneiform eruption, colour change এবং শিশুদের large-area/long-term use-এ adrenal suppression-এর risk বাড়তে পারে।
Contraindication/caution: untreated bacterial, viral বা fungal infection-এর উপর ব্যবহার করা উচিত নয়। তাই tinea সন্দেহ হলে আগে KOH করুন।
Interaction: MedEx hydrocortisone topical page কোনো specific systemic drug interaction উল্লেখ করে না। Emollient-এর সঙ্গে 20–30 মিনিট gap রাখুন।
Bangladesh MedEx brands:
Cortider 1% — Eskayef, 10 gm ৳40; Cortimet 1% — Medimet, 10 gm ৳28; Hydrocort 1% — Alco, 10 gm ৳28; Intasone 1% — Incepta, 10 gm ৳30; Topicort 1% — Square, 20 gm ৳70; Zocort 1% — ACI, 15 gm ৳70।
একটি গুরুত্বপূর্ণ availability note: MedEx generic list-এ Hydrocort আছে, কিন্তু তার individual brand page বর্তমানে এটিকে “unavailable” দেখাচ্ছে; local availability verify করতে হবে।
Confidence: 0.91
3. Generic name: Tacrolimus Monohydrate — Topical
Strength:
0.03% = 0.3 mg/g
0.1% = 1 mg/g
MedEx Therapeutic Class: Drugs affecting the immune response
Pharmacological class: Topical calcineurin inhibitor / immunomodulator.
Purpose of use: face-এর persistent/recurrent Pityriasis alba-তে steroid-sparing anti-inflammatory treatment হিসেবে ব্যবহার করা যায় এবং repigmentation দ্রুত করতে পারে। Pityriasis alba-র জন্য এটি off-label; একটি randomized study-তে 0.1% twice daily for 9 weeks moisturizer/sunscreen-এর চেয়ে বেশি improvement দেখিয়েছে।
Dose: thin film affected area-তে দিনে 2 বার।
Age/strength per MedEx: 2 বছর বা তার বেশি বয়সে 0.03% ব্যবহার করা যায়; 0.1% 16 বছর বা তার বেশি বয়সে ব্যবহারের কথা MedEx উল্লেখ করে।
Pityriasis alba duration: সাধারণত 4–6 সপ্তাহে review; response থাকলে dermatology supervision-এ প্রায় 6–9 সপ্তাহ পর্যন্ত বিবেচনা করা যায়। Trial evidence 9 সপ্তাহের।
Side effects: application-site burning, itching, erythema; কম ক্ষেত্রে skin infection, flu-like symptoms, allergic reaction বা headache। শুরুতে burning কয়েকদিন থাকতে পারে।
Interaction: systemic absorption সাধারণত কম। তবে widespread/erythrodermic skin disease-এ erythromycin, itraconazole, ketoconazole, fluconazole, calcium-channel blockers এবং cimetidine-এর মতো CYP3A4 inhibitors-এর সঙ্গে caution বলা হয়েছে। Occlusive dressing ব্যবহার করা উচিত নয়।
Bangladesh MedEx-listed brands:
Dermus 0.03% 10 gm ৳150; Prolimus 0.03% 30 gm ৳450, 0.1% 30 gm ৳1,000; Remus 0.03% 10 gm ৳150, 0.1% 10 gm ৳360; Rolimus 0.03% 10 gm ৳150, 0.1% 10 gm ৳360; Tacroderm 0.1% 5 gm ৳200; Tacrol 0.03% 30 gm ৳450, 0.1% 30 gm ৳1,000; Tacrolim 0.03% 5 gm ৳80, 0.1% 5 gm ৳200; Vitilimus 0.03% 30 gm ৳450, 0.1% 30 gm ৳1,000।
Confidence: 0.88 — কারণ PA-এর evidence আছে, তবে use off-label এবং trials তুলনামূলক ছোট।
4. Generic name: Pimecrolimus
Strength: 1% = 10 mg/g
MedEx Therapeutic Class: Drugs affecting the immune response
Pharmacological class: Topical calcineurin inhibitor.
Purpose of use: facial Pityriasis alba-তে steroid-sparing option; বিশেষ করে recurrent inflammatory lesion বা facial steroid adverse-effect concern থাকলে। PA-এর জন্য off-label। একটি 12-week clinical study-তে 1% twice daily ব্যবহারে pigmentation ও scaling improvement হয়েছে।
Dose: thin layer দিনে 2 বার।
Age: MedEx অনুযায়ী 2 বছরের নিচে ব্যবহার indicated নয়।
Duration: 4–6 সপ্তাহে response assess করা উচিত। PA study-তে 12 সপ্তাহ ব্যবহার হয়েছে; longer course specialist supervision ছাড়া চালানো উচিত নয়।
Side effects: application-site burning/warmth; uncommon headache, cold/stuffy nose, sore throat, cough, fever বা viral infection reported।
Interaction: systemic interaction expected কম; MedEx erythromycin, itraconazole, ketoconazole, fluconazole, calcium-channel blockers ও cimetidine-এর সঙ্গে caution উল্লেখ করে।
Bangladesh brand: Pmec 1% cream — Navana Pharmaceuticals — 10 gm tube ৳1,000. MedEx-এ এই exact generic-এর বর্তমানে একটি brand listed।
Confidence: 0.82 — evidence positive, তবে study sample ছোট এবং PA indication off-label।
5. Sun protection: Zinc oxide + Octinoxate + Enzacamene + Avobenzone
MedEx Therapeutic Class: Sunblock Preparation
Pharmacological class: Physical + chemical UV-filter combination.
Purpose: Pityriasis alba cure করার জন্য নয়; surrounding skin tanning কমিয়ে lesion-এর colour contrast কমানো এবং UV protection দেওয়া। Sunscreen PA-এর prominence কমাতে সাহায্য করে।
MedEx preparation: SunMask-এর SPF 60, UVA PA+++ উল্লেখ করা হয়েছে।
Dose: বাইরে যাওয়ার প্রায় 30 মিনিট আগে exposed skin-এ apply; prolonged sun exposure, sweating বা swimming থাকলে প্রায় প্রতি 2 ঘণ্টা পর reapply।
Side effects: sensitive skin-এ erythema, burning বা rash হতে পারে।
Interaction: other topical drugs-এর সঙ্গে interaction সম্পর্কে definitive data নেই। Morning regimen-এ active topical absorb হওয়ার পরে sunscreen শেষ layer হিসেবে ব্যবহার করা practical।
Bangladesh brand: SunMask Cream — Square Pharmaceuticals — 60 gm ৳250.
MedEx এই specific preparation-এর paediatric safety established নয় বলেছে, তাই শিশু হলে age-appropriate sunscreen নির্বাচন করা উচিত।
Confidence: 0.94
গুরুত্বপূর্ণ Drug Combination Rule
Tacrolimus + Pimecrolimus একসঙ্গে লাগানোর প্রয়োজন নেই—একটি নির্বাচন করতে হবে।
Hydrocortisone-ও routineভাবে calcineurin inhibitor-এর সঙ্গে একই lesion-এ একই সময়ে চালানোর প্রয়োজন নেই। Active inflammatory short flare হলে hydrocortisone short course, অথবা facial steroid-sparing strategy হিসেবে calcineurin inhibitor—clinical context অনুযায়ী নির্বাচন করা ভালো।
আর Pityriasis alba বলে antifungal লাগানোর indication নেই। Scaling + positive KOH/appropriate clinical diagnosis হলে তবেই antifungal treatment যুক্ত হবে।
Prevention
- Mild, fragrance-free cleanser ব্যবহার করুন; harsh soap, scrub, bleaching product ও aggressive facial treatment এড়িয়ে চলুন।
- মুখ ধোয়ার পর regular moisturizer ব্যবহার করুন।
- Daily broad-spectrum SPF ≥30 sunscreen ব্যবহার করুন।
- Excessive rubbing, hot-water washing এবং repeated exfoliation কমান।
- Associated eczema থাকলে early control করুন।
- “সাদা দাগ” দেখে potent steroid, steroid-antifungal-combination বা fairness cream নিজে থেকে ব্যবহার করবেন না।
- নতুন lesion দ্রুত বাড়লে, completely white হলে, hair white হলে অথবা sensation কমে গেলে diagnosis পুনর্মূল্যায়ন করুন।
Overview / Summary
আপনার ছবির ভিত্তিতে Facial Pityriasis alba সবচেয়ে সম্ভাব্য working diagnosis — confidence ~0.75। Morphology PA-এর সঙ্গে মানানসই, কিন্তু Wood’s lamp + clinical examination করলে confidence উল্লেখযোগ্যভাবে বাড়বে।
Pityriasis alba একটি benign, non-contagious, usually self-resolving hypopigmentary eczema-spectrum disorder। বেশিরভাগ ক্ষেত্রে moisturizer + sunscreenই যথেষ্ট। Redness/itch থাকলে short-course low-potency hydrocortisone এবং persistent facial disease-এ selected cases-এ tacrolimus বা pimecrolimus বিবেচনা করা যায়।
Actionable Plan / Steps
এই ছবির patient আমার সামনে থাকলে প্রথমে lesion-এর scale + sensation + border পরীক্ষা, তারপর Wood’s lamp করতাম। Fine scale থাকলে KOH scraping করতাম। Wood’s lamp-এ PA pattern এবং KOH negative হলে first-line হিসেবে regular emollient + sun protection শুরু করতাম। Lesion active pink/itchy/scaly হলে প্রয়োজন অনুসারে Hydrocortisone 1% short course; persistent/recurrent হলে age ও clinical situation অনুযায়ী Tacrolimus অথবা Pimecrolimus বিবেচনা করতাম। 4–6 সপ্তাহে response না থাকলে diagnosis আবার review করতাম।
MedEx brand/price তথ্য 2 October 2026-এ যাচাই করা হয়েছে; pharmacy price/availability পরিবর্তিত হতে পারে।
Reference List
Textbook: James WD, Elston DM, Treat JR, Rosenbach MA. Andrews’ Diseases of the Skin: Clinical Dermatology. 14th ed. Elsevier; 2024/2025. বর্তমান 14th edition-এ eczema/atopic and diagnostic dermatology sections relevant।
Textbook/clinical reference: Griffiths C, Barker J, Bleiker T, Chalmers R, Creamer D, eds. Rook’s Textbook of Dermatology. Pityriasis alba discussed under eczematous disorders; DermNet cites the relevant textbook section.
Clinical reference: DermNet NZ. Pityriasis alba (dry white patches)—diagnosis, Wood’s lamp, mycology, management and prognosis.
Guideline status: Pityriasis alba-র জন্য আলাদা WHO/CDC/NICE disease-specific pharmacotherapy guideline নেই; management মূলত dermatology textbooks, clinical references এবং published trials/reviews-এর ওপর ভিত্তি করে। Leprosy differential-এর sensory-loss criterion WHO guidance অনুসারে।
Peer-reviewed DOI references: Miazek N, et al. Pityriasis Alba—Common Disease, Enigmatic Entity: Up-to-Date Review of the Literature. Pediatr Dermatol. 2015;32:786–791. doi:10.1111/pde.12683.
In SI, et al. Clinical and histopathological characteristics of pityriasis alba. Clin Exp Dermatol. 2009;34:591–597. doi:10.1111/j.1365-2230.2008.03038.x.
Rigopoulos D, et al. Tacrolimus ointment 0.1% in pityriasis alba: an open-label, randomized, placebo-controlled study. Br J Dermatol. 2006;155:152–155. doi:10.1111/j.1365-2133.2006.07181.x.
Fujita WH, et al. An exploratory study to evaluate the efficacy of pimecrolimus cream 1% for the treatment of pityriasis alba. Int J Dermatol. 2007;46:700–705. doi:10.1111/j.1365-4632.2007.03145.x
Md.Rafiqul Islam Lipu.