Image attached:-


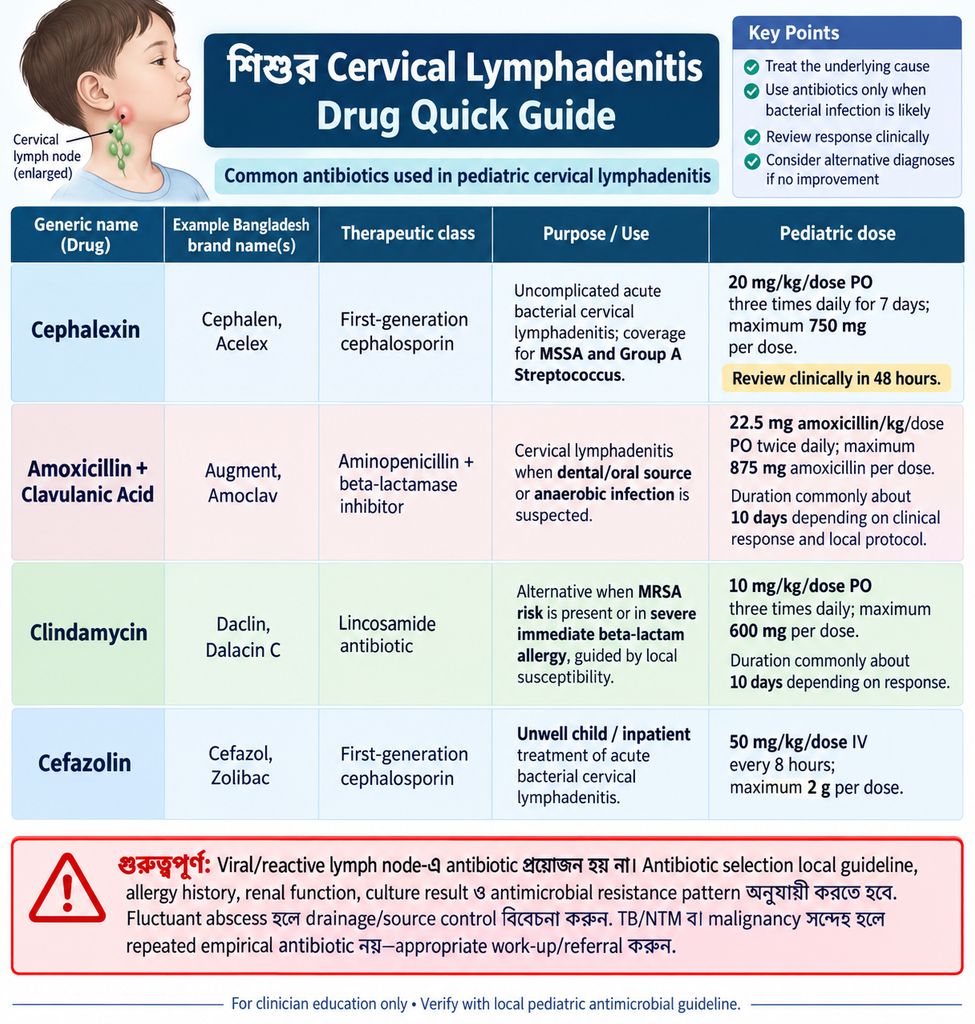
This info collected by ডা. মানিক মজুমদার
MBBS, BCS (Health), MD (Pediatrics)
শিশুর লিম্ফ নোড ফুলে গেলেই কি টিউমার?
“ডাক্তার সাহেব, আমার বাচ্চার গলার পাশে একটা গুটি হয়েছে—এটা কি ক্যান্সার?”
এটি উদ্বিগ্ন বাবা-মায়ের খুব পরিচিত একটি প্রশ্ন।
তবে প্রথমেই মনে রাখা জরুরি—
শিশুর লিম্ফ নোড ফুলে যাওয়া মানেই ক্যান্সার নয়।
বরং শিশুদের ক্ষেত্রে লিম্ফ নোড ফুলে যাওয়ার সবচেয়ে সাধারণ কারণ হলো সাধারণ সংক্রমণ।
কেন লিম্ফ নোড ফুলে যায়?
শরীরের রোগ প্রতিরোধ ব্যবস্থার গুরুত্বপূর্ণ অংশ হলো লিম্ফ নোড। কোনো সংক্রমণের বিরুদ্ধে শরীর লড়াই করার সময় এগুলো সাময়িকভাবে বড় হয়ে যেতে পারে।
সাধারণ কারণগুলোর মধ্যে রয়েছে—
ভাইরাস বা ব্যাকটেরিয়ার সংক্রমণ
গলা বা টনসিলের সংক্রমণ
দাঁত ও মাড়ির সংক্রমণ
ত্বকের সংক্রমণ
কিছু প্রদাহজনিত রোগ
বিশেষ করে ঘাড়ের লিম্ফ নোড শিশুদের মধ্যে সংক্রমণের পর কিছুদিন বড় থাকা খুবই সাধারণ।
কখন সতর্ক হবেন?
লিম্ফ নোড যদি—
কয়েক সপ্তাহ পরও না কমে বা ক্রমেই বড় হতে থাকে
ব্যথা না থাকলেও ক্রমাগত বৃদ্ধি পায়
খুব শক্ত, কম নড়াচড়া করে বা একাধিক নোড একসঙ্গে লেগে থাকে
কণ্ঠাস্থির উপরের দিকে (supraclavicular) দেখা যায়
শরীরের একাধিক স্থানে লিম্ফ নোড ফুলে যায়
দীর্ঘদিন জ্বর থাকে
রাতে অস্বাভাবিক বেশি ঘাম হয়
অকারণে ওজন কমতে থাকে
শিশুর অস্বাভাবিক দুর্বলতা বা ফ্যাকাশে ভাব দেখা দেয়
সহজে কালশিটে পড়া বা অস্বাভাবিক রক্তপাত হয়
পেট অস্বাভাবিকভাবে ফুলে যায়
তাহলে বিষয়টি অবহেলা না করে শিশু বিশেষজ্ঞের পরামর্শ নেওয়া জরুরি।
লিম্ফ নোড ফুলেছে দেখেই ভয় পাওয়ার দরকার নেই। আবার দীর্ঘদিনের বা অস্বাভাবিক লিম্ফ নোডকে অবহেলাও করা উচিত নয়।
লিম্ফ নোডের কারণ বোঝার জন্য শিশুর সম্পূর্ণ ইতিহাস ও শারীরিক পরীক্ষা সবচেয়ে গুরুত্বপূর্ণ। প্রয়োজনে চিকিৎসক পরিস্থিতি অনুযায়ী CBC, peripheral blood film, inflammatory markers, ultrasonography বা অন্যান্য পরীক্ষা দিতে পারেন।
সঠিক সময়ে সঠিক মূল্যায়নই অযথা দুশ্চিন্তা কমাতে এবং প্রয়োজনীয় চিকিৎসা দ্রুত শুরু করতে সাহায্য করে।
This info collected by Chat gpt:-
আপনার লেখার মূল মেডিক্যাল বক্তব্য সঠিক। Parent-facing health post হিসেবে এটি ভালো, তবে কয়েকটি জায়গা আরও precise করলে ভুল বোঝাবুঝির সুযোগ কমবে এবং লেখাটি academically stronger হবে।
1. আপনার লেখায় যেগুলো ঠিক আছে
শিশুদের cervical lymph node বড় হওয়ার সবচেয়ে সাধারণ কারণ reactive/infectious, বিশেষ করে viral upper respiratory infection। Healthy children-এও cervical nodes palpable হতে পারে এবং viral illness-এর পর reactive node কয়েক সপ্তাহ, কখনও কয়েক মাসও palpable থাকতে পারে। তাই “লিম্ফ নোড ফুলেছে = ক্যান্সার” বলা medically ভুল।
একটি systematic review-এ pediatric cervical lymphadenopathy-র প্রায় 67.8% nonspecific benign, আর malignancy ছিল প্রায় 4.7%; তবে এই সংখ্যা সব clinical setting-এর জন্য সরাসরি prevalence হিসেবে ব্যবহার করা উচিত নয়।
আপনি যে red flags লিখেছেন—progressive enlargement, hard/fixed/matted node, supraclavicular node, generalized lymphadenopathy, prolonged fever, weight loss, night sweats, pallor, bruising/bleeding ও hepatosplenomegaly—সবই clinically relevant।
তবে ৪টি correction করব
প্রথমত, “কণ্ঠাস্থির উপরের দিকে (supraclavicular)” anatomically ঠিক নয়। লিখুন: “কলারবোন বা clavicle-এর ঠিক উপরের অংশে (supraclavicular region)”।
দ্বিতীয়ত, “কয়েক সপ্তাহ পরও না কমে” এর পরিবর্তে আরও clinically useful হবে: “৪–৬ সপ্তাহেও না কমলে, ক্রমাগত বড় হলে, অথবা node >2 cm হলে মূল্যায়ন প্রয়োজন।” Excisional biopsy বিবেচনার established indications-এর মধ্যে persistent/progressive 4–6 weeks, >2 cm, supraclavicular location, systemic features এবং abnormal CBC/CXR রয়েছে।
তৃতীয়ত, “CBC, peripheral blood film, inflammatory markers, ultrasonography” যেন সব শিশুকেই করতে হবে এমন মনে না হয়। Well-appearing child-এর acute uncomplicated reactive cervical lymphadenopathy-তে routine investigation সাধারণত প্রয়োজন হয় না।
চতুর্থত, “পেট ফুলে যায়” এর বদলে medically precise wording হবে “লিভার বা spleen বড় পাওয়া যায়/পেটের মধ্যে mass অনুভূত হয়”।
Definition
সাধারণভাবে cervical lymph node >1 cm হলে lymphadenopathy বলা হয়, যদিও location ও age অনুযায়ী significance পরিবর্তিত হয়। Supraclavicular node ছোট হলেও comparatively বেশি concerning।
Etiology / Pathophysiology
সবচেয়ে common কারণ viral/reactive lymphadenopathy। এরপর differential-এর মধ্যে থাকে acute bacterial lymphadenitis—বিশেষত Staphylococcus aureus ও Group A Streptococcus—EBV/CMV, dental infection, tuberculosis, nontuberculous mycobacteria, Bartonella, toxoplasmosis, Kawasaki disease, autoimmune disease এবং lymphoma/leukemia।
বাংলাদেশের clinical context-এ TB অবশ্যই differential-এ রাখবেন, বিশেষ করে chronic, painless/matted nodes, constitutional symptoms বা TB exposure থাকলে।
Clinical Features
Reactive/viral pattern: সাধারণত bilateral বা multiple, ছোট, mobile, soft/rubbery; সঙ্গে recent URI/pharyngitis থাকতে পারে।
Acute bacterial lymphadenitis: বেশি করে unilateral anterior cervical node, tender, painful, fever, overlying redness/warmth; abscess হলে fluctuation হতে পারে।
Malignancy/TB/other chronic disease সন্দেহ: painless progressive node, firm/hard, fixed/matted, >2 cm, supraclavicular location, generalized lymphadenopathy, weight loss, persistent fever, drenching night sweats, pallor/bruising, hepatosplenomegaly ইত্যাদি।
Investigations
Well child + recent viral illness + small mobile node + no red flag হলে routine CBC/USG করার প্রয়োজন নেই। Clinical observation appropriate।
Persistent, progressive বা red-flag lymphadenopathy হলে investigation clinical suspicion অনুযায়ী করা উচিত:
| Investigation | কখন |
| CBC + differential + Peripheral blood film | persistent/generalized node, pallor, bruising, malignancy suspicion |
| CRP/ESR | inflammatory/infective assessment |
| LDH ± uric acid | malignancy/high cell-turnover suspicion |
| LFT | EBV/CMV/systemic illness |
| EBV/CMV serology | compatible clinical picture |
| TST/IGRA ± CXR | TB exposure/suspicion |
| Bartonella testing | cat exposure + compatible lymphadenitis |
| Neck USG | abscess suspected, uncertain neck mass, persistent node |
| Chest X-ray | lymphoma/TB/mediastinal disease suspected |
RCH specifically recommends considering CBC/blood film, CRP/ESR/LDH, LFT, targeted infectious testing, TB testing, CXR and USG for persistent or concerning cases.
Importantly, normal ultrasound alone malignancy completely exclude করতে পারে না। Tissue diagnosis প্রয়োজন হলে excisional biopsy remains the reference standard in children.
Differential Diagnosis
Clinically, আমি এটাকে ভাবব: reactive viral node → acute bacterial lymphadenitis/abscess → ENT/dental infection → EBV/CMV → TB/NTM → Bartonella → Kawasaki disease → autoimmune disease → leukemia/lymphoma → congenital neck masses.
Management / Treatment
এখানে সবচেয়ে গুরুত্বপূর্ণ কথা:
“Lymph node বড়” দেখে কোনো একটি antibiotic prescribe করা যাবে না। Treatment underlying cause অনুযায়ী।
1. Viral / reactive lymphadenopathy
Child well, recent URI, node mobile/soft, no red flags হলে:
Antibiotic নয়।
Observation + adequate hydration + fever/pain থাকলে weight-appropriate paracetamol/ibuprofen + underlying URI management যথেষ্ট। 1–2 cm isolated node এবং কোনো red flag না থাকলে 4–6 সপ্তাহ পর্যন্ত follow-up করা যায়; প্রায় 2 সপ্তাহে interim review করলে growth হচ্ছে কি না বোঝা যায়।
Viral illness ভালো হওয়ার পরও node কিছুদিন palpable থাকা স্বাভাবিক।
2. Acute bacterial cervical lymphadenitis
Typical picture:
unilateral + tender + fever ± erythema ± fluctuation
Empiric antibiotic-এ S. aureus ও Group A Streptococcus cover করতে হবে।
একটি established pediatric regimen হিসেবে RCH guideline দেয়:
Cefalexin 20 mg/kg/dose PO TDS × 7 days, maximum 750 mg/dose, এবং 48 ঘণ্টায় review।
UCSF protocol সামান্য ভিন্ন regimen ব্যবহার করে—cephalexin 25 mg/kg/dose TID এবং সাধারণত 10 দিনের course—তাই local susceptibility pattern ও institutional pediatric antimicrobial guideline follow করাই সঠিক।
Amoxicillin alone uncomplicated suppurative lymphadenitis-এর ideal empiric choice নয়, কারণ adequate antistaphylococcal coverage প্রয়োজন।
3. Dental source থাকলে
Periodontal/dental infection থাকলে oral streptococci ও anaerobic coverage দরকার।
একটি evidence-based regimen:
Amoxicillin-clavulanate 22.5 mg amoxicillin/kg/dose PO BID, maximum amoxicillin component 875 mg/dose; UCSF protocol সাধারণত 10 days ব্যবহার করে।
Dental source-controlও প্রয়োজন।
4. MRSA risk / severe beta-lactam allergy
Documented recent MRSA colonisation/infection বা appropriate severe beta-lactam allergy থাকলে clindamycin একটি option হতে পারে, কিন্তু local susceptibility নিশ্চিত করা গুরুত্বপূর্ণ। UCSF pediatric guidance-এ 10 mg/kg/dose PO TID ব্যবহৃত হয়।
Bangladesh-এর local antibiogram অনুযায়ী antibiotic selection adjust করা উচিত।
5. Child unwell / oral treatment failure
Toxic appearance, young infant, dehydration, rapidly progressive swelling, deep-neck infection suspicion বা oral antibiotic-এ improvement না হলে admission/IV treatment বিবেচনা করবেন।
RCH regimen:
Cefazolin 50 mg/kg/dose IV every 8 hours, maximum 2 g/dose।
Sepsis/deep neck infection suspected হলে broader management ও ENT/paediatric/ID input প্রয়োজন।
6. Fluctuant node / abscess
USG দিয়ে abscess assess করা যেতে পারে। Significant fluctuation বা IV antibiotic-এ response না হলে ENT/surgical consultation + drainage/source control প্রয়োজন হতে পারে এবং drainage material culture করা উচিত।
7. TB / NTM suspected
Chronic painless or matted node, TB contact, weight loss, fever ইত্যাদি থাকলে blind repeated antibiotic course নয়।
TST/IGRA, CXR ও appropriate TB work-up করে paediatric/TB specialist pathway follow করা উচিত। Suspected nontuberculous mycobacterial lymphadenitis-এ simple incision and drainage এড়ানো হয়, কারণ chronic sinus tract হতে পারে; selected cases-এ complete excision preferred।
8. Malignancy suspected
এক্ষেত্রে repeated antibiotics দিয়ে delay করবেন না।
2 cm, progressive 4–6 weeks, hard/fixed/matted, supraclavicular node, unexplained fever/weight loss/night sweats, generalized lymphadenopathy, hepatosplenomegaly অথবা abnormal CBC/PBF হলে urgent paediatric/haematology assessment প্রয়োজন। Excisional biopsy tissue diagnosis-এর gold-standard approach।
আর একটি গুরুত্বপূর্ণ clinical pearl: undiagnosed lymphadenopathy-তে empirical corticosteroid দেবেন না, বিশেষ করে lymphoma/leukemia possibility থাকলে; steroid histology পরিবর্তন করে diagnosis delay/mask করতে পারে।
Overview / Summary
আপনার লেখাটি প্রায় পুরোপুরি medically sound। সবচেয়ে গুরুত্বপূর্ণ modifications হলো supraclavicular-এর বাংলা location ঠিক করা, persistent node-এর ক্ষেত্রে 4–6 weeks / >2 cm criteria যোগ করা এবং পরিষ্কার করে লেখা যে সব lymphadenopathy-তে CBC/USG বা antibiotic লাগে না।
এক লাইনের clinical rule:
Well child + small/mobile/reactive node → observe.
Tender unilateral febrile node → bacterial lymphadenitis ভাবুন।
Hard/fixed/progressive/>2 cm/supraclavicular/systemic signs → investigate and refer.
Actionable Plan / Steps
Clinical practice-এ প্রথমে duration → location → size → tenderness/mobility → unilateral/bilateral → infection focus → generalized nodes → liver/spleen → red flags assess করুন। Clear viral/reactive হলে antibiotic দেবেন না। Typical bacterial lymphadenitis হলে antistaphylococcal/GAS coverage দিয়ে 48–72 ঘণ্টায় response review করুন। Response না হলে abscess, TB/NTM, Kawasaki disease, atypical infection বা malignancy পুনর্বিবেচনা করুন।
Treatment Management
1. Generic name: Cephalexin / Cefalexin
- Therapeutic category: Antibiotic
- Pharmacological class: First-generation cephalosporin
- Drug description: Bacterial cell-wall synthesis inhibit করে bactericidal effect তৈরি করে।
- কেন ব্যবহার করা হয়: Well-appearing শিশুর acute uncomplicated bacterial cervical lymphadenitis—বিশেষ করে unilateral, tender node + fever/erythema থাকলে। প্রধান target হলো MSSA এবং Group A Streptococcus। Viral/reactive lymph node-এর জন্য নয়।
- Pediatric dose: 20 mg/kg/dose PO, দিনে 3 বার (TDS); maximum 750 mg/dose।
- Duration: সাধারণত 7 days; 48 ঘণ্টায় clinical review। RCH এই regimen ব্যবহার করে। UCSF protocol-এ 25 mg/kg/dose TID এবং প্রায় 10 days ব্যবহৃত হয়—অর্থাৎ local antimicrobial guideline অনুযায়ী সামান্য variation থাকতে পারে।
- Common side effects: nausea, vomiting, diarrhoea, abdominal discomfort, rash।
- Important adverse effects: allergy/anaphylaxis, antibiotic-associated colitis; rare neutropenia।
- Drug interactions: Probenecid cephalexin-এর renal excretion কমিয়ে level বাড়াতে পারে; metformin exposure-ও বাড়তে পারে।
- Bangladesh-available MedEx brands: Acelex 125 mg/5 mL, 250 mg, 500 mg; Cefalex 125 mg/5 mL, 500 mg; Cephalen 125 mg/5 mL, 250 mg, 500 mg; Neorex 125 mg/5 mL, 250 mg, 500 mg; Selex 125 mg/5 mL, 500 mg।
Specific use: typical bacterial lymphadenitis-এ প্রথম oral optionগুলোর একটি; broad-spectrum antibiotic দিয়ে শুরু করার প্রয়োজন সাধারণত নেই।
2. Generic name: Amoxicillin + Clavulanic Acid
- Therapeutic category: Broad-spectrum antibacterial
- Pharmacological class: Aminopenicillin + β-lactamase inhibitor
- Drug description: Amoxicillin bacterial cell-wall synthesis বন্ধ করে; clavulanate β-lactamase inhibit করে amoxicillin-কে enzymatic destruction থেকে রক্ষা করে।
- কেন ব্যবহার করা হয়: Cervical lymphadenitis-এর সঙ্গে dental abscess, gingivitis, periodontal disease, poor oral hygiene বা odontogenic source সন্দেহ হলে এটি বেশি appropriate, কারণ oral streptococci + anaerobes cover প্রয়োজন।
- Pediatric dose: 22.5 mg/kg/dose of amoxicillin component PO BID।
- Maximum: 875 mg amoxicillin/dose।
- Duration: সাধারণত 10 days, অথবা clinical response/source control অনুযায়ী।
- Common side effects: diarrhoea, loose stool, nausea, vomiting, abdominal discomfort, rash।
- Important adverse effects: anaphylaxis, C. difficile-associated diarrhoea, rare cholestatic/hepatic injury।
- Drug interactions: Probenecid amoxicillin level বাড়ায়; warfarin/other oral anticoagulant-এর সঙ্গে INR বাড়তে পারে; allopurinol-এর সঙ্গে rash-এর ঝুঁকি বাড়তে পারে।
- Bangladesh-available MedEx brands: Amoclav 125+31.25 mg/5 mL, 500+125 mg, 875+125 mg; Amoclav Forte 400+57.5 mg/5 mL; Aristomox CV 125+31.25 mg/5 mL, 250+125 mg, 500+125 mg, 875+125 mg; Aristomox CV Forte 400+57.5 mg/5 mL; Amotid CL 125+31.25 mg/5 mL, 500+125 mg; Amovix 125+31.25 mg/5 mL, 250+125 mg, 500+125 mg।
Specific use: simple non-dental cervical lymphadenitis-এ automatically cephalexin-এর বদলে amoxiclav দেওয়া উচিত নয়; oral/dental anaerobic source থাকলে এর advantage বেশি।
3. Generic name: Clindamycin
- Therapeutic category: Antibiotic
- Pharmacological class: Lincosamide antibiotic
- Drug description: Bacterial 50S ribosomal subunit-এ bind করে protein synthesis inhibit করে।
- কেন ব্যবহার করা হয়: Severe immediate β-lactam allergy, অথবা documented/recent MRSA infection or colonisation থাকলে alternative হিসেবে; dental/anaerobic infection-ও cover করতে পারে। Previous culture থাকলে susceptibility দেখে ব্যবহার করা ভালো।
- Pediatric oral dose: 10 mg/kg/dose PO TID, maximum 600 mg/dose।
- IV dose: 10 mg/kg/dose IV every 8 hours, maximum সাধারণত 900 mg/dose।
- Duration: সাধারণত 10 days; drainage হলে clinical situation অনুযায়ী 5–7 days after source control হতে পারে।
- Common side effects: nausea, vomiting, abdominal pain, diarrhoea, rash।
- Important adverse effect: Clostridioides difficile-associated colitis—significant/persistent diarrhoea হলে গুরুত্ব দিতে হবে।
- Other adverse effects: oesophagitis/oesophageal ulcer, urticaria।
- Drug interactions: Erythromycin-এর সঙ্গে antagonism হতে পারে—concurrent use avoid; neuromuscular-blocking agents-এর effect বাড়াতে পারে।
- Bangladesh-available MedEx brands: Clindacin 75 mg/5 mL, 150 mg, 300 mg, 300 mg/2 mL, 600 mg/4 mL; Clindax 75 mg/5 mL, 150 mg, 300 mg, 300 mg/2 mL, 600 mg/4 mL; Clinacyn 150 mg, 300 mg; Climycin 300 mg; Daclin 150 mg, 300 mg; Dalacin C 300 mg।
Specific use: routine প্রথম-line drug নয়; MRSA risk বা serious β-lactam allergy থাকলে বেশি relevant।
4. Generic name: Cefazolin
- Therapeutic category: Parenteral antibiotic
- Pharmacological class: First-generation cephalosporin
- Drug description: Bacterial cell-wall synthesis inhibit করে bactericidal activity দেয়।
- কেন ব্যবহার করা হয়: Child systemically unwell, significant bacterial cervical lymphadenitis, oral antibiotic নিতে না পারা অথবা oral treatment failure হলে inpatient IV therapy হিসেবে।
- Pediatric dose: 50 mg/kg/dose IV every 8 hours।
- Maximum: 2 g/dose।
- Duration: Severe cervical lymphadenitis-এ ≥7 days হতে পারে, তবে clinical response হলে oral agent-এ step-down করা যায়।
- Common side effects: injection-site pain, diarrhoea, nausea, vomiting, abdominal discomfort, rash।
- Important adverse effects: hypersensitivity/anaphylaxis, antibiotic-associated colitis; renal impairment-এ excessive level হলে neurotoxicity/seizure risk বাড়তে পারে।
- Drug interaction: Probenecid renal secretion কমিয়ে cefazolin concentration বাড়ায়।
- Bangladesh-available MedEx brands: Cefazol 500 mg/vial, 1 g/vial; Cefalin 1 g/vial; Zolibac 1 g/vial; Cefazoline Panpharma 1 g/5 mL।
Specific use: toxic/unwell child বা failed oral treatment-এর IV treatment, uncomplicated viral node-এর জন্য নয়।
Symptomatic Medicines
5. Generic name: Paracetamol / Acetaminophen
- Therapeutic category: Analgesic + antipyretic
- Pharmacological class: Non-opioid analgesic
- কেন ব্যবহার করা হয়: Fever এবং lymphadenitis-associated pain/discomfort কমাতে। এটি lymph node infection cure করে না।
- Pediatric dose: সাধারণত 10–15 mg/kg/dose PO every 4–6 hours PRN; WHO pocket guidance-এ 15 mg/kg every 6 hours ব্যবহৃত হয়েছে।
- Duration: প্রয়োজন অনুযায়ী short-term; underlying cause treat করতে হবে।
- Common side effects: সাধারণ therapeutic dose-এ uncommon; nausea/rash হতে পারে।
- Major toxicity: overdose → potentially severe hepatotoxicity।
- Interaction/caution: অন্য cough/cold/analgesic preparation-এ paracetamol আছে কিনা check করতে হবে, যাতে accidental duplicate dosing না হয়।
- Bangladesh-available MedEx brands: Ace 120 mg/5 mL, 80 mg/mL drops, 125 mg suppository, 250 mg suppository, 500 mg; A-One 120 mg/5 mL; Acep 120 mg/5 mL, 80 mg/mL, 500 mg; Aceta 120 mg/5 mL, 500 mg।
Specific use: শিশুর discomfort/pain/fever control; lymphadenopathy shrink করার drug নয়।
6. Generic name: Ibuprofen
- Therapeutic category: Analgesic, antipyretic, anti-inflammatory
- Pharmacological class: NSAID
- কেন ব্যবহার করা হয়: Lymphadenitis-এর inflammatory pain, tenderness এবং fever কমানোর symptomatic option।
- Pediatric dose: সাধারণত 10 mg/kg/dose PO every 6–8 hours PRN।
- Maximum: প্রায় 40 mg/kg/day ব্যবহৃত হয় অনেক pediatric guideline-এ।
- Age: সাধারণভাবে ≥6 months হলে বেশি routinely ব্যবহার করা হয়।
- Duration: প্রয়োজন অনুযায়ী short course।
- Common side effects: dyspepsia, abdominal discomfort, nausea।
- Important adverse effects: GI bleeding/ulcer, renal impairment, bronchospasm in susceptible patients।
- Avoid/caution: significant dehydration, renal disease, GI bleeding/ulcer, NSAID hypersensitivity; chickenpox-এও avoid/caution করা হয়।
- Drug interactions: Other NSAIDs/aspirin, anticoagulants, corticosteroids, ACE inhibitors/diuretics, lithium, methotrexate, cyclosporine/tacrolimus-এর সঙ্গে clinically relevant interaction হতে পারে।
- Bangladesh-available MedEx brands: Advel 100 mg/5 mL, 200 mg, 400 mg; অন্যান্য MedEx-listed brands-এর মধ্যে Alflam 400 mg, Anaflam 400 mg, Brofen 400 mg ইত্যাদি রয়েছে। শিশুদের জন্য suspension formulation বেশি relevant।
Specific use: inflammation/pain/fever control; bacterial infection treat করে না।
কোন ক্ষেত্রে কোন drug?
Viral URI + bilateral/mobile/small nodes + child well: antibiotic না; observation ± paracetamol/ibuprofen।
Unilateral + tender + fever ± erythema, child otherwise well: bacterial lymphadenitis → Cephalexin first-line option; 48 ঘণ্টায় reassess।
Dental/gingival source: Amoxicillin-clavulanate বেশি appropriate।
MRSA history বা serious immediate β-lactam allergy: susceptibility অনুযায়ী Clindamycin বিবেচনা।
Child toxic/unwell বা oral treatment failure: admission + IV Cefazolin, abscess আছে কি না evaluate।
Fluctuant/abscess: শুধু antibiotic দিয়ে repeatedly চালানো নয়; USG/ENT or surgical assessment এবং প্রয়োজন হলে drainage/source control।
48–72 ঘণ্টায় improvement না হলে: diagnosis পুনর্বিবেচনা করুন—abscess, Kawasaki disease, TB/NTM, Bartonella, EBV/CMV অথবা malignancy বিবেচনা করতে হবে।
TB/NTM suspected: empiric routine cephalexin/amoxiclav repeatedly দেওয়া উচিত নয়; TB work-up এবং national TB protocol/paediatric specialist management প্রয়োজন।
Hard/fixed/matted, supraclavicular, >2 cm, progressively enlarging, persistent 4–6 weeks, weight loss/night sweat, hepatosplenomegaly বা abnormal CBC: antibiotic course repeat না করে investigation/referral; excisional biopsy tissue diagnosis-এর gold standard।
Prevention
Cervical lymphadenopathy পুরোপুরি prevent করা সম্ভব নয়, কারণ viral illness শিশুদের খুব common। তবে risk কমাতে hand hygiene, respiratory infection prevention, ভালো dental/oral hygiene, dental caries ও gingivitis দ্রুত চিকিৎসা, skin/scalp infection দ্রুত treatment, শিশুদের routine vaccination সম্পূর্ণ রাখা, TB exposure এড়ানো ও household TB contact থাকলে দ্রুত screening, এবং অপ্রয়োজনে antibiotic না দেওয়াই গুরুত্বপূর্ণ।
Node বারবার চাপা বা massage করা উচিত নয়। Bacterial lymphadenitis হলে prescribed antibiotic course যথাযথভাবে complete এবং 48–72 ঘণ্টায় response assess করা গুরুত্বপূর্ণ।
Reference List
Textbook: Kliegman RM, St. Geme JW, eds. Nelson Textbook of Pediatrics. 22nd ed. Elsevier; 2024/2025. Chapter 539: Lymphadenopathy. Elsevier confirms this as the current 22nd edition and lists Chapter 539 under the lymphatic system.
Guidelines: Royal Children’s Hospital Melbourne. Clinical Practice Guideline: Cervical Lymphadenopathy. Management includes observation for well children, bacterial lymphadenitis treatment, ultrasound when abscess is suspected, and biopsy indications.
NICE. Suspected cancer: recognition and referral, NG12. Last reviewed April 2026; unexplained lymphadenopathy in children with concerning associated features warrants very urgent specialist assessment.
UCSF Infectious Diseases Management Program. Pediatric Lymphadenitis. Current antimicrobial/source-control guidance.
Peer-reviewed: Chang SSY, et al. An approach to cervical lymphadenopathy in children. Singapore Med J. 2020;61(11):569–577. DOI: 10.11622/smedj.2020151.
Weinstock MS, Patel NA, Smith LP. Pediatric Cervical Lymphadenopathy. Pediatrics in Review. 2018;39(9):433–443. DOI: 10.1542/pir.2017-0249.
Deosthali A, et al. Etiologies of Pediatric Cervical Lymphadenopathy: A Systematic Review of 2687 Subjects. Global Pediatric Health. 2019;6. DOI: 10.1177/2333794X19865440
Md.Rafiqul Islam Lipu,Date:-21-09-2026,Monday,Time:-04-44-29 Pm